
Newborn Care & Neonatal Complications
In this chapterفي هذا الفصل
Key terms (12)المصطلحات الأساسية
Chapter outline (10 sections)مخطط الفصل
- Learning Objectivesأهداف التعلّم
- 8.1 · The First Minutes and Keeping the Baby Warm٨٫١ · الدقائق الأولى وإبقاء الطفل دافئاً
- 8.2 · When the Baby Does Not Breathe٨٫٢ · حين لا يتنفّس الطفل
- 8.3 · Prophylaxis, the Cord and the Newborn Examination٨٫٣ · الوقاية والحبل وفحص الوليد
- 8.4 · What You Actually See and Feel٨٫٤ · ما يُرى ويُتحسَّس فعلاً
- 8.5 · Jaundice٨٫٥ · اليرقان
- 8.6 · Low Blood Sugar and Difficulty Breathing٨٫٦ · نقص السكّر وصعوبة التنفّس
- 8.7 · The Preterm Baby, Infection and the Local Setting٨٫٧ · الطفل المبتسر والعدوى والسياق المحلّي
- 8.8 · Output, Handover and Moving a Baby٨٫٨ · الإخراج والتسليم ونقل طفل
- 8.9 · Watching How They Are Together, and Going Home٨٫٩ · مراقبة كيف هما معاً والعودة للمنزل
Start learningبدء التعلّم Learning objectivesأهداف التعلّم Test yourselfالاختبار الذاتي
Learning Objectivesأهداف التعلّم
8.1 · The First Minutes and Keeping the Baby Warm٨٫١ · الدقائق الأولى وإبقاء الطفل دافئاً
The Apgar score assesses five things, each scored 0, 1 or 2, at one and five minutes and thereafter if needed.
تقيّم درجة أبغار خمسة أمور كلّ منها بصفر أو واحد أو اثنين عند الدقيقة الأولى والخامسة وبعدها إن لزم.
The point that must be understood alongside the score is examined, and getting it wrong costs time: the Apgar is a RECORD of the baby’s condition — it is not what triggers resuscitation. You do not wait for the one-minute score before acting. Resuscitation begins on assessment of breathing, heart rate and tone, immediately.
النقطة الواجب فهمها إلى جانب الدرجة تُختبَر والخطأ فيها يكلّف وقتاً: أن أبغار سجلّ لحالة الطفل — وليس ما يُطلق الإنعاش. فلا تُنتظَر درجة الدقيقة الأولى قبل التصرّف. والإنعاش يبدأ على تقييم التنفّس ومعدّل القلب والتوتّر فوراً.
A newborn loses heat far faster than an adult, and for structural reasons.
يفقد الوليد الحرارة أسرع بكثير من البالغ، ولأسباب بنيوية.
Cold stress is not merely discomfort, and this is what makes thermoregulation a clinical priority rather than a kindness.
الكرب البارد ليس مجرّد انزعاج، وهذا ما يجعل تنظيم الحرارة أولويةً سريرية لا لطفاً.
Maintaining warmth is therefore active: dry immediately and remove wet linen; put a hat on, since the head is a large proportion of the surface area; skin to skin with the mother, which is the best thermal care there is and starts feeding; warm the room and close the doors; pre-warm surfaces and any equipment that touches him; and delay the bath until the temperature is stable.
الحفاظ على الدفء إذن إجراء فاعل: يُجفَّف الطفل فوراً وتُزال البياضات المبتلّة؛ وتوضع قبّعة فالرأس نسبة كبيرة من المساحة؛ وتلامس جلدي مع الأمّ وهو أفضل رعاية حرارية موجودة ويبدأ الرضاعة؛ وتُدفَّأ الغرفة وتُغلق الأبواب؛ وتُسخَّن الأسطح مسبقاً وأيّ معدّات تلمسه؛ ويُؤخَّر الحمّام حتى تستقرّ الحرارة.
8.2 · When the Baby Does Not Breathe٨٫٢ · حين لا يتنفّس الطفل
- Compression led
- A primary cardiac cause
- Circulation first
- Defibrillation is often the answer
- AIRWAY and BREATHING led — the opposite of the adult sequence
- The problem is almost always failure to establish breathing
- Effective ventilation alone corrects most of them
- Compressions are the exception, not the rule
Chest compressions are added only where the heart rate remains below the threshold your algorithm specifies DESPITE EFFECTIVE ventilation — and the word effective is doing the work. Compressions on a baby whose chest is not moving treat the wrong problem.
الضغطات تُضاف فقط حيث يبقى معدّل القلب دون العتبة التي تحدّدها الخوارزمية المعتمدة رغم تهوية فعّالة — وكلمة «فعّالة» هي بيت القصيد. فالضغطات على طفل لا يتحرّك صدره تعالج المشكلة الخاطئة.
8.3 · Prophylaxis, the Cord and the Newborn Examination٨٫٣ · الوقاية والحبل وفحص الوليد
Vitamin K is given to prevent vitamin K deficiency bleeding, historically called haemorrhagic disease of the newborn — a condition that can cause catastrophic bleeding, including intracranial haemorrhage.
يُعطى فيتامين ك لمنع نزف نقص فيتامين ك وكان يُسمّى تاريخياً مرض الوليد النزفي — حالة قد تسبّب نزفاً كارثياً بما فيه نزف داخل القحف.
Eye prophylaxis prevents ophthalmia neonatorum — conjunctivitis acquired during passage through the birth canal. It matters because gonococcal infection can destroy the cornea and cause blindness within days, and because the mother may have no symptoms and no idea she carries it. So it is given routinely rather than on suspicion. Teach the parents that any purulent discharge or swollen lids in the first weeks needs same-day assessment — it is not ‘sticky eye’ to be watched.
الوقاية العينية تمنع رمد الوليد — التهاب ملتحمة يُكتسَب أثناء المرور بقناة الولادة. ويهمّ لأن العدوى بالمكوّرات البنّية قد تدمّر القرنية وتسبّب العمى خلال أيام ولأن الأمّ قد لا تكون لديها أعراض ولا فكرة أنها حاملة. فهي تُعطى روتينياً لا على الاشتباه. ويُعلَّم الوالدان أن أيّ إفراز قيحي أو جفنين متورّمين في الأسابيع الأولى يحتاج تقييماً في اليوم نفسه، وليس مجرّد «عين لاصقة» يُكتفى بمراقبتها.
Cord care is straightforward and the message is one word: dry. Keep it clean and dry, exposed to air, and folded outside the nappy so urine does not soak it. Do not apply powders, oils, kohl or traditional substances — they introduce infection, and tetanus and omphalitis are what they cause. Teach the signs to report: redness spreading onto the abdominal wall, offensive discharge, swelling, or a baby who is unwell.
رعاية الحبل بسيطة والرسالة كلمة واحدة: جافّ. يُبقى نظيفاً جافّاً معرّضاً للهواء ومطوياً خارج الحفاض كي لا يبلّله البول. ولا تُوضَع مساحيق ولا زيوت ولا كحل ولا مواد تقليدية — فهي تُدخل العدوى، والكزاز والتهاب السرّة هما ما تسبّبه. وتُعلَّم العلامات الواجب الإبلاغ عنها: احمرار ينتشر على جدار البطن أو إفراز كريه أو تورّم أو طفل متوعّك.
The routine observations a nurse must know cold.
القياسات الروتينية التي يجب أن يعرفها الممرّض معرفة تامّة.
8.4 · What You Actually See and Feel٨٫٤ · ما يُرى ويُتحسَّس فعلاً
Several normal skin findings alarm parents and are worth naming so you can reassure specifically rather than generally.
عدّة موجودات جلدية طبيعية تُفزع الوالدين وتستحقّ التسمية كي تكون الطمأنة محدّدة لا عامّة.
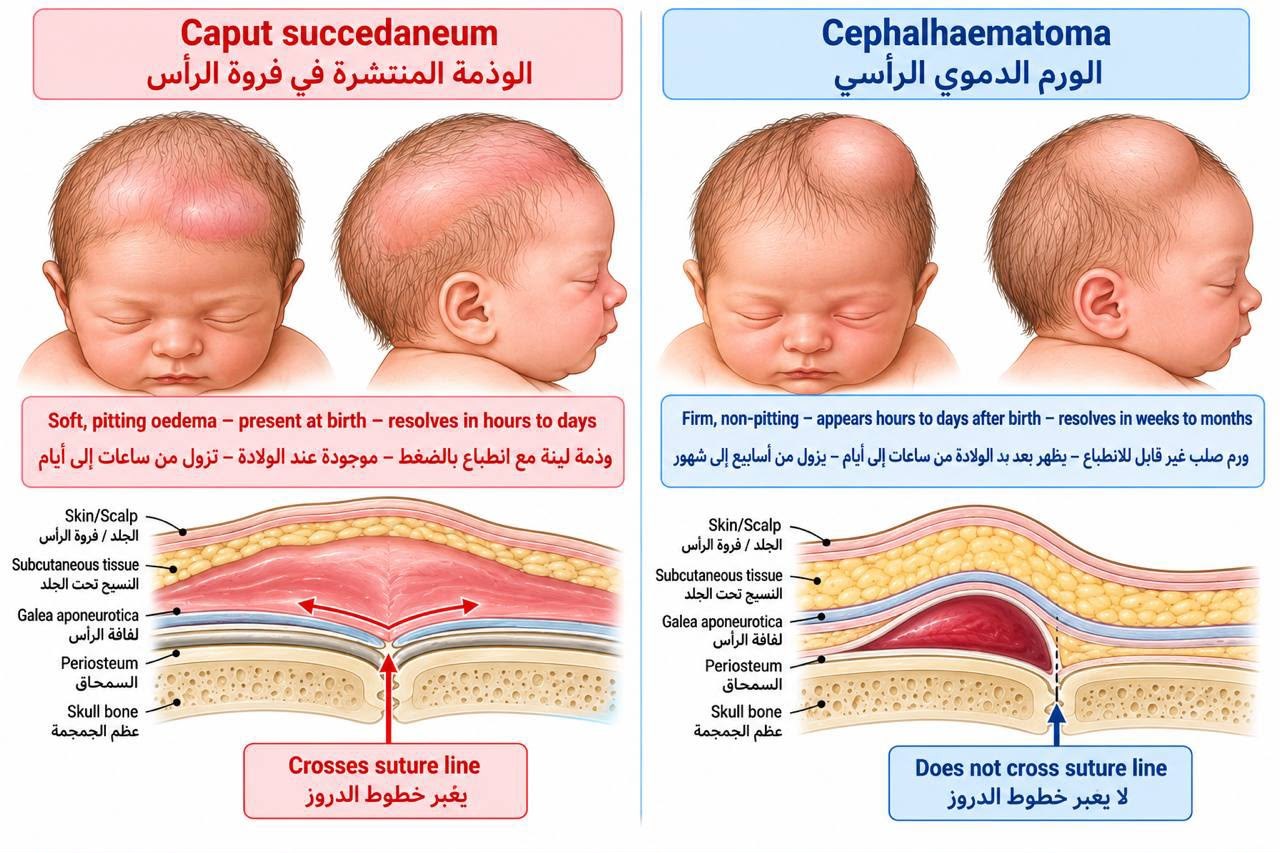
Two scalp swellings are distinguished by one feature, and the distinction matters.
يُميَّز بين تورّمين في فروة الرأس بسمة واحدة، والتمييز مهمّ.
- Diffuse oedema of the scalp from pressure during birth
- Present AT birth
- CROSSES suture lines
- Soft, pits on pressure
- Resolves within days
- Bleeding beneath the periosteum
- Appears AFTER birth and may enlarge
- Does NOT cross suture lines — the discriminator
- Firmer, well-defined edge
- Takes weeks, and can worsen jaundice as the blood breaks down
Crossing the suture lines is the discriminator, and the practical consequence is the last line: a cephalhaematoma is a reason to watch the bilirubin.
عبور خطوط الدروز هو المميّز، والعاقبة العملية هي السطر الأخير: فالورم الدموي الرأسي سبب لمراقبة البيليروبين.
The rest of the examination follows a fixed order, and each element exists because something serious is being looked for.
بقيّة الفحص تتبع ترتيباً ثابتاً، وكلّ عنصر موجود لأن شيئاً خطيراً يُبحَث عنه.
And the parts that are easy to hurry: count the fingers and toes and look at the palms; check the anus is patent; examine the genitalia — in a boy, that the testes are descended and the urethral opening is in the normal position; and note ambiguous genitalia as an urgent referral before a sex is assigned or registered. Measure and plot weight, length and head circumference.
الأجزاء التي يسهل الإسراع بها: تُعدّ أصابع اليدين والقدمين ويُنظر إلى الراحتين؛ ويُتحقَّق من أن الشرج مفتوح؛ وتُفحَص الأعضاء التناسلية — في المولود الذكر أن الخصيتين نازلتان وفتحة الإحليل في موضعها الطبيعي؛ ويُسجَّل أن الأعضاء التناسلية الملتبسة تستدعي إحالة عاجلة قبل تحديد الجنس أو تسجيله. ويُقاس الوزن والطول ومحيط الرأس ويُرسَم كلّ منها على المنحنيات.
8.5 · Jaundice٨٫٥ · اليرقان
Jaundice is very common and usually harmless, and the whole clinical skill lies in separating the physiological from the pathological.
اليرقان شائع جداً وحميد عادةً، والمهارة السريرية كلّها في فصل الفيزيولوجي عن المرضي.
- Appears AFTER the first 24 hours
- Typically day 2–3, peaks around day 3–5
- Resolves within about a week (longer if preterm)
- Baby is well, feeding, gaining
- Unconjugated bilirubin
- WITHIN the first 24 hours — ALWAYS pathological
- Or a rapidly rising level
- Or persisting beyond 14 days (21 if preterm)
- Or the baby is unwell, feeding poorly, lethargic
- Or conjugated bilirubin is raised — with pale stools and dark urine
The single most examinable rule: jaundice appearing within the first 24 hours of life is always pathological and requires urgent assessment — haemolysis, including rhesus and ABO incompatibility, is the usual cause and it moves fast.
أكثر قاعدة قابلة للاختبار: أنّ اليرقان الظاهر خلال أول ٢٤ ساعة من الحياة مرضي دائماً ويتطلّب تقييماً عاجلاً — والانحلال الدموي بما فيه عدم توافق الريسوس وABO السبب المعتاد ويتحرّك بسرعة.
And the second: prolonged jaundice beyond 14 days is investigated, not watched — because pale stools and dark urine with conjugated jaundice mean biliary atresia until proved otherwise, and the surgical window for that closes early.
والثانية: أن اليرقان المطوّل بعد ١٤ يوماً يُستقصى لا يُكتفى بمراقبته — فالبراز الشاحب والبول الداكن مع يرقان مقترن يعنيان رتق القنوات الصفراوية حتى يُثبَت خلافه والنافذة الجراحية له تُغلَق مبكّراً.
Kernicterus is why any of this matters. Unconjugated bilirubin is fat-soluble, and at high levels it crosses into the brain and deposits in the basal ganglia, causing permanent damage: cerebral palsy, deafness, and intellectual disability. It is entirely preventable, and entirely irreversible once it has happened.
اليرقان النووي هو سبب أهمّية كلّ هذا. فالبيليروبين غير المقترن ذائب في الدهن وبمستويات عالية يعبر للدماغ ويترسّب في العقد القاعدية مسبّباً تلفاً دائماً: شللاً دماغياً وصمماً وإعاقةً ذهنية. وهو قابل للمنع تماماً وغير عكوس تماماً بعد حدوثه.
Phototherapy converts bilirubin in the skin into a form that can be excreted without conjugation. The nursing care has a fixed shape, and each element has a reason.
المعالجة الضوئية تحوّل البيليروبين في الجلد لشكل يمكن طرحه دون اقتران. وللرعاية التمريضية شكل ثابت ولكلّ عنصر سبب.
8.6 · Low Blood Sugar and Difficulty Breathing٨٫٦ · نقص السكّر وصعوبة التنفّس
Neonatal hypoglycaemia is common, dangerous and — the reason it is dealt with by protocol rather than by observation — frequently asymptomatic.
نقص سكّر الدم الوليدي شائع وخطير، وهو — وهذا سبب معالجته ببروتوكول لا بالملاحظة — كثيراً ما يكون عديم الأعراض.
When signs do appear they are non-specific and shared with almost every other neonatal problem: jitteriness, poor feeding, lethargy, temperature instability, a weak or high-pitched cry, apnoea, hypotonia and seizures. So the finding is used in reverse: a baby with any of these has a blood glucose checked, because it takes seconds and excludes a treatable cause.
حين تظهر العلامات تكون غير نوعية ومشتركة مع كلّ مشكلة وليدية أخرى تقريباً: ارتعاش وسوء رضاعة وخمول وعدم استقرار حراري وبكاء ضعيف أو عالي النبرة وانقطاع نفس ونقص توتّر واختلاجات. فتُستخدَم العلامة بالعكس: يُفحَص سكّر دم أيّ طفل تظهر عليه إحداها، لأن ذلك يستغرق ثوانٍ ويستبعد سبباً قابلاً للعلاج.
Management follows the protocol: feed early and frequently, recheck, and escalate to intravenous glucose where the level does not respond or the baby is symptomatic. And the prevention that costs nothing: keep him warm and feed him early — the two things that stop a well baby becoming a hypoglycaemic one.
التدبير يتبع البروتوكول: تكون الإرضاعة مبكّرة ومتواترة، ويُعاد الفحص، ويُصعَّد العلاج إلى غلوكوز وريدي حيث لا يستجيب المستوى أو يكون الطفل عرضياً. والوقاية التي لا تكلّف شيئاً: إبقاؤه دافئاً وإرضاعه مبكّراً — وهما الأمران اللذان يمنعان الطفل السليم من أن يصبح ناقص السكّر.
Respiratory distress has a set of signs a nurse should recognise from across a room.
الضائقة التنفّسية لها مجموعة علامات ينبغي أن يميّزها الممرّض من الطرف الآخر للغرفة.
- Delayed clearance of lung fluid
- Commoner after caesarean — no thoracic squeeze of a vaginal birth
- Appears soon after birth
- Settles over 24–72 hours
- Supportive care; often needs little or no oxygen
- Surfactant deficiency — the alveoli collapse
- A disease of prematurity — the more preterm, the higher the risk
- Worsens over the first hours
- Needs surfactant, respiratory support and time
- Antenatal steroids given to the mother reduce it
The discriminator worth carrying: transient tachypnoea improves, respiratory distress syndrome worsens — and direction of travel over the first hours tells you which you are looking at more reliably than the initial picture.
المميّز الجدير بالتذكّر: أن تسرّع التنفّس العابر يتحسّن ومتلازمة الضائقة التنفّسية تسوء — واتّجاه السير عبر الساعات الأولى يدلّ على الحالة المعنيّة بموثوقية أكبر من الصورة الأولية.
8.7 · The Preterm Baby, Infection and the Local Setting٨٫٧ · الطفل المبتسر والعدوى والسياق المحلّي
Caring for a preterm baby follows a small number of principles that explain most of what is done.
رعاية طفل مبتسر تتبع عدداً صغيراً من المبادئ تفسّر معظم ما يُفعَل.
- Abnormal growth of the retinal blood vessels
- Risk related to prematurity and to OXYGEN exposure
- The nursing point: keep saturations within the prescribed target range
- Not higher — higher is not safer
- Screened by ophthalmology on a defined schedule
- Ischaemic, inflammatory bowel injury in a preterm baby
- Feed intolerance, bilious aspirates, abdominal distension
- Blood in the stool, and a baby who becomes systemically unwell
- The nursing point: report distension and bilious aspirate EARLY
- Breast milk is protective — which is why it is prioritised
Neonatal sepsis is the diagnosis a nurse must be able to suspect, because the signs are non-specific and the deterioration is fast.
الإنتان الوليدي تشخيص يجب أن يكون الممرّض قادراً على الاشتباه به، فالعلامات غير نوعية والتدهور سريع.
8.8 · Output, Handover and Moving a Baby٨٫٨ · الإخراج والتسليم ونقل طفل
Wet nappies are the practical measure a mother can use, and they answer the question she cannot otherwise resolve — whether the baby is getting enough. Give her a specific number for each day of the first week, rather than ‘plenty’.
الحفاضات المبتلّة هي المقياس العملي الذي تستطيع أمّ استخدامه وتجيب عن السؤال الذي لا تستطيع حلّه — هل يحصل الطفل على ما يكفي. يُعطى رقم محدّد لكلّ يوم من الأسبوع الأول لا «كثيراً».
Those two absences are assessed rather than watched — they are the presentations of Hirschsprung disease, bowel obstruction, imperforate anus and cystic fibrosis, all of which are better found on day two than on day five.
هذان الغيابان يُقيَّمان لا يُراقَبان — فهما تظاهرات داء هيرشسبرونغ وانسداد الأمعاء والشرج غير المثقوب والتليّف الكيسي وكلّها يكون اكتشافها في اليوم الثاني أفضل منه في اليوم الخامس.
A newborn handover carries a specific risk: the baby cannot tell the next nurse anything, and the mother may assume everything has been passed on.
تسليم الوليد يحمل خطراً محدّداً: أن الطفل لا يستطيع إخبار الطاقم التمريضي التالي بشيء والأمّ قد تفترض أن كلّ شيء نُقل.
Transfer to a neonatal unit follows the same principles as any transfer, with additions specific to a newborn.
النقل إلى وحدة الولدان يتبع مبادئ أيّ نقل مع إضافات خاصّة بالوليد.
8.9 · Watching How They Are Together, and Going Home٨٫٩ · مراقبة كيف هما معاً والعودة للمنزل
Alongside the physical care, a nurse on a postnatal ward is in a position nobody else is: she watches how a mother and her baby are together, repeatedly, over days.
إلى جانب الرعاية البدنية تكون الممرّضة في جناح النفاس في موضع لا يكونه أحد آخر: إذ تشاهد كيف تكون الأمّ وطفلها معاً مراراً عبر أيام.
What it means is usually not what an untrained observer assumes. Before concluding anything about attachment, consider the commoner explanations.
ما يعنيه عادةً ليس ما يفترضه مراقب غير مدرَّب. وقبل استنتاج أيّ شيء عن التعلّق يُنظر في التفسيرات الأشيع.
So the response to a concern is to address the fixable things first — pain relief, sleep, privacy, practical help, someone showing her rather than telling her — and to ask how she is. If a concern persists across shifts after those are addressed, escalate through the proper route rather than recording an opinion in the notes.
فالاستجابة لمبعث القلق هي معالجة الأمور القابلة للإصلاح أولاً — تسكين ونوم وخصوصية ومساعدة عملية وشخص يُريها بدل أن يخبرها — وسؤالها كيف حالها. وإن استمرّ مبعث القلق عبر المناوبات بعد معالجتها يُصعَّد الأمر عبر الطريق المناسب ولا يُسجَّل رأي في السجلّات.
A very young mother needs the same care with two additions: she is more likely to be frightened of appearing not to know what she is doing, so she will not ask — show her rather than wait to be asked; and she is more likely to have everyone in the room talking over her to her own mother — so speak to her, and let her answer.
الأمّ الصغيرة جداً تحتاج الرعاية نفسها مع إضافتين: فهي أرجح أن تخاف من الظهور بمظهر من لا يعرف ما تفعل فلن تسأل — تُوضَّح لها الأمور عملياً بدل انتظار أن تسأل؛ وأرجح أن يتحدّث الجميع في الغرفة من فوقها لأمّها هي — فيُوجَّه الكلام إليها ويُترك لها أن تجيب.
Before discharge, the practical teaching.
قبل الخروج: التعليم العملي.
And the reason it is written: she will be exhausted, and a verbal list at discharge does not survive the first night.
وسبب كونها مكتوبة: أنها ستكون منهكة والقائمة الشفهية عند الخروج لا تنجو من الليلة الأولى.
Test yourselfالاختبار الذاتي
Loading… جارٍ التحميل…
Loading… جارٍ التحميل…
Loading… جارٍ التحميل…