AL-FAHADSNLE PREPARATION
HomeAdult NursingPsychopharmacology & Substance Use
Adult NursingChapter 16 of 17

Psychopharmacology & Substance Use

الأدوية النفسية وتعاطي المواد
بِسْمِ اللّهِ الرَّحْمَٰنِ الرَّحِيمِ
Prayer for knowledgeدعاء طلب العلم
اللَّهُمَّ انْفَعْنِي بِمَا عَلَّمْتَنِي، وَعَلِّمْنِي مَا يَنْفَعُنِي، وَزِدْنِي عِلْمًا“O Allah, benefit me by what You have taught me, teach me what benefits me, and increase me in knowledge.”
«رَبِّ زِدْنِي عِلْمًا»“My Lord, increase me in knowledge.” Qur’an, Ṭā-Hā 20:114 · سورة طه، الآية ١١٤

In this chapterفي هذا الفصل

9 sections · 42 questions · 45 flashcards · 10 clinical casesالأقسام: 9 · الأسئلة: 42 · البطاقات التعليمية: 45 · الحالات السريرية: 10

Key terms (12)المصطلحات الأساسية
Acute dystoniaخلل التوتر العضلي الحاد
An extrapyramidal effect appearing within hours to days of an antipsychotic, with sudden sustained muscle spasm of the neck, jaw or tongue or an oculogyric crisis, which responds within minutes to an anticholinergic.أثر خارج هرمي يظهر خلال ساعات إلى أيام من بدء مضاد الذهان، ويتمثّل بتشنّج عضلي مفاجئ ومستمر في العنق أو الفك أو اللسان أو بأزمة دوران العينين، ويستجيب خلال دقائق لمضاد الكولين.
Akathisiaالأكاثيزيا (تعذّر الجلوس)
An intense, unbearable inner restlessness appearing days to weeks into antipsychotic treatment, often mistaken for anxiety or worsening psychosis, associated with suicide risk and managed by reducing or changing the drug rather than increasing it.تململ داخلي شديد لا يُحتمل يظهر بعد أيام إلى أسابيع من العلاج بمضاد الذهان، وكثيراً ما يُخلط بينه وبين القلق أو تفاقم الذهان، ويرتبط بخطر الانتحار، ويُدبَّر بتخفيض الدواء أو تغييره لا بزيادته.
Tardive dyskinesiaخلل الحركة المتأخر
Involuntary repetitive movements of the mouth, tongue and face, such as lip smacking, chewing and tongue protrusion, appearing after months to years of antipsychotic use and often irreversible, so early recognition and reporting is essential.حركات لاإرادية متكررة في الفم واللسان والوجه، مثل مصمصة الشفتين والمضغ وبروز اللسان، تظهر بعد أشهر إلى سنوات من استعمال مضاد الذهان وكثيراً ما لا تُعكس، ولذلك فإن التعرّف المبكر والإبلاغ أمران أساسيان.
Neuroleptic malignant syndromeالمتلازمة الخبيثة لمضادات الذهان
An emergency developing over hours to days on an antipsychotic, with high fever, lead-pipe rigidity, altered consciousness, autonomic instability and raised creatine kinase, requiring the drug to be stopped and urgent escalation.حالة إسعافية تتطور خلال ساعات إلى أيام لدى مريض يتناول مضاد الذهان، وتتميّز بحمّى مرتفعة وتصلّب كأنبوب الرصاص واضطراب الوعي وعدم استقرار الجهاز العصبي الذاتي وارتفاع كيناز الكرياتين، وتستوجب إيقاف الدواء والتصعيد العاجل.
Agranulocytosis (clozapine)ندرة المحبّبات (مع الكلوزابين)
A severe fall in neutrophils (a type of white cell) that leaves the patient defenceless against infection, which is why clozapine is dispensed only under strict medical supervision with mandatory blood counts, and fever or sore throat must be reported immediately.انخفاض شديد في العدلات (وهي نوع من كريات الدم البيضاء) يترك المريض بلا دفاع أمام العدوى، ولهذا لا يُصرف الكلوزابين إلا تحت إشراف طبي صارم مع تعداد دم إلزامي، ويجب الإبلاغ الفوري عن الحمّى أو التهاب الحلق.
QT prolongationإطالة فاصل QT
A cardiac effect of several antipsychotics that raises the risk of a dangerous arrhythmia, worsened by low potassium and low magnesium, and managed with baseline and follow-up ECGs where indicated and caution with other QT-prolonging drugs.أثر قلبي لعدد من مضادات الذهان يزيد خطر اضطراب النظم الخطير، ويتفاقم بانخفاض البوتاسيوم والمغنيسيوم، ويُدبَّر بتخطيط قلب أساسي وآخر لاحق عند وجود استطباب مع الحذر من الأدوية الأخرى المطيلة لفاصل QT.
Lithium toxicityسُمّية الليثيوم
Toxicity of a narrow-therapeutic-index drug, signalled by a change from the expected fine tremor to a coarse tremor with vomiting, diarrhoea, ataxia and confusion, and raised by dehydration, low salt, NSAIDs, ACE inhibitors and thiazide diuretics.سُمّية دواء ضيّق المؤشر العلاجي، تُنذر بها الرعشة الخشنة بدلاً من الرعشة الدقيقة المتوقعة مع القيء والإسهال والرنح والتخليط، وتزيدها حالات الجفاف وقلة الملح ومضادات الالتهاب غير الستيرويدية ومثبّطات الإنزيم المحوِّل للأنجيوتنسين ومدرّات الثيازيد.
Serotonin syndromeمتلازمة السيروتونين
An emergency caused by excess serotonergic activity, developing over hours with hyperreflexia, clonus, agitation, dilated pupils, diarrhoea and fever, which differs from neuroleptic malignant syndrome that develops over days with lead-pipe rigidity.حالة إسعافية ناجمة عن فرط النشاط السيروتونيني، تتطور خلال ساعات مع فرط المنعكسات والرمع والهياج واتساع الحدقتين والإسهال والحمّى، وتختلف عن المتلازمة الخبيثة لمضادات الذهان التي تتطور خلال أيام مع تصلّب كأنبوب الرصاص.
Delirium tremensالهذيان الارتعاشي
The most dangerous and potentially fatal complication of alcohol withdrawal, appearing at 48–72 hours with severe confusion, vivid hallucinations believed to be real, marked tremor, agitation and autonomic instability.أخطر مضاعفات انسحاب الكحول وقد يكون مميتاً، يظهر بعد 48 إلى 72 ساعة مع تخليط شديد وهلاوس حيّة يعتقد المريض بحقيقتها ورعشة بارزة وهياج وعدم استقرار الجهاز العصبي الذاتي.
Wernicke encephalopathyاعتلال فيرنيكه الدماغي
An acute, treatable emergency of thiamine deficiency with confusion, ataxia and eye signs, precipitated by giving glucose before thiamine and progressing if untreated to Korsakoff syndrome, a permanent memory disorder with confabulation.حالة إسعافية حادة قابلة للعلاج ناجمة عن نقص الثيامين، تتظاهر بتخليط ورنح وعلامات عينية، ويُحرِّضها إعطاء الغلوكوز قبل الثيامين، وتتطور إن لم تُعالَج إلى متلازمة كورساكوف، وهي اضطراب ذاكرة دائم مع الاختلاق.
Lost tolerance (opioid overdose risk)فقدان التحمّل (خطر الجرعة الزائدة من الأفيونيات)
The rapid fall in tolerance after a period of abstinence, after which returning to the usual dose becomes an overdose, so the period after detoxification, discharge or custody is the highest-risk time and take-home naloxone is provided where the service does.الانخفاض السريع في التحمّل بعد فترة امتناع، بحيث تصبح العودة إلى الجرعة المعتادة جرعة زائدة، ولذلك تكون الفترة التالية للإزالة السمّية أو الخروج أو الاحتجاز أعلى الفترات خطراً ويُزوَّد المريض بالنالوكسون ليأخذه معه إلى المنزل حيثما تقدّمه الخدمة.
Harm reductionتقليل الضرر
The principle that reducing the damage caused by substance use is a legitimate clinical goal even where stopping is not achieved, including needle and syringe provision, blood-borne virus testing, vaccination and overdose education.مبدأ يعدّ الحدّ من الضرر الناجم عن تعاطي المواد هدفاً سريرياً مشروعاً حتى لو لم يتحقق التوقف، ويشمل توفير الإبر والمحاقن والفحص عن الفيروسات المنقولة بالدم والتطعيم والتثقيف حول الجرعة الزائدة.
Chapter outline (9 sections)مخطط الفصل
  1. Learning Objectivesأهداف التعلّم
  2. 16.1 · Antipsychotics and Their Movement Effects١٦٫١ · مضادّات الذهان وآثارها الحركية
  3. 16.2 · Clozapine and Long-Acting Injections١٦٫٢ · الكلوزابين والحقن طويلة المفعول
  4. 16.3 · Giving Psychotropic Medicines Safely١٦٫٣ · إعطاء الأدوية النفسية بأمان
  5. 16.4 · Lithium and Other Mood Stabilisers١٦٫٤ · الليثيوم ومثبّتات المزاج الأخرى
  6. 16.5 · Antidepressants, Anxiolytics and Serotonin Syndrome١٦٫٥ · مضادّات الاكتئاب ومزيلات القلق ومتلازمة السيروتونين
  7. 16.6 · Alcohol and Its Withdrawal١٦٫٦ · الكحول وانسحابه
  8. 16.7 · Opioids, Harm Reduction and Relapse١٦٫٧ · الأفيونيات وتقليل الضرر والنكس
  9. 16.8 · Substance Use in the Saudi Setting١٦٫٨ · تعاطي المواد في السياق السعودي

Start learningبدء التعلّم Learning objectivesأهداف التعلّم Test yourselfالاختبار الذاتي

Learning Objectivesأهداف التعلّم

1
Explain how long antipsychotics take to work and what to tell the patient.
بيان المدة التي تستغرقها مضادّات الذهان لتعمل وما يُقال للمريض.
2
Distinguish the extrapyramidal side effects by their timing.
التمييز بين الآثار خارج الهرمية بتوقيتها.
3
Recognise acute dystonia and state its treatment.
تمييز خلل التوتّر الحادّ وذكر علاجه.
4
Recognise akathisia and explain why it is misread.
تمييز تعذّر الجلوس وبيان لماذا يُساء قراءته.
5
Recognise tardive dyskinesia and explain why the dose is not increased.
تمييز خلل الحركة المتأخّر وبيان لماذا لا تُزاد الجرعة.
6
Recognise neuroleptic malignant syndrome and respond to it.
تمييز المتلازمة الخبيثة لمضادّات الذهان والاستجابة لها.
7
State the monitoring required for clozapine and why.
ذكر المراقبة المطلوبة للكلوزابين ولماذا.
8
Explain the risks of clozapine beyond agranulocytosis.
بيان مخاطر الكلوزابين الأخرى غير ندرة المحبّبات.
9
Explain what happens when clozapine doses are missed.
بيان ما يحدث حين تُفوَّت جرعات الكلوزابين.
10
Describe the nursing care of a long-acting injection.
وصف الرعاية التمريضية لحقنة طويلة المفعول.
11
Distinguish a fine from a coarse tremor in a lithium patient.
التمييز بين الرعاش الناعم والخشن لدى مريض يتناول الليثيوم.
12
List the signs of lithium toxicity.
سرد علامات سمّية الليثيوم.
13
State what raises the lithium level.
ذكر ما يرفع مستوى الليثيوم.
14
Teach a lithium patient about salt, fluid and other medicines.
تعليم مريض الليثيوم عن الملح والسوائل والأدوية الأخرى.
15
State the monitoring required for lithium.
ذكر المراقبة المطلوبة لليثيوم.
16
Explain why suicide risk rises early in antidepressant treatment.
بيان لماذا يرتفع خطر الانتحار مبكّراً في علاج مضادّ الاكتئاب.
17
Recognise serotonin syndrome.
تمييز متلازمة السيروتونين.
18
Distinguish serotonin syndrome from neuroleptic malignant syndrome.
التمييز بين متلازمة السيروتونين والمتلازمة الخبيثة لمضادّات الذهان.
19
Explain antidepressant discontinuation symptoms.
شرح أعراض انقطاع مضادّ الاكتئاب.
20
Explain the risks of benzodiazepines and why they are tapered.
بيان مخاطر البنزوديازيبينات ولماذا تُخفَّض تدريجياً.
21
Describe the alcohol withdrawal timeline.
وصف الخطّ الزمني لانسحاب الكحول.
22
Recognise delirium tremens as the most dangerous complication.
تمييز الهذيان الارتعاشي كأخطر مضاعفة.
23
Explain why thiamine is given before glucose.
بيان لماذا يُعطى الثيامين قبل الغلوكوز.
24
Distinguish Wernicke encephalopathy from Korsakoff syndrome.
التمييز بين اعتلال دماغ فيرنيكه ومتلازمة كورساكوف.
25
Apply the Saudi context: which substances predominate and how to ask.
تطبيق السياق السعودي: أيّ المواد تسود وكيف يُسأل.

16.1 · Antipsychotics and Their Movement Effects١٦٫١ · مضادّات الذهان وآثارها الحركية

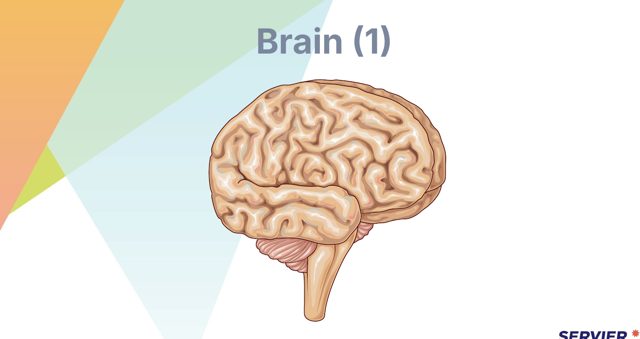
Lateral view of the brain: cerebral hemisphere, cerebellum and brainstem
Lateral view of the brain: cerebral hemisphere, cerebellum and brainstemمنظر جانبي للدماغ: نصف الكرة المخية والمخيخ وجذع الدماغServier Medical Art · CC BY 4.0

Antipsychotics treat the positive symptoms of psychosis — hallucinations, delusions and thought disorder — and are used in schizophrenia, in mania and sometimes for severe agitation. Two expectations must be set at the start: the full effect takes weeks, and side effects usually arrive before the benefit does. A patient who is not told that stops taking them.

ومضادات الذهان تعالج الأعراض الإيجابية للذهان — هلوسات وأوهام واضطراب تفكير — وتُستخدَم في الفصام والهوس وأحياناً للهياج الشديد. ويجب وضع توقّعين في البداية: أن الأثر الكامل يستغرق أسابيع، وأن الآثار الجانبية تصل عادةً قبل الفائدة. والمريض الذي لا يُخبَر بذلك يتوقّف عن تناولها.

The extrapyramidal side effects are the group to know, and they are distinguished by when they appear.

والآثار خارج الهرمية المجموعة الواجب معرفتها وتُميَّز بحسب وقت ظهورها.

1
Acute dystonia — hours to days
A sudden sustained muscle spasm: neck twisting, jaw or tongue, and the frightening oculogyric crisis with the eyes rolled upward. Distressing and treatable — an anticholinergic works within minutes. Reassure him it will pass.
خلل التوتّر الحادّ — ساعات لأيام: تشنّج عضلي مفاجئ مستمرّ: التواء العنق، وتشنّج الفكّ أو اللسان، والأزمة المخيفة لدوران العينين مع انقلابهما إلى الأعلى. حالة مزعجة وقابلة للعلاج — فمضادّ الكولين يعمل خلال دقائق. ويُطمأَن المريض بأنها ستزول.
2
Akathisia — days to weeks
Intense inner restlessness — he cannot sit still, paces, rocks, and describes an unbearable feeling. The one most often misread.
تعذّر الجلوس — أيام لأسابيع: تململ داخلي شديد — لا يستطيع المريض الجلوس بهدوء، فيذرع المكان جيئةً وذهاباً ويتمايل، ويصف شعوراً لا يُحتمل. وهو الأكثر عرضةً لإساءة القراءة.
3
Parkinsonism — weeks
Tremor, rigidity, bradykinesia, shuffling gait, mask-like face.
الباركنسونية — أسابيع: رعاش وصلابة وبطء حركة ومشية متجرجرة ووجه قناعي.
4
Tardive dyskinesia — months to years
Involuntary repetitive movement, characteristically of the mouth, tongue and face: lip smacking, chewing, tongue protrusion. Often irreversible — so early recognition and reporting is the whole nursing contribution.
خلل الحركة المتأخّر — أشهر لسنوات: حركات لا إرادية متكرّرة، تصيب عادةً الفم واللسان والوجه: مصمصة الشفتين والمضغ وبروز اللسان. وهي غير عكوسة غالباً — ولذلك فإن التعرّف المبكر والإبلاغ هما المساهمة التمريضية كلّها.

Akathisia deserves its own warning, because misreading it makes it worse.

وتعذّر الجلوس يستحقّ تحذيراً خاصّاً، فإساءة قراءته تزيده سوءاً.

❌What it is mistaken for
  • Anxiety, or the psychosis worsening
  • Agitation needing more antipsychotic
  • ‘Attention-seeking’ or non-compliance
  • So the dose is increased — and it gets worse
ما يُظَنّ أنه — قلق أو تفاقم للذهان؛ أو هياج يحتاج إلى مزيد من مضادّ الذهان؛ أو «طلب للانتباه» أو عدم التزام بالعلاج؛ فتُزاد الجرعة — ويسوء الحال.
✅What it actually is
  • A drug side effect, not a symptom
  • An unbearable inner restlessness he can describe
  • Associated with suicide risk — it is genuinely intolerable
  • Managed by reducing or changing the drug
ما هو فعلاً — أثر جانبي لدواء وليس عَرَضاً مرضياً؛ تململ داخلي لا يُحتمل يستطيع المريض وصفه؛ يرتبط بخطر الانتحار — فهو لا يُطاق فعلاً؛ ويُدبَّر بتقليل الدواء أو تغييره.

Neuroleptic malignant syndrome is the emergency of this drug group. It develops over hours to days.

والمتلازمة الخبيثة لمضادات الذهان الحالة الإسعافية لهذه المجموعة. وتتطوّر عبر ساعات لأيام.

High feveroften markedحمّى عالية — شديدة الارتفاع غالباً
‘Lead-pipe’ rigiditysevere and generalisedصلابة «أنبوب الرصاص» — شديدة ومعمّمة
Altered consciousnessconfusion, then reduced levelتغيّر الوعي — ارتباك ثم انخفاض مستوى الوعي
Autonomic instabilityunstable pulse and blood pressure, sweatingعدم استقرار الجهاز العصبي المستقل — تذبذب النبض وضغط الدم وتعرّق
↑ CKraised creatine kinase, risk of renal failureارتفاع كيناز الكرياتين — خطر الفشل الكلوي

Stop the antipsychotic and escalate immediately. Supportive care is cooling, fluids and monitoring, and the risk that follows the rigidity is rhabdomyolysis and acute kidney injury — which is why the creatine kinase and the urine output matter as much as the temperature.

يُوقَف مضادّ الذهان ويُصعَّد الأمر فوراً. والرعاية الداعمة هي التبريد والسوائل والمراقبة، والخطر الذي يلي الصلابة هو انحلال الربيدات والأذى الكلوي الحادّ — ولهذا يهمّ كيناز الكرياتين والنتاج البولي بقدر ما تهمّ الحرارة.

🔑
Memory aid
مفتاح للحفظ
Timing separates the extrapyramidal effects: acute dystonia within hours to days, akathisia and parkinsonism over days to weeks, tardive dyskinesia after months to years.
التوقيت يفصل الآثار خارج الهرمية: خلل التوتّر الحادّ خلال ساعات إلى أيام وتعذّر الجلوس والباركنسونية عبر أيام إلى أسابيع وخلل الحركة المتأخّر بعد أشهر إلى سنوات.
🚩
Watch out
تنبيه
Akathisia looks like agitation and is often treated by increasing the antipsychotic, which makes it worse. It is profoundly distressing and is associated with an increased suicide risk.
تعذّر الجلوس يبدو كهياج ويُعالَج غالباً بزيادة مضادّ الذهان، مما يزيده سوءاً. وهو يسبّب كرباً شديداً ويرتبط بزيادة خطر الانتحار.
🚩
Watch out
تنبيه
Never increase the antipsychotic dose to suppress tardive dyskinesia. It masks the movements temporarily while making the underlying problem worse.
لا تُزاد جرعة مضادّ الذهان أبداً لكبت خلل الحركة المتأخّر؛ فزيادتها تُخفي الحركات مؤقّتاً بينما تُفاقم المشكلة الكامنة.
🚩
Watch out
تنبيه
Fever with severe rigidity and altered consciousness in a patient on an antipsychotic is neuroleptic malignant syndrome until proved otherwise. Stop the drug and escalate urgently.
الحمّى مع صلابة شديدة وتغيّر في الوعي لدى مريض يتناول مضادّ ذهان تُعامَل كالمتلازمة الخبيثة لمضادّات الذهان حتى يثبت العكس. يُوقَف الدواء ويُصعَّد الأمر عاجلاً.

16.2 · Clozapine and Long-Acting Injections١٦٫٢ · الكلوزابين والحقن طويلة المفعول

Clozapine is used for schizophrenia that has not responded to other antipsychotics, and it is often effective where nothing else has been. It is also the antipsychotic with the most demanding monitoring, and every requirement exists because of a specific death.

والكلوزابين يُستخدَم لفصام لم يستجب لمضادات الذهان الأخرى وكثيراً ما يكون فعّالاً حيث لم ينجح غيره. وهو أيضاً مضادّ الذهان ذو المراقبة الأكثر تطلّباً وكلّ اشتراط موجود بسبب وفاة محدّدة.

•The four risks — each has killed patients◆ المخاطر الأربعة — وقد أودى كلٌّ منها بحياة مرضى
AgranulocytosisA severe fall in the white cells leaving him defenceless against infection. This is why clozapine is given only under strict medical supervision with regular blood counts — white cell and neutrophil (WBC/ANC) counts weekly for the first 18 weeks, then at least every four weeks. Teach him to report fever, sore throat or any infection immediately.ندرة المحبّبات — هبوط شديد في كريات الدم البيضاء يترك المريض بلا دفاع أمام العدوى. ولهذا لا يُعطى الكلوزابين إلا تحت إشراف طبي صارم مع فحوص دم منتظمة — تعداد كريات الدم البيضاء والعدلات (WBC/ANC) أسبوعياً خلال أول ١٨ أسبوعاً، ثم كل أربعة أسابيع على الأقل. ويُعلَّم المريض الإبلاغ فوراً عن الحمّى أو التهاب الحلق أو أيّ عدوى.
MyocarditisMainly in the first weeks. Chest pain, breathlessness, palpitations, fever — or simply feeling unwell. Easily attributed to something else at exactly the point it is most dangerous.التهاب العضلة القلبية — يحدث غالباً في الأسابيع الأولى. ألم الصدر وضيق النفس وخفقان القلب والحمّى — أو مجرّد الشعور بالتوعّك. ويُنسَب بسهولة إلى شيء آخر في اللحظة التي يكون فيها أشدّ خطورة.
ConstipationSounds trivial and is not: it can progress to ileus, obstruction and death. Ask about bowels routinely and specifically, and treat it actively.الإمساك — يبدو تافهاً وليس كذلك: قد يتقدّم إلى علوص وانسداد ووفاة. ويُسأل عن حركة الأمعاء بانتظام وبصورة محدّدة، ويُعالَج بفاعلية.
Seizures and sedationDose-related, and hypersalivation is common and distressing.الاختلاجات والتهدئة — مرتبطة بالجرعة، وفرط اللعاب شائع ومزعج.

One practical rule catches people out: if a patient misses clozapine for more than about 48 hours, it cannot simply be restarted at his usual dose — tolerance is lost quickly, and restarting at the full dose risks profound hypotension, sedation and collapse. It must be re-titrated from a low dose. So a missed weekend, a hospital admission where it was not prescribed, or a spell in another department is a clinical event, not an administrative gap.

وهناك قاعدة عملية يُخطئ فيها كثيرون: إذا فات المريضَ الكلوزابين أكثر من نحو ٤٨ ساعة فلا يمكن استئنافه ببساطة بجرعته المعتادة — فالتحمّل يُفقَد بسرعة، وقد يؤدي الاستئناف بالجرعة الكاملة إلى هبوط شديد في ضغط الدم وتهدئة وانهيار. بل يجب إعادة معايرته من جرعة منخفضة. فتفويت الجرعات خلال عطلة نهاية الأسبوع، أو التنويم الذي لم يُوصَف فيه الدواء، أو قضاء فترة في قسم آخر، كلّها حدث سريري وليست فجوة إدارية.

📅Long-acting injection — the benefit
  • Given every few weeks
  • Removes the daily decision to take it
  • Adherence is known, not assumed
  • Useful where relapse follows every missed period
الحقنة طويلة المفعول — الفائدة: يُعطى كلّ بضعة أسابيع؛ ويُزيل قرار تناول الدواء اليومي؛ والالتزام معروف لا مفترَض؛ ويفيد حيث يعقب النكسُ كلَّ فترة يُفوَّت فيها الدواء.
⏳— and the consequence
  • A side effect cannot be stopped by omitting a dose
  • It has to be waited out
  • So the first dose is given cautiously
  • and he is observed — including after each dose
والعاقبة: لا يمكن إيقاف الأثر الجانبي بإغفال جرعة، بل يجب انتظار زواله؛ لذا تُعطى الجرعة الأولى بحذر، ويُراقَب المريض — بما في ذلك بعد كلّ جرعة.
🚩
Watch out
تنبيه
A sore throat, fever or flu-like illness in a patient on clozapine is treated as possible agranulocytosis until the blood count is checked.
التهاب الحلق أو الحمّى أو مرض شبيه بالإنفلونزا لدى مريض يتناول الكلوزابين يُعامَل كندرة محبّبات محتملة حتى يُفحَص تعداد الدم.
🚩
Watch out
تنبيه
Clozapine constipation is not trivial — untreated it progresses to impaction, bowel obstruction and death. Ask about bowels by name at every review and treat early.
إمساك الكلوزابين ليس تافهاً — فبلا علاج يتقدّم لانحشار وانسداد أمعاء وموت. يُسأل عن الأمعاء بالاسم في كلّ مراجعة ويُعالَج الإمساك مبكّراً.
🚩
Watch out
تنبيه
Clozapine missed for more than about forty-eight hours must be re-titrated from a low dose, not restarted at the usual dose. Ask when he last took it before administering.
الكلوزابين المفوَّت أكثر من نحو ثمانٍ وأربعين ساعة يجب إعادة معايرته من جرعة منخفضة لا استئنافه بالجرعة المعتادة. يُسأل المريض عن موعد آخر جرعة تناولها قبل الإعطاء.
⭐
Key point
نقطة أساسية
A side effect from a depot injection cannot be stopped by withholding the next dose, because the drug is already in the body.
الأثر الجانبي من حقنة مستودع لا يمكن إيقافه بحجب الجرعة التالية، فالدواء في الجسم أصلاً.

16.3 · Giving Psychotropic Medicines Safely١٦٫٣ · إعطاء الأدوية النفسية بأمان

Several administration issues are specific to this group of drugs.

وعدّة مسائل إعطاء خاصّة بهذه المجموعة من الأدوية.

•Administration points particular to psychotropics◆ نقاط الإعطاء الخاصّة بالأدوية النفسية
Cheeking and concealmentA patient who does not want the medication may hold the tablet in his cheek or under his tongue and remove it afterwards. Where there is a concern, check the mouth, or use a liquid or orodispersible preparation.إخفاء الدواء في الخدّ — قد يحتفظ المريض الذي لا يرغب في تناول الدواء بالقرص في خدّه أو تحت لسانه ثم يُخرجه لاحقاً. وعند وجود قلق يُفحَص الفم، أو يُستخدَم مستحضر سائل أو سريع الذوبان في الفم.
After rapid tranquillisationHe is at risk of over-sedation and respiratory depression. Monitor level of consciousness, respiratory rate, oxygen saturation, pulse and blood pressure at the specified intervals — and do not leave him unobserved because he is now quiet.بعد التهدئة السريعة — خطر الإفراط في التهدئة وتثبيط التنفّس. يُراقَب مستوى الوعي ومعدّل التنفّس وتشبّع الأكسجين والنبض وضغط الدم في الفترات المحدّدة، ولا يُترك المريض دون مراقبة لمجرّد أنه أصبح هادئاً.
Postural hypotensionCommon with many psychotropics, particularly when starting or increasing a dose — and it is a direct falls risk. Teach rising slowly, lying to sitting and sitting to standing, and check a lying and standing blood pressure.هبوط الضغط الوضعي — شائع مع كثير من الأدوية النفسية، خاصّةً عند البدء بالجرعة أو زيادتها — وهو خطر مباشر للسقوط. يُعلَّم المريض النهوض ببطء، من الاستلقاء إلى الجلوس ثم من الجلوس إلى الوقوف، ويُقاس ضغط الدم مستلقياً وواقفاً.
❤️Cardiac — QT prolongation
  • Several antipsychotics prolong the QT interval
  • Raising the risk of a dangerous arrhythmia
  • So a baseline and subsequent ECG where indicated
  • And caution with other QT-prolonging drugs — check before adding
قلبياً — إطالة QT: تُطيل عدّة مضادّات ذهان فترة QT، مما يرفع خطر اضطراب نظم خطير؛ لذا يُجرى تخطيط قلب أساسي وآخر لاحق عند الاقتضاء، مع الحذر من الأدوية الأخرى المُطيلة لـ QT — ويُتحقَّق منها قبل إضافتها.
⚖️Metabolic
  • Weight gain, dyslipidaemia and impaired glucose tolerance
  • Particularly with several second-generation antipsychotics
  • So weight, glucose and lipids are monitored
  • Not as an afterthought — this is what shortens these patients’ lives
استقلابياً — زيادة الوزن واضطراب شحوم الدم وضعف تحمّل الغلوكوز، خاصّةً مع عدّة مضادّات ذهان من الجيل الثاني؛ لذا يُراقَب الوزن والغلوكوز والشحوم — لا كأمر ثانوي، فهذا ما يُقصّر أعمار هؤلاء المرضى.

Finally, an interaction that is regularly missed and can cause serious toxicity: smoking induces the enzyme that metabolises clozapine, so a patient who smokes needs a higher dose to reach the same level.

وأخيراً تداخل يُغفَل بانتظام وقد يسبّب سميّةً خطيرة: أن التدخين يحفّز الإنزيم الذي يستقلب الكلوزابين، فالمريض المدخّن يحتاج جرعةً أعلى لبلوغ المستوى نفسه.

1
So when he stops smoking
The enzyme is no longer induced.
فحين يتوقّف عن التدخين — لم يعد الإنزيم محفَّزاً.
2
The level RISES on the same dose
Sometimes sharply.
يرتفع المستوى بالجرعة نفسها — أحياناً بحدّة.
3
And this happens on admission
To a smoke-free hospital — the commonest way it occurs, and nobody plans for it.
وهذا يحدث عند التنويم — في مستشفى خالٍ من التدخين: وهي الطريقة الأشيع لحدوثه، ولا أحد يخطّط لها.
4
So flag it and monitor
A patient on clozapine who stops or reduces smoking needs the level checked and the dose reviewed.
لذا يُنبَّه إلى ذلك ويُراقَب المريض — فالمريض الذي يتناول الكلوزابين ويتوقّف عن التدخين أو يقلّله يحتاج إلى فحص المستوى ومراجعة الجرعة.
🚩
Watch out
تنبيه
Smoking induces the enzyme that metabolises clozapine. Stopping smoking suddenly — as on admission to a smoke-free hospital — makes the clozapine level rise sharply and it can become toxic.
التدخين يحفّز الإنزيم الذي يستقلب الكلوزابين. والتوقّف المفاجئ عن التدخين — كما عند التنويم في مستشفى خالٍ من التدخين — يجعل مستوى الكلوزابين يرتفع بحدّة وقد يصير سامّاً.
⭐
Key point
نقطة أساسية
QT prolongation from antipsychotics is made worse by a low potassium and a low magnesium, so correcting them is part of managing the cardiac risk rather than a separate task.
إطالة QT من مضادّات الذهان تسوء بانخفاض البوتاسيوم والمغنيسيوم، فتصحيحهما جزء من تدبير الخطر القلبي لا مهمّة منفصلة.
🔑
Memory aid
مفتاح للحفظ
Anticholinergic effects: dry mouth, blurred vision, constipation, urinary retention and confusion in older people. The dry mouth causes dental decay, so mouth care belongs in the plan.
الآثار المضادّة للكولين: جفاف الفم وعدم وضوح الرؤية والإمساك واحتباس البول والتشوّش لدى كبار السنّ. وجفاف الفم يسبّب تسوّس الأسنان، لذا ينبغي إدراج العناية بالفم في الخطة.
⭐
Key point
نقطة أساسية
Where a patient is reluctant to take medication, use a liquid or dispersible preparation and ask why — the reason is usually addressable and more useful than winning the round.
عند ممانعة المريض في تناول الدواء يُستخدَم مستحضر سائل أو سريع الذوبان ويُسأل عن السبب — فالسبب قابل للمعالجة عادةً وأنفع من كسب الجولة.

16.4 · Lithium and Other Mood Stabilisers١٦٫٤ · الليثيوم ومثبّتات المزاج الأخرى

Lithium is highly effective in bipolar disorder and reduces suicide risk. It has a narrow therapeutic index — the gap between an effective level and a toxic one is small — which is why it is monitored by blood level rather than by response alone.

والليثيوم شديد الفعالية في اضطراب ثنائي القطب ويقلّل خطر الانتحار. وله مؤشّر علاجي ضيّق — فالفجوة بين مستوى فعّال وسامّ صغيرة — ولهذا يُراقَب بمستوى الدم لا بالاستجابة وحدها.

Recognising toxicity is the examinable skill, and the tremor is the key that unlocks it.

وتمييز السميّة المهارة القابلة للاختبار والرعاش هو المفتاح.

✅Therapeutic level
  • FINE tremor of the hands — common and expected
  • Mild thirst and increased urine output
  • Nausea early in treatment
  • Weight gain; a metallic taste
المستوى العلاجي — رعاش ناعم لليدين شائع ومتوقّع؛ وعطش خفيف وزيادة في إدرار البول؛ وغثيان في بداية العلاج؛ وزيادة في الوزن وطعم معدني في الفم.
🚨Toxicity
  • COARSE tremor — the change that signals it
  • Vomiting and diarrhoea
  • Ataxia, slurred speech, drowsiness
  • Confusion, then seizures and coma
  • Withhold the dose, check a level, escalate
السميّة — رعاش خشن، وهو التغيّر الذي يدلّ عليها؛ وتقيّؤ وإسهال؛ ورنح وثقل في الكلام ونعاس؛ ثم ارتباك فاختلاجات وغيبوبة: تُحجَب الجرعة ويُفحَص مستوى الليثيوم ويُصعَّد الأمر.

Fine to coarse is the transition to teach and to watch for. Vomiting and diarrhoea are doubly dangerous, because they are both a sign of toxicity and a cause of it — fluid loss concentrates the lithium further.

والانتقال من الناعم إلى الخشن هو ما ينبغي تعليمه وترقّبه. والتقيّؤ والإسهال خطران بدرجة مضاعفة، فهما علامة على السميّة وسبب لها — إذ يزيد فقد السوائل من تركيز الليثيوم.

The teaching that prevents toxicity is about salt and water, and it is the most important thing a nurse tells a lithium patient. Lithium is handled by the kidney in a way that follows sodium: when sodium falls or the patient is dehydrated, the kidney retains lithium and the level rises.

والتعليم الذي يمنع السميّة يدور حول الملح والماء، وهو أهمّ ما يقوله الممرّض لمريض يتناول الليثيوم. فالكلية تتعامل مع الليثيوم بطريقة تتبع الصوديوم: فحين ينخفض الصوديوم أو يُصاب المريض بالجفاف تحتفظ الكلية بالليثيوم فيرتفع المستوى.

•What raises the level — all avoidable, all worth naming◆ ما يرفع المستوى — وكلّه يمكن تجنّبه، وكلّه يستحقّ أن يُسمّى صراحةً
DehydrationVomiting, diarrhoea, fever, sweating — and hot weather, which matters particularly here.الجفاف — تقيّؤ وإسهال وحمّى وتعرّق — والطقس الحارّ، وهذا يهمّ بوجه خاصّ هنا.
A sudden change in salt intakeConsistent salt intake matters more than low or high — a new low-salt diet raises the level.تغيّر مفاجئ في تناول الملح — ثبات تناول الملح أهمّ من كونه منخفضاً أو مرتفعاً — فاتّباع حمية جديدة قليلة الملح يرفع مستوى الليثيوم.
Certain drugsNSAIDs, ACE inhibitors and thiazide diuretics all raise the lithium level — so check before any new prescription, including anything bought over the counter.أدوية معيّنة — مضادات الالتهاب اللاستيرويدية ومثبّطات الإنزيم المحوّل للأنجيوتنسين والمدرّات الثيازيدية، وكلّها ترفع مستوى الليثيوم — لذا يُتحقَّق قبل أيّ وصفة جديدة، بما في ذلك ما يُشترى دون وصفة طبية.
So the adviceMaintain consistent fluid and salt intake, drink more in hot weather or illness, and report vomiting or diarrhoea rather than pushing through it.فالنصيحة — المحافظة على تناول ثابت للسوائل والملح، وشرب المزيد في الطقس الحارّ أو أثناء المرض، والإبلاغ عن التقيّؤ أو الإسهال بدلاً من تحمّلهما.

Other mood stabilisers include certain antiepileptic drugs, and one point about them matters above all others: several are teratogenic. So contraception and pre-conception counselling belong in the treatment plan for any woman of childbearing potential — at the time it is prescribed, not when she becomes pregnant. Lithium also requires thyroid and renal function monitoring, because long-term use affects both.

ومثبّتات المزاج الأخرى تشمل بعض الأدوية المضادّة للصرع، ونقطة واحدة بشأنها تفوق غيرها أهمية: أن عدّة منها مسبّبة لتشوّه الأجنّة. لذا ينبغي إدراج منع الحمل والاستشارة قبل الحمل في خطة العلاج لأيّ امرأة في سنّ الإنجاب — عند وصف الدواء لا حين تحمل. كما يتطلّب الليثيوم مراقبة وظائف الدرقية والكلية، لأن الاستخدام طويل الأمد يؤثّر في كليهما.

🔑
Memory aid
مفتاح للحفظ
A fine tremor is an expected side effect of lithium at therapeutic level. A coarse tremor is a sign of toxicity — that distinction is what questions turn on.
الرعاش الناعم أثر جانبي متوقّع لليثيوم عند المستوى العلاجي. والرعاش الخشن علامة سمّية — وذلك التمييز ما تدور عليه الأسئلة.
🚩
Watch out
تنبيه
Dehydration, low salt, vomiting, diarrhoea, fever, hot weather and heavy sweating all raise the lithium level. So do non-steroidal anti-inflammatories and certain diuretics.
الجفاف ونقص الملح والتقيّؤ والإسهال والحمّى والجوّ الحارّ والتعرّق الغزير كلّها ترفع مستوى الليثيوم. وكذلك مضادّات الالتهاب غير الستيرويدية وبعض المدرّات.
⭐
Key point
نقطة أساسية
The lithium level is taken about twelve hours after the dose, consistently. A sample drawn at the wrong time gives a number that is meaningless.
مستوى الليثيوم يُؤخذ بعد نحو اثنتي عشرة ساعة من الجرعة باتّساق. والعيّنة المسحوبة في الوقت الخطأ تعطي رقماً بلا معنى.

16.5 · Antidepressants, Anxiolytics and Serotonin Syndrome١٦٫٥ · مضادّات الاكتئاب ومزيلات القلق ومتلازمة السيروتونين

Antidepressants take about two to four weeks to produce a meaningful effect on mood, and often longer for the full benefit — while the side effects arrive first, typically nausea, headache, sleep disturbance and agitation. Saying that plainly is what keeps a patient on them through the fortnight when the drug is all cost and no benefit.

ومضادات الاكتئاب تستغرق نحو أسبوعين إلى أربعة أسابيع لإحداث أثر ذي معنى على المزاج، وأطول من ذلك للفائدة الكاملة — بينما تصل الآثار الجانبية أولاً، وهي عادةً الغثيان والصداع واضطراب النوم والهياج. وقول ذلك بوضوح ما يُبقي مريضاً عليها خلال الأسبوعين اللذين يكون فيهما الدواء كلّه كلفة بلا فائدة.

•Two safety points about starting them◆ نقطتا سلامة عند بدء استخدامها
The early risk periodEnergy and motivation may return before mood does — which can mean a patient becomes able to act on thoughts he already had. Monitoring is closest in the first weeks, and particularly in young people.فترة الخطر المبكّرة — قد تعود الطاقة والدافعية قبل المزاج، مما قد يعني أن يصبح المريض قادراً على تنفيذ أفكار كانت لديه أصلاً. وتكون المراقبة أشدّ في الأسابيع الأولى، وبخاصّة لدى صغار السنّ.
Never stop abruptlyDiscontinuation symptoms — dizziness, electric-shock sensations, nausea, irritability, vivid dreams, flu-like symptoms. Patients frequently interpret these as proof they were addictive. Explain in advance, and taper.لا يُوقَف فجأةً أبداً — أعراض الانقطاع: دوخة وإحساس بصدمات كهربائية وغثيان وتهيّج وأحلام حيّة وأعراض شبيهة بالإنفلونزا. وكثيراً ما يفسّر المرضى هذه الأعراض على أنها دليل على أن الدواء يسبّب الإدمان. ويُشرح ذلك مسبقاً، ويُخفَّض الدواء تدريجياً.

Serotonin syndrome is the emergency of this drug group — caused by too much serotonergic activity, most often after adding a second serotonergic drug, increasing a dose, or an overdose.

ومتلازمة السيروتونين الحالة الإسعافية لهذه المجموعة — سببها نشاط سيروتوني مفرط وغالباً بعد إضافة دواء سيروتوني ثانٍ أو زيادة جرعة أو جرعة زائدة.

⚡Serotonin syndrome
  • Develops over HOURS
  • HYPERreflexia and clonus
  • Muscles twitchy and overactive
  • Agitation, dilated pupils, diarrhoea
  • Fever, sweating, tachycardia
متلازمة السيروتونين — تتطوّر خلال ساعات: فرط منعكسات ورمع؛ وعضلات منتفضة مفرطة النشاط؛ وهياج واتّساع الحدقتين وإسهال؛ وحمّى وتعرّق وتسرّع القلب.
🧊Neuroleptic malignant syndrome
  • Develops over DAYS
  • Lead-pipe RIGIDITY
  • Muscles stiff, not twitchy
  • Reduced reflexes
  • High fever, altered consciousness, ↑ CK
المتلازمة الخبيثة لمضادّات الذهان — تتطوّر خلال أيام: صلابة «أنبوب الرصاص»؛ وعضلات متيبّسة لا منتفضة؛ ومنعكسات منقوصة؛ وحمّى عالية وتغيّر في الوعي وارتفاع كيناز الكرياتين.

The usable discriminators: hours against days, and hyperreflexia with clonus against lead-pipe rigidity. Both are emergencies, both need the drug stopped and urgent escalation — but the drug you stop is different, so the distinction is not academic.

والفروق العملية المميِّزة: ساعات مقابل أيام، وفرط المنعكسات مع الرمع مقابل صلابة «أنبوب الرصاص». وكلتا الحالتين إسعافية وتستلزم إيقاف الدواء والتصعيد العاجل — لكن الدواء الذي يُوقَف يختلف، فالتمييز بينهما ليس مسألة نظرية.

Benzodiazepines work quickly for anxiety and insomnia — which is precisely the problem: they are effective, they feel good, and tolerance and dependence develop within weeks. They are therefore intended for short-term use, and stopping after prolonged use must be gradual: abrupt withdrawal can cause seizures, and is one of the few withdrawals that is genuinely dangerous.

والبنزوديازيبينات تعمل بسرعة في علاج القلق والأرق — وهذه هي المشكلة تحديداً: فهي فعّالة، وتمنح شعوراً بالارتياح، ويتطوّر التحمّل والاعتماد خلال أسابيع. ولهذا يُقصَد بها الاستخدام قصير الأمد، ويجب أن يكون التوقّف بعد الاستخدام المطوّل تدريجياً: فالانسحاب المفاجئ قد يسبّب اختلاجات، وهو من الانسحابات القليلة الخطرة فعلاً.

🚩
Watch out
تنبيه
Risk rises in the early weeks of antidepressant treatment, because energy and motivation return before the hopelessness lifts. Increase observation when the patient starts to look better.
الخطر يرتفع في الأسابيع الأولى من علاج مضادّ الاكتئاب، فالطاقة والدافعية تعودان قبل انقشاع اليأس. تُزاد الملاحظة حين يبدأ المريض في الظهور بحال أفضل.
🔑
Memory aid
مفتاح للحفظ
Serotonin syndrome develops over hours with hyperreflexia and clonus. Neuroleptic malignant syndrome develops over days with lead-pipe rigidity and reduced reflexes.
متلازمة السيروتونين تتطوّر عبر ساعات بفرط منعكسات ورمع. والمتلازمة الخبيثة لمضادّات الذهان تتطوّر عبر أيام بصلابة «أنبوب الرصاص» ونقص المنعكسات.
🚩
Watch out
تنبيه
Benzodiazepines are never stopped abruptly after prolonged use — withdrawal can cause seizures. They are tapered under supervision.
البنزوديازيبينات لا تُوقَف فجأةً أبداً بعد استخدام مطوّل — فالانسحاب قد يسبّب اختلاجات. وتُخفَّض تحت إشراف.

16.6 · Alcohol and Its Withdrawal١٦٫٦ · الكحول وانسحابه

Alcohol withdrawal follows a timeline, and knowing it tells you what to expect and when.

وانسحاب الكحول يتبع خطاً زمنياً ومعرفته تبيّن ما يُتوقَّع حدوثه ومتى.

1
6–12 hours — early withdrawal
Tremor, anxiety, sweating, nausea, headache, fast pulse, raised blood pressure.
٦ إلى ١٢ ساعة — انسحاب مبكّر: رعاش وقلق وتعرّق وغثيان وصداع ونبض سريع وارتفاع ضغط الدم.
2
12–24 hours — hallucinations
Usually visual, and typically with insight retained — he knows they are not real.
١٢ إلى ٢٤ ساعة — هلوسات: بصرية عادةً، وغالباً مع احتفاظ بالبصيرة — إذ يعرف المريض أنها غير حقيقية.
3
12–48 hours — seizures
Generalised, and a genuine risk of harm.
١٢ إلى ٤٨ ساعة — اختلاجات معمّمة، وفيها خطر حقيقي للأذى.
4
48–72 hours — delirium tremens
The most dangerous complication, and potentially fatal.
٤٨ إلى ٧٢ ساعة — الهذيان الارتعاشي: أخطر المضاعفات، وقد يكون قاتلاً.
👀Withdrawal hallucinations
  • 12–24 hours
  • Usually visual
  • Insight retained — he knows they are not real
  • Orientation intact
  • Frightening, but not delirium
هلوسات الانسحاب — ١٢ إلى ٢٤ ساعة؛ بصرية عادةً؛ مع بصيرة محفوظة — يعرف المريض أنها غير حقيقية؛ والتوجّه سليم؛ مخيفة لكنها ليست هذياناً.
🚨Delirium tremens
  • 48–72 hours
  • Severe confusion and disorientation
  • Vivid hallucinations he believes are real
  • Marked tremor, agitation, autonomic instability
  • Potentially fatal — needs a monitored setting
الهذيان الارتعاشي — ٤٨ إلى ٧٢ ساعة: تشوّش شديد وتوهان؛ وهلوسات حيّة يصدّقها المريض؛ ورعاش واضح وهياج وعدم استقرار في الجهاز العصبي المستقل؛ وقد يكون قاتلاً — ويحتاج إلى بيئة خاضعة للمراقبة.

Management is a benzodiazepine by a symptom-triggered or fixed regimen per your protocol, a quiet well-lit environment, frequent observation, correction of fluids and electrolytes, and attention to safety — he is confused, frightened and at risk of falling.

ويشمل التدبير إعطاء بنزوديازيبين وفق نظام محفَّز بالأعراض أو نظام ثابت بحسب البروتوكول المعتمد، وتوفير بيئة هادئة جيدة الإضاءة، ومراقبة متكررة، وتصحيح السوائل والشوارد، والانتباه للسلامة — فالمريض مشوّش وخائف ومعرّض للسقوط.

Thiamine is the other essential, and the rule about it is one of the most examined points in this chapter.

والثيامين هو العنصر الأساسي الآخر، والقاعدة المتعلّقة به من أكثر النقاط اختباراً في هذا الفصل.

•The thiamine rule◆ قاعدة الثيامين
Why he is deficientChronic alcohol use depletes thiamine through poor intake and impaired absorption.لماذا هو ناقص — يستنفد التعاطي المزمن للكحول الثيامين بسبب سوء الوارد الغذائي وضعف الامتصاص.
GIVE THIAMINE BEFORE GLUCOSEGlucose given to a thiamine-deficient patient consumes the remaining thiamine and can precipitate Wernicke encephalopathy.يُعطى الثيامين قبل الغلوكوز — فالغلوكوز المُعطى لمريض ناقص الثيامين يستهلك ما تبقّى من الثيامين وقد يُحدث اعتلال دماغ فيرنيكه.
So if he needs glucose urgentlyThiamine goes in first or at the same time — never after.فإن احتاج غلوكوزاً عاجلاً — يُعطى الثيامين أولاً أو في الوقت نفسه، ولا يُعطى بعده أبداً.

Wernicke encephalopathy is an acute, treatable emergency caused by thiamine deficiency, and the classic triad is confusion, ataxia and eye signs — nystagmus or paralysis of eye movement. Two things matter: the whole triad is frequently absent, so treat on suspicion rather than waiting for it; and untreated it progresses to Korsakoff syndrome — a permanent, largely irreversible memory disorder with confabulation. The window between a treatable emergency and permanent brain damage is short.

واعتلال دماغ فيرنيكه حالة إسعافية حادّة قابلة للعلاج سببها نقص الثيامين، والثلاثي الكلاسيكي هو التشوّش والرنح والعلامات العينية — رأرأة أو شلل حركة العين. وأمران يهمّان: أن الثلاثي بكامله كثيراً ما يغيب، فيُعالَج المريض عند الاشتباه دون انتظار ظهوره؛ وأنه بلا علاج يتقدّم إلى متلازمة كورساكوف — اضطراب ذاكرة دائم غير عكوس إلى حدّ بعيد مع تلفيق. والنافذة بين حالة إسعافية قابلة للعلاج وتلف دماغي دائم قصيرة.

🔑
Memory aid
مفتاح للحفظ
Alcohol withdrawal timeline: tremor and anxiety at 6–12 hours, hallucinations at 12–24, seizures at 12–48, and delirium tremens at 48–72 hours.
الخطّ الزمني لانسحاب الكحول: رعاش وقلق عند ٦–١٢ ساعة وهلوسات عند ١٢–٢٤ واختلاجات عند ١٢–٤٨ والهذيان الارتعاشي عند ٤٨–٧٢ ساعة.
🚩
Watch out
تنبيه
Delirium tremens is the most dangerous complication of alcohol withdrawal and is potentially fatal. Anticipate it from the timeline rather than reacting to it.
الهذيان الارتعاشي أخطر مضاعفات انسحاب الكحول وقد يكون مميتاً. يُتوقَّع حدوثه استناداً إلى الخطّ الزمني، ولا يُكتفى بردّ الفعل بعد وقوعه.
🚩
Watch out
تنبيه
Thiamine is given before or with any glucose, never after. Giving glucose first consumes the remaining thiamine and precipitates Wernicke encephalopathy.
الثيامين يُعطى قبل أيّ غلوكوز أو معه لا بعده أبداً. فإعطاء الغلوكوز أولاً يستهلك الثيامين المتبقّي ويُحدث اعتلال دماغ فيرنيكه.
⭐
Key point
نقطة أساسية
Wernicke encephalopathy is confusion, ataxia and eye signs, and it is reversible with urgent thiamine. Untreated it becomes Korsakoff syndrome — irreversible memory loss with confabulation.
اعتلال دماغ فيرنيكه تشوّش ورنح وعلامات عينية وهو عكوس بثيامين عاجل. وبلا علاج يصير متلازمة كورساكوف — فقد ذاكرة غير عكوس مع تلفيق.

16.7 · Opioids, Harm Reduction and Relapse١٦٫٧ · الأفيونيات وتقليل الضرر والنكس

Opioid overdose is recognised by a triad, and death is from respiratory depression — so the priorities are airway, breathing and oxygen, then naloxone.

والجرعة الزائدة من الأفيونيات تُعرَف بثلاثي من العلامات، والموت ينتج عن تثبيط التنفّس — فالأولويات مجرى الهواء والتنفّس والأكسجين ثم النالوكسون.

↓ Consciousnessreduced levelانخفاض الوعي — هبوط في مستوى الوعي
↓ Respiratory ratethe cause of deathانخفاض معدّل التنفّس — سبب الوفاة
Pinpoint pupilsthe giveawayحدقتان دبّوسيتان — العلامة الكاشفة

The point about naloxone that is regularly missed: its duration of action is shorter than that of many opioids, so the patient can re-sedate after it wears off. He is observed, not discharged because he woke up.

والنقطة عن النالوكسون التي تُغفَل بانتظام: أن مدّة فعله أقصر من كثير من الأفيونيات فقد يعود المريض إلى حالة التهدئة بعد زوال مفعوله. فهو يُراقَب ولا يُخرَج لمجرد أنه استيقظ.

⚠️Alcohol / benzodiazepine withdrawal
  • Can cause seizures
  • Can cause delirium tremens
  • Potentially FATAL
  • Needs medical management
انسحاب الكحول والبنزوديازيبين — قد يسبّب اختلاجات وهذياناً ارتعاشياً، وقد يكون قاتلاً، ويحتاج إلى تدبير طبي.
😒Opioid withdrawal
  • Deeply unpleasant — aching, sweating, cramps, diarrhoea, agitation
  • But not usually life-threatening in a physically well adult
  • A distinction worth knowing — it is the opposite of what most people assume
  • Still treated, because untreated distress drives him back to using
انسحاب الأفيونيات — شديد الإزعاج: آلام وتعرّق وتشنّجات وإسهال وهياج؛ لكنه غير مهدّد للحياة عادةً لدى البالغ السليم بدنياً. وهذا تمييز يستحقّ المعرفة، فهو عكس ما يفترضه معظم الناس. ومع ذلك يُعالَج، لأن الكرب غير المعالَج يدفع المريض إلى العودة إلى التعاطي.

The single most important fact in opioid harm reduction is about lost tolerance, and it saves lives.

وأهمّ حقيقة في تقليل ضرر الأفيونيات تتعلّق بفقدان التحمّل، وهي تنقذ الأرواح.

1
He stops using for a period
After detoxification, a hospital admission, a period in custody, or a spell of abstinence.
يتوقّف عن الاستخدام مدّةً — بعد إزالة السموم أو التنويم أو فترة احتجاز أو فترة امتناع.
2
Tolerance falls quickly
Much faster than people expect.
يهبط التحمّل بسرعة — أسرع بكثير ممّا يتوقّع الناس.
3
He returns to his USUAL dose
The one that was safe for him before.
يعود لجرعته المعتادة — التي كانت آمنةً له من قبل.
4
And it is now an overdose
The period immediately after a period of abstinence is the highest-risk time for a fatal overdose.
وهي الآن جرعة زائدة — فالفترة التي تلي الامتناع مباشرةً هي أعلى الأوقات خطراً للجرعة الزائدة القاتلة.
5
So say it explicitly, before discharge
To him and to whoever is with him — and provide take-home naloxone where the service does.
لذا يُقال ذلك صراحةً قبل الخروج — للمريض ولمن معه — ويُوفَّر النالوكسون للاستخدام المنزلي حيثما تقدّمه الخدمة.

Harm reduction is the principle that reducing the damage caused by substance use is a legitimate clinical goal even where stopping is not achieved. It is not approval of use and it is not giving up on recovery — it is keeping a person alive and well enough to recover later. Needle and syringe provision, testing and treatment for blood-borne viruses, wound care, vaccination, and overdose education all belong to it.

وتقليل الضرر مبدأ أن تقليل الأذى الناجم عن تعاطي المواد هدف سريري مشروع حتى عندما لا يتحقّق التوقّف. وهو ليس إقراراً بالاستخدام ولا تخلّياً عن التعافي — بل إبقاء شخص حيّاً وبخير كفايةً ليتعافى لاحقاً. ويندرج فيه توفير الإبر والمحاقن، وفحص الفيروسات المنقولة بالدم وعلاجها، ورعاية الجروح، والتطعيم، والتثقيف بشأن الجرعة الزائدة.

•Relapse — and why how you respond to it matters◆ النكس — ولماذا تهمّ طريقة الاستجابة له
It is part of the expected courseSubstance use disorders are relapsing conditions. Relapse is not evidence that the person or the treatment has failed.جزء من المسار المتوقّع — فاضطرابات التعاطي حالات ناكسة. والنكس ليس دليلاً على أن الشخص أو العلاج قد أخفق.
Treating it as failureMakes it less likely he returns — and returning is what determines the outcome.معاملته كإخفاق — تجعل عودة المريض إلى العلاج أقلّ ترجيحاً، والعودة هي ما يحدّد النتيجة.
And the danger after itA relapse following abstinence carries the lost-tolerance overdose risk above — so the response is clinical, not moral.والخطر بعده — النكس بعد فترة امتناع يحمل خطر الجرعة الزائدة الناتج عن فقدان التحمّل المذكور أعلاه، لذا تكون الاستجابة سريرية لا أخلاقية.
So respond by re-engagingAsk what happened, what was different, and what would help — and make the door back an easy one.فتكون الاستجابة بإعادة الإشراك — يُسأل عمّا حدث، وما الذي اختلف، وما الذي قد يفيد، ويُجعل باب العودة سهلاً.
🚩
Watch out
تنبيه
After a period of abstinence, tolerance falls quickly. Returning to the previous dose can be fatal, which makes the period just after detoxification, discharge or custody the highest-risk time for overdose.
بعد مدّة من الامتناع يهبط التحمّل بسرعة. والعودة للجرعة السابقة قد تكون مميتة، ما يجعل الفترة بُعيد إزالة السموم أو الخروج أو الاحتجاز أعلى الأوقات خطراً للجرعة الزائدة.
🔑
Memory aid
مفتاح للحفظ
Opioid overdose: reduced consciousness, reduced respiratory rate and pinpoint pupils. Naloxone is shorter-acting than most opioids, so observe for recurrence.
الجرعة الأفيونية الزائدة: نقص وعي ونقص معدّل تنفّس وحدقتان دبّوسيتان. والنالوكسون أقصر مفعولاً من معظم الأفيونيات فيُراقَب المريض تحسّباً لعودة الأعراض.
⭐
Key point
نقطة أساسية
Unpleasant but not usually fatal in a well adult — unlike alcohol and benzodiazepine withdrawal, which can kill. It is dangerous in pregnancy.
مزعج لكنه ليس مميتاً عادةً لدى بالغ سليم — بخلاف انسحاب الكحول والبنزوديازيبين اللذين قد يقتلان. وهو خطر في الحمل.
⭐
Key point
نقطة أساسية
Relapse is part of the expected course of a relapsing condition, not evidence of failure. Treating it as failure drives people out of services and makes the next relapse more dangerous.
النكس جزء من المسار المتوقّع لحالة ناكسة لا دليل إخفاق. ومعاملته كإخفاق تُخرج الناس من الخدمات وتجعل النكس التالي أخطر.

16.8 · Substance Use in the Saudi Setting١٦٫٨ · تعاطي المواد في السياق السعودي

A nurse trained on Western material is prepared for the wrong problem here, and the difference matters clinically. In much of the world alcohol dominates substance-related presentations; in Saudi Arabia the picture is different, and amphetamine-type stimulants — particularly captagon — feature far more prominently.

والممرضة المدرَّبة على مناهج غربية مهيّأة للمشكلة الخاطئة هنا والفرق يهمّ سريرياً. ففي كثير من العالم يهيمن الكحول على الحالات المرتبطة بالمواد؛ وفي السعودية الصورة مختلفة والمنبّهات الأمفيتامينية — خاصّةً الكبتاغون — أبرز بكثير.

🌍What you were taught to expect
  • Alcohol withdrawal and delirium tremens
  • Thiamine and Wernicke
  • A benzodiazepine regimen
  • Still relevant — but not the first thing you will meet
ما جرى التدريب على توقّعه — انسحاب الكحول والهذيان الارتعاشي؛ والثيامين واعتلال دماغ فيرنيكه؛ ونظام بنزوديازيبين: ما زال ذا صلة لكنه ليس أوّل ما يُصادَف.
⚡What to expect first here
  • Acute stimulant intoxication
  • Agitation, aggression, tachycardia, hypertension
  • Hyperthermia, dilated pupils, psychosis
  • Risk of arrhythmia, seizure, stroke and rhabdomyolysis
ما يُتوقَّع أولاً هنا — تسمّم حادّ بالمنبّهات: هياج وعدوانية وتسرّع قلب وارتفاع ضغط الدم؛ وفرط حرارة واتّساع الحدقتين وذهان؛ وخطر اضطراب النظم والاختلاج والسكتة الدماغية وانحلال الربيدات.

The management is supportive and specific: a calm low-stimulus environment, benzodiazepines for agitation rather than antipsychotics as first line, active cooling for hyperthermia, fluids, and cardiac and temperature monitoring. And note that stimulant-induced psychosis can be indistinguishable from a primary psychotic illness on presentation — so a first-episode psychosis is asked about substances, without accusation.

والتدبير داعم ومحدّد: بيئة هادئة قليلة التنبيه وبنزوديازيبينات للهياج لا مضادات الذهان خطّاً أول وتبريد فعّال لارتفاع الحرارة وسوائل ومراقبة قلبية وحرارية. ويُلاحَظ أن الذهان الناجم عن المنبّهات قد يتعذّر تمييزه عن مرض ذهاني أوّلي عند التظاهر — لذا يُسأل المريض عن المواد في أول نوبة ذهانية بلا اتّهام.

The legal and religious context shapes everything about disclosure, and pretending otherwise helps nobody. Substances are prohibited both by faith and by law, penalties are severe, and the shame attached is profound.

والسياق القانوني والديني يحدّد كلّ ما يتعلّق بالإفصاح، والتظاهر بغير ذلك لا يفيد أحداً. فالمواد محظورة بالدين والقانون معاً والعقوبات شديدة والعار المرتبط بها عميق.

•What that means for a nurse◆ ما يعنيه ذلك في الممارسة التمريضية
He will not volunteer itAnd may deny it directly when asked. Assume under-disclosure rather than absence.لن يتطوّع بذكرها — وقد ينكرها مباشرةً عند السؤال: يُفترَض نقص الإفصاح لا الغياب.
Family may be presentWhich makes honest disclosure impossible — so ask privately, as a routine part of the assessment rather than as a suspicion.قد تكون الأسرة حاضرةً — وهذا يجعل الإفصاح الصادق مستحيلاً، لذا يُسأل المريض على انفراد، كجزء روتيني من التقييم لا كشبهة.
Ask everyone, the same wayA question asked of every patient is not an accusation of this one.يُسأل الجميع بالطريقة نفسها — فالسؤال الذي يُطرَح على كلّ مريض ليس اتّهاماً لهذا المريض.
Treat what is in front of youThe clinical presentation is managed regardless of what he has admitted to — tachycardia and hyperthermia are treated as what they are.يُعالَج ما هو ماثل — فالتظاهر السريري يُدبَّر بغضّ النظر عمّا اعترف به المريض؛ إذ يُعالَج تسرّع القلب وفرط الحرارة على حقيقتهما.
Know your own obligationsConfidentiality, reporting requirements and referral routes differ by setting — know yours before you are in the room, not while you are in it.معرفة الالتزامات المهنية — تختلف السرّية ومتطلبات الإبلاغ وطرق الإحالة بحسب بيئة العمل، ويجب معرفتها قبل دخول الغرفة لا أثناء الوجود فيها.
•Three further points that complete the picture◆ ثلاث نقاط إضافية تُكمل الصورة
Treatment services existThe Kingdom operates dedicated addiction hospitals and rehabilitation services with established referral routes — so a nurse who identifies a problem has somewhere to refer to, and saying so plainly is often the most useful thing in the conversation.خدمات العلاج موجودة — تدير المملكة مستشفيات مخصّصة للإدمان وخدمات تأهيل بطرق إحالة راسخة، فتتوافر للطاقم التمريضي الذي يكتشف مشكلة جهةٌ يُحال إليها المريض، وقول ذلك بوضوح هو غالباً أنفع ما في المحادثة.
KhatChewed for its stimulant effect and used in parts of the region, particularly the south-west and among some expatriate communities. It causes tachycardia, hypertension, insomnia, anorexia and, with heavy use, psychosis — and users frequently do not regard it as a drug, so ask about it by name.القات — يُمضَغ لأثره المنبّه ويُستخدَم في أجزاء من المنطقة، وبخاصّة الجنوب الغربي وبين بعض الجاليات الوافدة. يسبّب تسرّع القلب وارتفاع ضغط الدم والأرق وفقدان الشهية، والذهان مع الاستخدام الكثيف — وكثيراً ما لا يعدّه المتعاطون مادة مخدّرة، لذا يُسأل عنه بالاسم.
Tobacco is the biggest oneIncluding shisha — the substance use with the largest population health impact here. It is legal, it is normalised, and families frequently do not classify shisha as smoking.التبغ هو الأكبر — بما فيه الشيشة: فهو تعاطي المواد الأكبر أثراً على صحّة السكان هنا. وهو قانوني ومُطبَّع اجتماعياً، وكثيراً ما لا تصنّف الأسر الشيشة ضمن التدخين.
And brief advice worksBrief advice from a nurse measurably increases quit rates. It is the substance conversation you will have most often, and the one most often skipped.والنصيحة الموجزة تنجح — فالنصيحة الموجزة من الطاقم التمريضي ترفع معدّلات الإقلاع بشكل قابل للقياس. وهي المحادثة المتعلّقة بالمواد التي تتكرّر أكثر من غيرها، والتي يُغفَل عنها أكثر من غيرها.
⭐
Key point
نقطة أساسية
Amphetamine, most often as Captagon, is among the leading substances here — about forty per cent of single-drug misuse in one large Al-Qassim rehabilitation-centre series, with the share varying by setting — and alcohol is reported far less often. A nurse trained on Western material expects the wrong problem.
الأمفيتامين وغالباً كالكبتاغون من المواد الأبرز هنا — نحو أربعين بالمئة من إساءة استخدام مادة واحدة في سلسلة كبيرة لمركز تأهيل في القصيم وتختلف النسبة باختلاف البيئة — والكحول يُبلَّغ عنه أقلّ بكثير. والممرضة المدرَّبة على مناهج غربية تتوقّع المشكلة الخطأ.
🚩
Watch out
تنبيه
Stimulant intoxication kills through hyperthermia, arrhythmia, hypertensive crisis, seizures, stroke and myocardial infarction — including in young people with normal arteries.
التسمّم بالمنبّهات يقتل عبر فرط الحرارة واضطراب النظم والأزمة الضغطية والاختلاجات والسكتة الدماغية واحتشاء عضلة القلب — بما في ذلك لدى شباب بشرايين طبيعية.
⭐
Key point
نقطة أساسية
Stimulant withdrawal is not usually physically dangerous but causes profound low mood and a real suicide risk. The crash after intoxication is when the mental health assessment matters most.
انسحاب المنبّهات ليس خطراً بدنياً عادةً لكنه يسبّب انخفاضاً عميقاً في المزاج وخطر انتحار حقيقياً. والانهيار الذي يعقب التسمّم هو الوقت الذي يكون فيه التقييم النفسي أشدّ أهمية.
🚩
Watch out
تنبيه
Ask about substance use routinely of everyone rather than of those you suspect, so that being asked is not itself an accusation — and never promise a confidentiality you cannot deliver.
يُسأل عن تعاطي المواد روتينياً من الجميع، لا ممّن يُشتبَه بهم فقط، كي لا يكون السؤال نفسه اتّهاماً — ولا يُوعَد أبداً بسرّية لا يمكن تحقيقها.

Test yourselfالاختبار الذاتي

Loading… جارٍ التحميل…

Medical disclaimer. The content of this platform is for education and exam preparation only. It is not medical advice and does not replace consultation with a qualified physician or other licensed healthcare professional, or current clinical guidelines. Do not use it to diagnose or treat any person. إخلاء المسؤولية الطبية: محتوى هذه المنصة مخصص للتعليم والتحضير للاختبار فقط، وليس نصيحة طبية، ولا يغني عن استشارة الطبيب المختص أو الممارس الصحي المرخّص، ولا عن الإرشادات السريرية الحالية. ولا يجوز استخدامه لتشخيص أي شخص أو علاجه.