
Burns & Wound Care
In this chapterفي هذا الفصل
Key terms (12)المصطلحات الأساسية
Chapter outline (20 sections)مخطط الفصل
- Learning Objectivesأهداف التعلّم
- 13.1 · Assessing a Burn١٣٫١ · تقييم الحرق
- 13.2 · The First Minutes١٣٫٢ · الدقائق الأولى
- 13.3 · The Airway and Inhalation Injury١٣٫٣ · المجرى الهوائي وإصابة الاستنشاق
- 13.4 · Fluid Resuscitation١٣٫٤ · إنعاش السوائل
- 13.5 · Why the Fluid Matters: Burn Shock and the Zone of Stasis١٣٫٥ · لماذا تهمّ السوائل: صدمة الحرق ومنطقة الركود
- 13.6 · The Two Phases and Their Electrolytes١٣٫٦ · المرحلتان وشوارِدهما
- 13.7 · Complications and Wound Care١٣٫٧ · المضاعفات والعناية بالجرح
- 13.8 · Choosing Dressings and Recognising Infection١٣٫٨ · اختيار الضمادات وتمييز العدوى
- 13.9 · Toxic Shock and Assessing the Depth of a Wound١٣٫٩ · الصدمة السمّية وتقييم عمق الجرح
- 13.10 · Special Situations and Recovery١٣٫١٠ · مواقف خاصّة والتعافي
- 13.11 · The History, the Older Patient and Oxygen at Home١٣٫١١ · القصّة والمريض المسنّ والأكسجين في المنزل
- 13.12 · Two Burn Situations That Kill Disproportionately١٣٫١٢ · موقفان في الحروق يقتلان بغير تناسب
- 13.13 · Cold Injury and Life After the Burn١٣٫١٣ · إصابة البرد والحياة بعد الحرق
- 13.14 · When the Burn Is Not Survivable١٣٫١٤ · حين لا يكون الحرق قابلاً للنجاة
- 13.15 · Wounds and Skin Integrity١٣٫١٥ · الجروح وسلامة الجلد
- 13.16 · When a Wound or the Skin Becomes an Emergency١٣٫١٦ · حين يصير الجرح أو الجلد طارئاً
- 13.17 · Leg Ulcers and the Diabetic Foot١٣٫١٧ · قرح الساق والقدم السكّرية
- 13.18 · Device Injury, Skin Conditions and Scars١٣٫١٨ · أذيّة الأجهزة والحالات الجلدية والندبات
- 13.19 · Burns in the Saudi Setting١٣٫١٩ · الحروق في السياق السعودي
Start learningبدء التعلّم Learning objectivesأهداف التعلّم Test yourselfالاختبار الذاتي
Learning Objectivesأهداف التعلّم
13.1 · Assessing a Burn١٣٫١ · تقييم الحرق
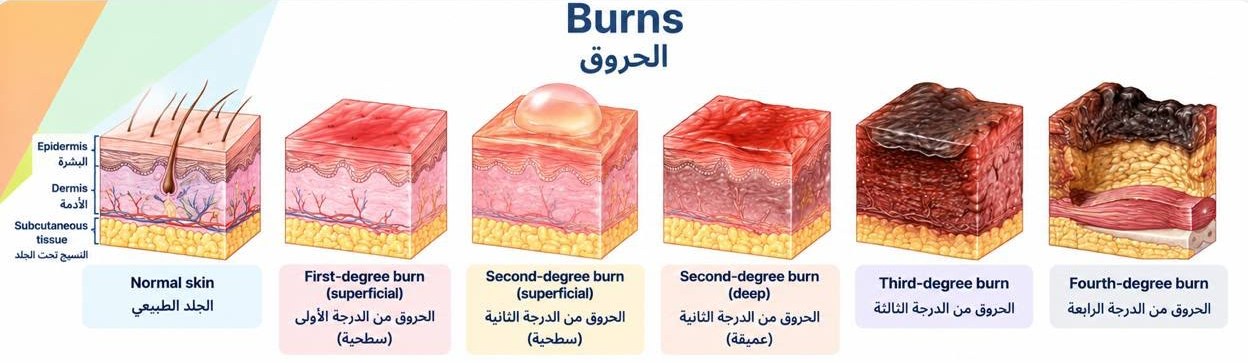
Burn depth determines healing, treatment and scarring, and each depth has a recognisable appearance.
عمق الحرق يحدّد الالتئام والعلاج والتندّب ولكلّ عمق مظهر مميّز.
- More pain = worse burn
- So a painless area is reassuring
- And a screaming patient is the priority
- Both assumptions are backwards
- The deepest burn is the one that does NOT hurt
- The nerve endings are destroyed
- Painless, leathery, non-blanching = full thickness
- More serious than the blistered area screaming beside it
Total body surface area is estimated because it determines fluid resuscitation and referral.
مساحة سطح الجسم الكلّية تُقدَّر لأنها تحدّد الإنعاش السائلي والإحالة.
13.2 · The First Minutes١٣٫٢ · الدقائق الأولى
The tension in burn care is that you must cool the burn but keep the patient warm, and these pull in opposite directions. A burned patient loses heat rapidly through damaged skin, and hypothermia worsens the outcome — it deepens the burn, impairs clotting and worsens shock. So cool the burn, not the person: in a large burn, cool in stages or for a shorter period, and monitor the temperature.
يكمن التوتّر في رعاية الحروق في أنه يجب تبريد الحرق مع إبقاء المريض دافئاً وهما يتجاذبان اتّجاهين متعاكسين. فالمريض المحروق يفقد الحرارة بسرعة عبر جلد متضرّر وانخفاض الحرارة يسوّئ النتيجة — فيعمّق الحرق ويُضعف التخثّر ويسوّئ الصدمة. فيُبرَّد الحرق لا الشخص؛ وفي الحرق الواسع يُبرَّد على مراحل أو لمدة أقصر مع مراقبة درجة الحرارة.
13.3 · The Airway and Inhalation Injury١٣٫٣ · المجرى الهوائي وإصابة الاستنشاق
The airway is always the first priority in a burn, ahead of the burn itself — because airway swelling develops progressively over hours, and a patient who is talking comfortably now can be in trouble later.
المجرى الهوائي هو دائماً الأولوية الأولى في الحرق قبل الحرق نفسه — فتورّم المجرى يتطوّر تدريجياً عبر ساعات والمريض الذي يتحدّث بارتياح الآن قد تتدهور حالته لاحقاً.
The management principle is early intubation by an experienced clinician, before the airway closes — rather than waiting for deterioration. It is far easier to intubate an airway that is still open, and an attempt made once the swelling is established may fail entirely. So a nurse’s contribution is escalating on the signs above rather than on the observations, which will look normal.
مبدأ التدبير هو التنبيب المبكّر من ممارس خبير قبل انغلاق المجرى — لا انتظار التدهور. فتنبيب مجرى ما زال مفتوحاً أسهل بكثير ومحاولة تُجرى بعد ترسّخ التورّم قد تفشل تماماً. فمساهمة الكادر التمريضي هي التصعيد على العلامات أعلاه لا على القياسات التي ستبدو طبيعية.
Carbon monoxide poisoning must be assumed in anyone burned in an enclosed space, and it contains a trap the nurse must know.
يجب افتراض تسمّم أول أكسيد الكربون لدى كلّ من احترق في مكان مغلق، وهو يحوي فخّاً يجب أن يعرفه الكادر التمريضي.
- Pulse oximetry is falsely NORMAL or high
- The oximeter cannot distinguish carboxyhaemoglobin from oxyhaemoglobin
- So the saturation reads 99% in a dying patient
- A normal saturation does not exclude it
- Suspect it on the history, not the number
- Headache, nausea, confusion, drowsiness — non-specific
- High-flow oxygen through a non-rebreathing mask
- Measure carboxyhaemoglobin on a blood gas
The classic cherry-red skin is a late and unreliable sign — do not wait for it.
الجلد الكرزي الأحمر الكلاسيكي علامة متأخّرة وغير موثوقة — ولا يُنتظَر ظهورها.
13.4 · Fluid Resuscitation١٣٫٤ · إنعاش السوائل
A major burn causes a massive shift of fluid out of the circulation into the tissues, producing hypovolaemia and shock over the first hours even though no blood has been lost.
الحرق الكبير يسبّب انزياحاً هائلاً للسائل من الدوران إلى الأنسجة مؤدّياً إلى نقص حجم الدم وصدمة خلال الساعات الأولى رغم عدم فقدان أي دم.
- Hypotension, poor perfusion
- Falling urine output
- Deepens the burn — the zone of stasis is lost
- Renal failure
- A genuine and under-appreciated risk
- The tendency to exceed the calculated volume is well described
- Worse oedema, compartment syndrome
- Pulmonary oedema, prolonged ventilation
- Abdominal compartment syndrome
So the volume is titrated in both directions: the calculated figure is a guide, and the urine output tells you whether to increase or reduce it. Giving more because the number said so is not resuscitation — it is arithmetic.
فالحجم يُعاير في الاتّجاهين: فالرقم المحسوب دليل وإدرار البول يبيّن هل ينبغي الزيادة أم التقليل. وإعطاء المزيد لأن الرقم قال ذلك ليس إنعاشاً — بل حساباً.
13.5 · Why the Fluid Matters: Burn Shock and the Zone of Stasis١٣٫٥ · لماذا تهمّ السوائل: صدمة الحرق ومنطقة الركود
The formula makes sense only once the underlying physiology does.
الصيغة لا تصير منطقيةً إلا بعد فهم الفيزيولوجيا الكامنة.
The same physiology explains something that changes how the wound is cared for. A burn has three zones.
الفيزيولوجيا نفسها تفسّر شيئاً يغيّر كيفية العناية بالجرح. فللحرق ثلاث مناطق.
What pushes the zone of stasis the wrong way is a short and entirely nursing-controllable list.
ما يدفع منطقة الركود في الاتّجاه الخاطئ قائمة قصيرة يتحكّم بها التمريض تماماً.
Every one of those is something a nurse manages. So ‘the burn got deeper’ is frequently not the burn progressing on its own — it is the zone of stasis being lost to cold, pressure or under-resuscitation.
كلّ واحد منها شيء يتولّاه التمريض. فـ«تعمّق الحرق» كثيراً ما لا يكون تقدّماً ذاتياً للحرق — بل فقدان منطقة الركود للبرد أو الضغط أو نقص الإنعاش.
13.6 · The Two Phases and Their Electrolytes١٣٫٦ · المرحلتان وشوارِدهما
A major burn passes through two phases with opposite fluid and electrolyte pictures, and knowing which phase he is in explains almost every abnormal result.
الحرق الكبير يمرّ بمرحلتين بصورتين سائلية وشاردية متعاكستين ومعرفة أيّ مرحلة هو فيها تفسّر كلّ نتيجة شاذّة تقريباً.
- Fluid leaks OUT of the circulation into the tissues
- HYPERkalaemia — burned cells lyse and release intracellular potassium
- HYPOnatraemia — sodium follows the fluid into the tissues
- Haemoconcentration — a raised haematocrit because plasma is lost
- Metabolic acidosis
- The capillaries seal; fluid returns to the circulation and is excreted
- HYPOkalaemia — potassium is lost in the urine
- Sodium is also lost in the diuresis
- Diuresis — a large urine output that is expected, not reassuring
- Risk of fluid overload as the fluid returns
So the potassium reverses between the two phases, and it is the examinable point: high early because cells are lysing, low later because it is being urinated out. A potassium result is interpreted by asking which phase he is in before anything else.
فالبوتاسيوم ينعكس بين المرحلتين وهو النقطة القابلة للاختبار: مرتفع مبكّراً لانحلال الخلايا ومنخفض لاحقاً لطرحه بالبول. ونتيجة البوتاسيوم تُفسَّر بسؤال أيّ مرحلة هو فيها قبل أيّ شيء.
13.7 · Complications and Wound Care١٣٫٧ · المضاعفات والعناية بالجرح
A circumferential burn — one that encircles a limb, a digit, the neck or the chest — becomes dangerous as oedema develops beneath rigid, inelastic burnt skin called eschar, which cannot expand.
الحرق الدائري (المحيطي) — الذي يطوّق طرفاً أو إصبعاً أو العنق أو الصدر — يصير خطراً مع تطوّر الوذمة تحت جلد محروق صلب غير مرن يُسمّى الخشارة لا يستطيع التمدّد.
- Pressure rises beneath the eschar
- Compartment syndrome — perfusion is cut off
- Watch: pain, pallor, paraesthesia, pulselessness, cold
- Check pulses and capillary refill hourly, and elevate
- Treatment: escharotomy
- The chest wall cannot expand
- So ventilation is mechanically restricted
- Rising airway pressures, falling tidal volume
- Not an airway problem — a chest wall problem
- Treatment: escharotomy, urgently
Infection is the leading cause of death once the patient has survived the resuscitation, because the burn destroys the body’s principal barrier and the wound is an ideal culture medium.
العدوى هي السبب الرئيس للوفاة بعد نجاة المريض من الإنعاش، فالحرق يدمّر الحاجز الرئيس للجسم والجرح وسط زرع مثالي.
The hypermetabolic response to a major burn is extreme and prolonged: the metabolic rate can rise enormously and stay elevated for months, with massive protein breakdown, muscle wasting and impaired healing. So nutrition is treatment, not supportive care — high-calorie, high-protein feeding started early, enterally wherever possible, with the intake actually recorded rather than assumed.
استجابة فرط الاستقلاب لحرق كبير شديدة ومطوّلة: فمعدّل الاستقلاب قد يرتفع هائلاً ويبقى مرتفعاً أشهراً مع تحطيم بروتين هائل وضمور عضلي وضعف التئام. فالتغذية علاج لا رعاية داعمة — عالية السعرات والبروتين تبدأ مبكّراً ومعوياً حيثما أمكن مع تسجيل الوارد فعلياً لا افتراضه.
Pain after a burn has three distinct components, and each needs its own plan — which is why a single regular analgesic fails.
للألم بعد الحرق ثلاثة مكوّنات متمايزة ولكلّ منها خطّته — ولهذا يخفق مسكّن منتظم واحد.
Wound care: clean the burn, debride loose devitalised tissue, and dress it according to depth and local protocol. Blisters are managed by local policy — small intact blisters are commonly left, because the blister is a sterile biological dressing.
رعاية الجرح: يُنظَّف الحرق ويُزال النسيج الميت السائب ويُضمَّد بحسب العمق والبروتوكول المحلّي. ويخضع تدبير الفقاعات للسياسة المحلّية — الصغيرة السليمة تُترَك عادةً فالفقاعة ضماد بيولوجي معقّم.
13.8 · Choosing Dressings and Recognising Infection١٣٫٨ · اختيار الضمادات وتمييز العدوى
Dressings are chosen to match the wound rather than by habit, and the main variable is exudate. The principle: keep a dry wound moist and absorb from a wet one — a wound that is too dry will not heal, and one that is too wet macerates the surrounding skin.
تُختار الضمادات لتناسب الجرح لا بالعادة، والمتغيّر الرئيس هو الإفراز. والمبدأ: يُبقى الجرح الجافّ رطباً ويُمتصّ الإفراز من الجرح الرطب — فالجافّ جداً لن يلتئم والرطب جداً يُنقّع الجلد المحيط.
Wound swabbing is done far more often than it is useful, and understanding why prevents a common harm.
أخذ مسحات من الجروح يُجرى أكثر بكثير ممّا هو نافع وفهم السبب يمنع أذىً شائعاً.
- Every chronic wound is colonised with bacteria
- That is normal and is not infection
- A swab will therefore always grow something
- Treating a swab result rather than a patient means unnecessary antibiotics
- Increasing pain, spreading redness, heat, swelling
- Purulent discharge, offensive odour
- A wound that stops healing or breaks down
- Systemic signs — fever, malaise
- Swab only when you already suspect infection clinically
Surgical site infection follows the same logic and typically appears in the days after operation: increasing rather than settling pain, spreading redness, heat, swelling, discharge, and fever. The discriminator is direction of travel — a wound that hurts less each day is healing; one that hurts more is not.
عدوى موضع الجراحة تتبع المنطق نفسه وتظهر عادةً في الأيام التالية للعملية: ألم يتزايد بدلاً من أن يهدأ واحمرار منتشر وحرارة وتورّم وإفراز وحمّى. والمميّز اتّجاه التطوّر — فالجرح الذي يؤلم أقلّ كلّ يوم يلتئم والذي يؤلم أكثر لا.
Two forms of skin damage are routinely mistaken for pressure injury, and the distinction changes the intervention.
شكلان من تلف الجلد يُخلَط بينهما وبين إصابة الضغط بصورة روتينية، والتمييز يغيّر التدخّل.
- From prolonged exposure to urine, faeces, sweat or exudate
- Diffuse, in skin folds and the perineum
- Edges are irregular and indistinct
- Not over a bony prominence
- Fix the moisture — barrier, cleansing, continence management
- From sustained pressure or shear
- Over a bony prominence — sacrum, heel, trochanter
- Edges more defined
- Staged as above
- Fix the pressure — surface, repositioning, offloading
The third is skin tear — a traumatic separation of skin layers, common in older or steroid-thinned skin. Preserve the flap: do not trim it, roll it gently back into place, dress with a non-adherent dressing, and mark the direction of removal on it so the next person does not lift the flap off.
الثالث هو تمزّق الجلد — انفصال رضّي لطبقات الجلد شائع في جلد كبار السن أو الجلد المرقَّق بالستيرويدات. تُحفَظ السديلة: فلا تُقصّ، وتُعاد برفق إلى مكانها، وتُضمَّد بضماد غير لاصق، ويُعلَّم عليه اتّجاه الإزالة كي لا يرفع الشخص التالي السديلة.
13.9 · Toxic Shock and Assessing the Depth of a Wound١٣٫٩ · الصدمة السمّية وتقييم عمق الجرح
Toxic shock syndrome is the burn complication that kills children with trivial-looking injuries, and it is missed for exactly that reason. It is caused by a toxin produced by bacteria colonising the burn — so the size of the burn does not predict it.
متلازمة الصدمة السمّية هي مضاعفة الحروق التي تقتل أطفالاً بإصابات تبدو بسيطة وتُغفَل لذلك السبب بالضبط. وسببها ذيفان تنتجه جراثيم تستعمر الحرق — فحجم الحرق لا يتنبّأ بها.
The reason this matters so much: a small scald in a toddler, dressed and sent home, is exactly the presentation. So a child who has had any burn and becomes unwell with fever, a rash and vomiting is escalated urgently — and the parents are told this before discharge, in those words.
سبب أهمّيتها الشديدة: أن حرقاً صغيراً بسائل ساخن لدى طفل دارج ضُمّد وأُرسل إلى المنزل هو التظاهر السريري بعينه. فالطفل الذي أصيب بأيّ حرق وصار متوعّكاً بحمّى وطفح وتقيّؤ يُصعَّد عاجلاً — والوالدان يُخبَران بهذا قبل الخروج بتلك الكلمات.
Assessing any wound properly includes measuring what cannot be seen from above.
تقييم أيّ جرح كما ينبغي يشمل قياس ما لا يُرى من فوق.
- Destruction of tissue beneath intact wound edges
- The wound extends further under the skin than the opening suggests
- Assessed by gently probing around the edge
- Recorded by clock position and depth
- A narrow channel extending from the wound
- Can be deep and go in an unexpected direction
- Also probed and measured
- Both change the dressing — the cavity must be filled, loosely, and the packing counted
Record a wound the same way every time so it can be compared: location, size in three dimensions, the wound bed by colour, exudate amount and type, the edges, the surrounding skin, odour, pain, and any undermining or tunnelling by clock position. A wound described differently by each nurse cannot be shown to be improving or deteriorating.
يُسجَّل الجرح بالطريقة نفسها كلّ مرّة كي يمكن مقارنته: الموضع والحجم بثلاثة أبعاد وقاعدة الجرح باللون وكمّية الإفراز ونوعه والحواف والجلد المحيط والرائحة والألم وأيّ تقويض أو تنفّق بموضع الساعة. فالجرح الذي يصفه كلّ فرد من الكادر التمريضي بطريقة مختلفة لا يمكن إثبات تحسّنه أو تدهوره.
13.10 · Special Situations and Recovery١٣٫١٠ · مواقف خاصّة والتعافي
- The injury continues until the chemical is removed
- Protect yourself — gloves and apron
- Brush dry powder off FIRST — water activates some powders
- Then irrigate copiously and for a prolonged period
- Alkalis penetrate deeper than acids and are more serious
- Do not attempt to neutralise — the reaction generates heat
- The visible burn tells you almost nothing
- Current travels along the path of least resistance
- Small entry and exit wounds can overlie massive deep tissue destruction
- Cardiac monitoring — arrhythmia is the immediate risk
- Rhabdomyolysis — watch the urine for myoglobin and the CK
- Fluid requirement is higher than the surface area suggests
Rehabilitation begins on the first day, not when the wounds have healed — because burn scar tissue contracts relentlessly as it matures, and a contracture that forms is far harder to correct than to prevent.
التأهيل يبدأ في اليوم الأول لا حين تلتئم الجروح — فنسيج ندبة الحرق ينكمش بلا هوادة مع نضجه والتقفّع المتشكّل أصعب تصحيحاً بكثير من منعه.
13.11 · The History, the Older Patient and Oxygen at Home١٣٫١١ · القصّة والمريض المسنّ والأكسجين في المنزل
Alongside the burn patterns already described, three features of the history itself raise concern about a burn that was not accidental — and they apply to adults at risk as much as to children.
إلى جانب أنماط الحروق الموصوفة ثمّة ثلاث سمات في القصّة نفسها تثير القلق من حرق غير عرَضي — وتنطبق على البالغين المعرّضين للخطر بقدر الأطفال.
Burns in the older person carry a worse outcome than the same burn in a younger one, and for reasons that change the nursing.
الحروق في المسنّ تحمل نتيجةً أسوأ من الحرق نفسه لدى شخص أصغر سناً ولأسباب تغيّر التمريض.
One further question belongs with every burn in an older person and is easily skipped in the rush of treating the wound: why did this happen? A burn may be the visible symptom of something else — a fall, a faint, a seizure, cognitive impairment, poor vision, alcohol, sedating medication, neglect, or an inability to manage safely at home. Treating the burn and returning him to the situation that caused it means he comes back.
ثمّة سؤال آخر يرتبط بكلّ حرق لدى مسنّ ويسهل تخطّيه في زحمة علاج الجرح: لماذا حدث هذا؟ فالحرق قد يكون عرَضاً مرئياً لشيء آخر — سقوط أو إغماء أو اختلاج أو ضعف إدراكي أو سوء بصر أو كحول أو دواء مهدّئ أو إهمال أو عجز عن التدبّر بأمان في المنزل. وعلاج الحرق وإعادته للوضع الذي سبّبه يعني أنه سيعود.
Finally, a preventable catastrophe that nurses are well placed to avert: fire risk with home oxygen. Oxygen does not itself burn, but it makes everything else ignite more easily and burn far more fiercely.
وأخيراً كارثة قابلة للمنع يكون الكادر التمريضي في موضع جيّد لتفاديها: خطر الحريق مع الأكسجين المنزلي. فالأكسجين لا يحترق بذاته لكنه يجعل كلّ شيء آخر يشتعل أسهل ويحترق أشدّ بكثير.
13.12 · Two Burn Situations That Kill Disproportionately١٣٫١٢ · موقفان في الحروق يقتلان بغير تناسب
Hydrofluoric acid deserves its own mention because it behaves unlike any other chemical burn, and because a relatively small surface burn can kill. It is used industrially in rust removers, glass etching and cleaning products.
حمض الهيدروفلوريك يستحقّ ذكراً خاصّاً لأنه يتصرّف بخلاف أيّ حرق كيميائي آخر ولأن حرقاً سطحياً صغيراً نسبياً قد يقتل. ويُستخدَم صناعياً في مزيلات الصدأ ونقش الزجاج ومنتجات التنظيف.
Management therefore differs in one crucial respect: irrigation alone is not enough. Irrigate copiously as for any chemical injury, then apply calcium gluconate gel to bind the fluoride — and monitor calcium, magnesium and the ECG, because the arrhythmia is what kills. Escalate early regardless of how the skin looks.
يختلف التدبير في جانب حاسم: الغسل وحده لا يكفي. يُغسَل بغزارة كأيّ إصابة كيميائية ثم يُوضَع هلام غلوكونات الكالسيوم لربط الفلوريد — ويُراقَب الكالسيوم والمغنيسيوم وتخطيط القلب فاضطراب النظم هو ما يقتل. ويُصعَّد الأمر مبكّراً بغضّ النظر عن مظهر الجلد.
Abdominal compartment syndrome is a complication of major burns that follows directly from the treatment: the large volumes of fluid required for resuscitation cause tissue oedema throughout the body, including within the abdomen, and the pressure inside the abdominal cavity rises.
متلازمة الحيّز البطني مضاعفة للحروق الكبيرة تنتج مباشرةً عن العلاج: فالأحجام الكبيرة من السوائل اللازمة للإنعاش تسبّب وذمة نسيجية في الجسم كلّه بما فيه داخل البطن فيرتفع الضغط داخل التجويف البطني.
This is the clearest example in the chapter of over-resuscitation causing harm — and of why the fluid is titrated against the response rather than delivered because the formula said so.
هذا أوضح مثال في الفصل على أذى فرط الإنعاش — وعلى سبب معايرة السائل بحسب الاستجابة بدلاً من إعطائه لأن الصيغة قالت ذلك.
13.13 · Cold Injury and Life After the Burn١٣٫١٣ · إصابة البرد والحياة بعد الحرق
Frostbite is the cold equivalent of a burn and is managed on similar principles with several specific rules. Affected tissue is white or waxy, hard, numb and insensate, and it becomes intensely painful on rewarming.
قضمة الصقيع هي المكافئ البارد للحرق ويقوم تدبيرها على مبادئ مشابهة مع عدّة قواعد محدّدة. والنسيج المصاب أبيض أو شمعي وقاسٍ وخدر وعديم الإحساس ويصير مؤلماً بشدّة عند إعادة التدفئة.
Two other injuries are treated like burns. Radiation burns occur after radiotherapy and after accidental exposure. Friction burns from road surfaces or machinery combine a burn with abrasion and embedded debris — so they need thorough cleaning, and retained grit tattoos the skin permanently if it is not removed.
ثمّة إصابتان أخريان تُعالَجان كالحروق. فحروق الإشعاع تحدث بعد المعالجة الشعاعية وبعد تعرّض عرَضي. وحروق الاحتكاك من أسطح الطرق أو الآلات تجمع حرقاً مع سحج وحطام منغرز — فتحتاج تنظيفاً شاملاً والحصى المتبقّي يوشم الجلد دائماً إن لم يُزَل.
The first dressing change after a burn is remembered by patients for years, and how it is handled shapes every one that follows.
أول تغيير ضماد بعد حرق يتذكّره المرضى سنوات وكيفية التعامل معه تشكّل كلّ ما يليه.
13.14 · When the Burn Is Not Survivable١٣٫١٤ · حين لا يكون الحرق قابلاً للنجاة
Some burns are not survivable. A very large burned area, particularly combined with extremes of age, severe inhalation injury or significant existing disease, may make death inevitable whatever is done — and that judgement is made by the senior team, with the family, on the clinical picture rather than the surface area alone.
بعض الحروق غير قابلة للنجاة. فمساحة محروقة كبيرة جداً خاصّةً مع طرفَي العمر أو إصابة استنشاق شديدة أو مرض قائم كبير قد تجعل الموت حتمياً مهما فُعل — وذلك الحكم يتّخذه الفريق الأقدم مع الأسرة بناءً على الصورة السريرية لا على المساحة وحدها.
Once that decision is made, the nursing does not reduce — it changes direction. The principle applies exactly: a decision not to escalate is never a decision to withdraw care.
بمجرّد اتّخاذ ذلك القرار لا تقلّ الرعاية التمريضية — بل تغيّر اتّجاهها. والمبدأ ينطبق تماماً: قرار عدم التصعيد ليس قرار سحب الرعاية أبداً.
A related matter runs through all wound and burn care: clinical photography. Photographs are genuinely valuable for tracking a wound, for handover and for referral — but they are identifiable patient information.
ثمّة مسألة ذات صلة تمتدّ عبر كلّ رعاية الجروح والحروق: التصوير السريري. فالصور قيّمة فعلاً لتتبّع جرح والتسليم والإحالة — لكنها معلومات تحدّد هوية المريض.
13.15 · Wounds and Skin Integrity١٣٫١٥ · الجروح وسلامة الجلد
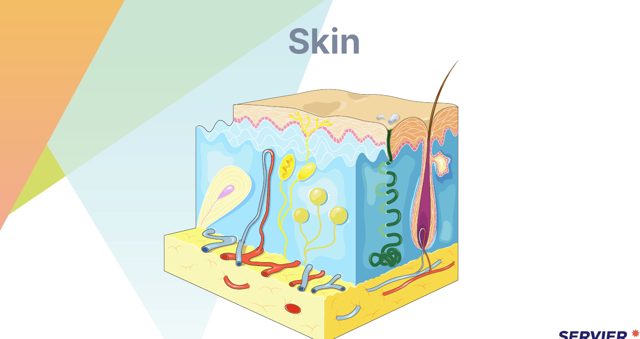
Wounds heal through overlapping phases — inflammation, proliferation with granulation and new vessels, and maturation in which the scar remodels and strengthens over months. Healing is delayed by poor perfusion, infection, malnutrition, diabetes, smoking, steroids, pressure and moisture — and most of those are things a nurse influences.
الجروح تلتئم عبر أطوار متداخلة — التهاب وتكاثر بتحبّب وأوعية جديدة ونضج تُعاد فيه قولبة الندبة وتقوى عبر أشهر. والالتئام يتأخّر بسوء الإرواء والعدوى وسوء التغذية والسكّري والتدخين والستيرويدات والضغط والرطوبة — ومعظمها أمور يؤثّر فيها التمريض.
Pressure injury results from sustained pressure, or pressure combined with shear, over a bony prominence.
إصابة الضغط تنتج عن ضغط مستمرّ أو ضغط مع قصّ فوق نتوء عظمي.
13.16 · When a Wound or the Skin Becomes an Emergency١٣٫١٦ · حين يصير الجرح أو الجلد طارئاً
Wound dehiscence is separation of the layers of a surgical wound; evisceration is protrusion of abdominal contents through it. The risk factors are the familiar ones — obesity, malnutrition, infection, steroids, diabetes, coughing and straining — and a serosanguineous discharge from a wound is often the warning sign that precedes it.
انفتاح الجرح هو انفصال طبقات جرح جراحي؛ والاندلاق بروز محتويات البطن عبره. وعوامل الخطر المألوفة — سمنة وسوء تغذية وعدوى وستيرويدات وسكّري وسعال وإجهاد — والإفراز المصلي الدموي من جرح كثيراً ما يكون العلامة المنذرة السابقة له.
- PAIN OUT OF ALL PROPORTION to the appearance
- Early on the skin does not look bad enough — which is why it is missed
- Rapidly spreading, systemically very unwell
- Later: dusky or purple skin, blisters, crepitus, anaesthesia over the area
- Surgical emergency — urgent debridement
- Escalate on the pain and the systemic state, not the skin
- Hot, red, swollen, tender area with a diffuse border
- Fever and malaise
- Pain is proportionate to the appearance
- Progresses over days, not hours
- Antibiotics, elevation, and marking the border to track spread
- Look for the entry point — tinea between the toes is a classic
The single discriminator worth carrying: in cellulitis the pain fits what you see; in necrotising fasciitis it does not — and a patient in severe pain who looks systemically dreadful with unimpressive skin is the one to escalate immediately.
العامل المميِّز الوحيد الجدير بالتذكّر: أنّ الألم في التهاب النسيج الخلوي يتناسب مع ما يُرى، أمّا في التهاب اللفافة الناخر فلا يتناسب — والمريض الذي يعاني ألماً شديداً ويبدو في حالة جهازية مريعة مع جلد لا يوحي بخطورة هو من يجب تصعيد أمره فوراً.
13.17 · Leg Ulcers and the Diabetic Foot١٣٫١٧ · قرح الساق والقدم السكّرية
A chronic leg ulcer is venous, arterial or mixed, and telling them apart is the most consequential distinction in wound care — because the treatments are opposite.
قرحة الساق المزمنة وريدية أو شريانية أو مختلطة والتمييز بينها أهمّ تمييز في رعاية الجروح — فالعلاجان متعاكسان.
- Gaiter area — above the medial malleolus
- Shallow, irregular edges, large
- Heavy exudate
- Surrounding skin: brown staining, eczema, oedema
- Pain relieved by elevation
- Pulses present; leg warm
- Toes, foot, pressure points, lateral malleolus
- Deep, punched-out, well-defined edges
- Little exudate
- Surrounding skin: shiny, hairless, pale
- Pain WORSE on elevation, better hanging down
- Pulses absent or weak; foot cold
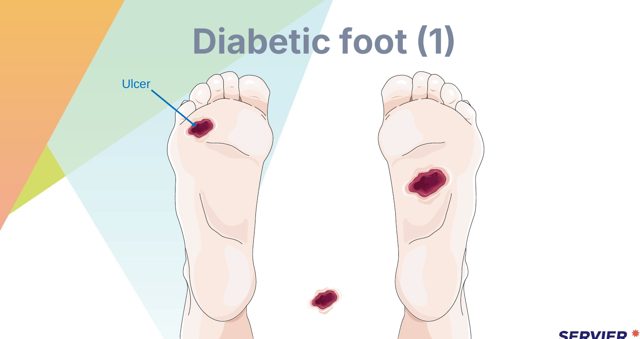
The diabetic foot ulcer arises from three things acting together, and knowing which are present directs the treatment.
قرحة القدم السكّرية تنشأ من ثلاثة أمور تعمل معاً ومعرفة الموجود منها توجّه العلاج.
13.18 · Device Injury, Skin Conditions and Scars١٣٫١٨ · أذيّة الأجهزة والحالات الجلدية والندبات
A large proportion of pressure injuries acquired in hospital are caused by medical devices rather than by lying on a mattress — and they are missed because nobody looks under the equipment.
نسبة كبيرة من إصابات الضغط المكتسَبة في المستشفى تسبّبها الأجهزة الطبّية لا الاستلقاء على مرتبة — وتُغفَل لأن أحداً لا ينظر تحت المعدّات.
- Raised but stays within the boundary of the original wound
- Often improves over months
- Responds to pressure garments and silicone
- The commoner of the two
- Extends BEYOND the original wound margin into normal skin
- Does not regress
- Commonly recurs after excision — sometimes worse
- Commoner in darker skin, and on the chest, shoulders and earlobes
Both are treated with pressure garments, silicone, massage and intralesional injection per specialist plan — and the nursing contribution is adherence, because these are worn and done for months, and the results are slow enough that people stop.
كلتاهما تُعالَجان بملابس ضغط وسيليكون وتدليك وحقن داخل الآفة بخطة اختصاصي — والمساهمة التمريضية الالتزام فهذه تُلبَس وتُفعَل أشهراً والنتائج بطيئة كفايةً ليتوقّف الناس.
13.19 · Burns in the Saudi Setting١٣٫١٩ · الحروق في السياق السعودي
The commonest burns in this setting follow a predictable domestic pattern, and knowing it directs prevention advice.
أشيع الحروق في هذا السياق تتبع نمطاً منزلياً متوقّعاً ومعرفته توجّه نصيحة الوقاية.
Traditional first aid remedies deserve to be addressed explicitly rather than criticised after the event, because they are widely used and cause real harm.
علاجات الإسعاف التقليدية تستحقّ أن يُتطرَّق إليها صراحةً لا أن تُنتقَد بعد الحدث، فهي واسعة الاستخدام وتسبّب أذىً حقيقياً.
- Toothpaste, oil, butter, egg white, coffee grounds, henna
- They trap heat and deepen the burn
- They introduce infection
- They obscure assessment of depth
- And removing them causes further pain and damage
- Ask what was applied — without reproach
- Families will not volunteer it if they expect criticism
- Teach the correct first aid before it is needed — at any contact
- Cool water, twenty minutes, cling film, nothing else
- And say why, because ‘don’t’ without a reason does not travel
Two further contextual points. Mass gatherings carry fire and burn risk from cooking in temporary accommodation and from crowding, and staff working in those settings should know the local emergency and evacuation plan before the season. And the climate: high ambient temperature means a burned patient dehydrates faster and hyperthermia is a genuine additional risk, while the sun protection needed for healing scars is harder to achieve and more important here than almost anywhere.
نقطتان سياقيتان أخريان. فالتجمّعات الكبرى تحمل خطر الحريق والحرق من الطهي في سكن مؤقّت ومن الازدحام، وينبغي أن يعرف الطاقم العامل في تلك البيئات خطة الطوارئ والإخلاء المحلّية قبل الموسم. أمّا المناخ، فالحرارة المحيطة العالية تعني أن المريض المحروق يُصاب بالجفاف أسرع وأن فرط الحرارة خطر إضافي حقيقي، بينما الحماية من الشمس اللازمة للندبات الملتئمة أصعب تحقيقاً وأهمّ هنا من أيّ مكان تقريباً.
Test yourselfالاختبار الذاتي
Loading… جارٍ التحميل…
Loading… جارٍ التحميل…
Loading… جارٍ التحميل…