اللَّهُمَّ انْفَعْنِي بِمَا عَلَّمْتَنِي، وَعَلِّمْنِي مَا يَنْفَعُنِي، وَزِدْنِي عِلْمًا“O Allah, benefit me by what You have taught me, teach me what benefits me, and increase me in knowledge.”
«رَبِّ زِدْنِي عِلْمًا»“My Lord, increase me in knowledge.” Qur’an, Ṭā-Hā 20:114 · سورة طه، الآية ١١٤
Surgical safety checklist (Sign In, Time Out, Sign Out)قائمة التحقق من السلامة الجراحية (الدخول، الوقفة، الخروج)
Three phases: Sign In before induction of anaesthesia, Time Out before the incision (the whole team introduces themselves and confirms patient, site and procedure aloud) and Sign Out before the patient leaves theatre (counts correct, specimens labelled).ثلاث مراحل: تسجيل الدخول قبل بدء التخدير، والوقفة قبل الشق (يعرّف أعضاء الفريق جميعاً بأنفسهم ويؤكَّد المريض والموضع والإجراء بصوت مسموع)، وتسجيل الخروج قبل مغادرة المريض غرفة العمليات (صحة العدّ ووسم العيّنات).
Surgical countالعدّ الجراحي
Count of instruments, swabs, needles and sharps performed before the procedure, during it as cavities are closed and at the end, by two people counting together out loud.عدّ الأدوات والشاش والإبر والأدوات الحادة قبل الإجراء وأثناءه عند إغلاق التجاويف وفي نهايته، يقوم به شخصان معاً بصوت مسموع.
Malignant hyperthermiaفرط الحرارة الخبيث
Rare inherited reaction to volatile inhaled agents and suxamethonium with uncontrolled muscle calcium release; the earliest sign is a rapidly rising end-tidal CO2 with tachycardia and rigidity, fever is late, and management is to stop the trigger, give 100% oxygen and dantrolene.تفاعل وراثي نادر مع المخدّرات الاستنشاقية المتطايرة والسكسينيل كولين مع تحرّر غير مضبوط للكالسيوم في العضلة؛ وأبكر علاماته ارتفاع سريع في ثاني أكسيد الكربون في نهاية الزفير مع تسرّع قلب وصلابة عضلية، أما الحمّى فمتأخرة، ويتمثّل التدبير في إيقاف العامل المحرِّض وإعطاء الأكسجين 100% والدانترولين.
A bleed that compresses the spinal cord after epidural analgesia and causes permanent paralysis if not decompressed within hours; the warning is a block that is denser or higher than expected, or one that was wearing off and returns.نزف يضغط على النخاع الشوكي بعد التسكين فوق الجافية ويسبّب شللاً دائماً إن لم يُفرَّج الضغط خلال ساعات؛ والإنذار هو حصار أشد أو أعلى مما هو متوقع، أو حصار كان يزول ثم عاد.
Mean cell volume (MCV)متوسط حجم الكرية (MCV)
The most useful single figure for classifying anaemia: low (microcytic) suggests iron deficiency or thalassaemia, normal suggests blood loss or chronic disease, and high (macrocytic) suggests vitamin B12 or folate deficiency.أنفع رقم منفرد لتصنيف فقر الدم: فالمنخفض (صغير الكريّات) يوحي بنقص الحديد أو الثلاسيميا، والطبيعي يوحي بفقد الدم أو المرض المزمن، والمرتفع (كبير الكريّات) يوحي بنقص فيتامين B12 أو الفولات.
Pernicious anaemiaفقر الدم الوبيل
Vitamin B12 deficiency from autoimmune loss of intrinsic factor in the stomach, giving macrocytic anaemia plus neurological features; it is treated with lifelong B12 injections because the absorption problem does not go away.نقص فيتامين B12 الناجم عن فقد مناعي ذاتي للعامل الداخلي في المعدة، ويعطي فقر دم كبير الكريّات مع أعراض عصبية؛ ويُعالَج بحقن B12 مدى الحياة لأن مشكلة الامتصاص لا تزول.
Sickle cell disease (vaso-occlusive crisis)داء الخلايا المنجلية (الأزمة الانسدادية الوعائية)
Inherited autosomal recessive disease in which abnormal haemoglobin distorts red cells into rigid sickles that block small vessels, causing severe pain and tissue infarction; crisis needs hydration, oxygen if hypoxic, and prompt, adequate strong opioid analgesia.مرض وراثي جسمي متنحٍّ يشوّه فيه الهيموغلوبين الشاذ الكريات الحمر إلى أشكال منجلية صلبة تسدّ الأوعية الصغيرة، فتسبّب ألماً شديداً واحتشاء نسيجياً؛ وتستلزم الأزمة الإماهة والأكسجين عند نقص الأكسجة وتسكيناً فورياً كافياً بمواد أفيونية قوية.
Acute chest syndromeمتلازمة الصدر الحادة
Complication of sickle cell disease with fever, chest pain, breathlessness, hypoxia and a new infiltrate; the commonest cause of death in sickle cell disease and a postoperative complication that needs escalation at the first sign.مضاعفة لداء الخلايا المنجلية تتظاهر بحمّى وألم صدر وضيق نفس ونقص أكسجة وارتشاح جديد؛ وهي أشيع أسباب الوفاة في المرض وقد تحدث بعد الجراحة، وتستلزم التصعيد عند أول علامة.
G6PD deficiencyنقص إنزيم G6PD
X-linked inherited enzyme defect, highly prevalent in the region, in which red cells lack protection against oxidative stress so an oxidant precipitates acute haemolysis; management is explicit avoidance of the triggers.عيب إنزيمي وراثي مرتبط بالصبغي X وشائع جداً في المنطقة، تفتقر فيه الكريات الحمر إلى الحماية من الإجهاد التأكسدي فيسبّب أي مؤكسِد انحلالاً حاداً؛ ويقوم التدبير على تجنّب المحرِّضات تجنّباً صريحاً.
Haemophiliaالهيموفيليا (الناعور)
Inherited, X-linked recessive deficiency of a clotting factor affecting mainly males, causing bleeding into joints and muscles; factor replacement is given first and early, with no intramuscular injections, aspirin or NSAIDs.نقص وراثي متنحٍّ مرتبط بالصبغي X في أحد عوامل التخثّر يصيب الذكور بصورة رئيسية، ويسبّب نزفاً في المفاصل والعضلات؛ ويُعطى تعويض العامل أولاً ومبكراً، مع منع الحقن العضلي والأسبرين ومضادات الالتهاب غير الستيرويدية.
Neutropenic sepsisالإنتان في قلّة العدلات
Medical emergency in which a low neutrophil count removes the normal inflammatory response so that fever may be the only sign; broad-spectrum antibiotics are given within one hour without waiting for cultures.حالة طبية طارئة يُفقِد فيها انخفاض عدد العدلات الاستجابة الالتهابية الطبيعية، فقد تكون الحمّى العلامة الوحيدة؛ وتُعطى مضادات حيوية واسعة الطيف خلال ساعة دون انتظار نتائج الزرع.
Acute haemolytic transfusion reactionتفاعل انحلال الدم الحاد بعد نقل الدم
Reaction following ABO incompatibility that begins within minutes with fever, chills, flank pain and dark urine and can progress to renal failure, DIC and shock; as for every transfusion reaction, the first action is to stop the transfusion immediately.تفاعل يعقب عدم توافق ABO ويبدأ خلال دقائق بحمّى وقشعريرة وألم خاصرة وبول داكن، وقد يتطوّر إلى فشل كلوي وتخثّر منتشر داخل الأوعية وصدمة؛ وكما في كل تفاعل نقل دم، يكون الإجراء الأول إيقاف النقل فوراً.
Recognise neutropenic sepsis as an emergency and apply protective measures.
تمييز الإنتان بقلّة العدلات بوصفه حالة طارئة وتطبيق التدابير الواقية.
23
Carry out the transfusion checking procedure and monitor correctly.
تنفيذ إجراء التحقّق لنقل الدم والمراقبة بشكل صحيح.
24
Recognise transfusion reactions and state the first action.
تمييز تفاعلات نقل الدم وبيان الإجراء الأول.
25
Apply the Saudi context: premarital screening, regional distribution and consanguinity.
تطبيق السياق السعودي: الفحص قبل الزواج والتوزّع الإقليمي وزواج الأقارب.
2
8.1 · Informed Consent and Preoperative Preparation٨٫١ · الموافقة المستنيرة والتحضير قبل الجراحة
The division of responsibility in informed consent is what the exam tests. The surgeon obtains the consent — explaining the procedure, the risks, the benefits and the alternatives. The nurse's role is to witness the signature, to confirm that it is given voluntarily, and to confirm that the patient appears to understand. The nurse does not explain the procedure and does not obtain the consent, as Part 01 Chapter 01 sets out.
تقسيم المسؤولية في الموافقة المستنيرة هو ما يختبره الامتحان. فالجرّاح يحصل على الموافقة — شارحاً الإجراء والمخاطر والفوائد والبدائل. ودور الممرضة أن تشهد التوقيع وتؤكّد أنه طوعي وتؤكّد أن المريض يبدو فاهماً. ولا تشرح الممرضة الإجراء ولا تحصل على الموافقة كما يبيّن الفصل الأول من الجزء الأول.
Two situations follow from that and both are commonly examined. If the patient says anything suggesting he does not understand — "I'm not really sure what they're doing" — stop and notify the surgeon to clarify before the form is signed. And the consent must be signed before any sedative premedication is given, because a sedated patient cannot give valid consent; if the sedative is due and the form is unsigned, the consent is dealt with first.
وموقفان يتبعان ذلك وكلاهما يُختبَر كثيراً. فإن قال المريض أيّ شيء يوحي بأنه لا يفهم — «لست متأكّداً تماماً مما يفعلونه» — يجب التوقّف وإبلاغ الجرّاح ليوضّح قبل توقيع النموذج. ويجب توقيع الموافقة قبل إعطاء أيّ مهدّئ قبل الجراحة، فالمريض المهدَّأ لا يستطيع إعطاء موافقة صحيحة؛ وإن حان موعد المهدّئ والنموذج غير موقّع فتُعالَج الموافقة أولاً.
Preoperative assessment covers the history, current medications, allergies — including latex and iodine — and previous anaesthetic problems in the patient or the family, which matters because malignant hyperthermia is inherited. Baseline observations, weight, and the investigations the procedure requires are recorded. Anticoagulants and antiplatelets are managed according to protocol, and diabetes medication is planned as Chapter 03 sets out. A venous thromboembolism risk assessment is completed and prophylaxis prescribed.
والتقييم قبل الجراحة يغطّي القصّة والأدوية الحالية والحساسيات بما فيها اللاتكس واليود ومشكلات التخدير السابقة لدى المريض أو أسرته، وهذا يهمّ لأن فرط الحرارة الخبيث موروث. وتُسجَّل القياسات الأساسية والوزن والاستقصاءات التي يتطلّبها الإجراء. ومضادّات التخثّر ومضادّات الصفيحات تُدبَّر وفق البروتوكول، ويُخطَّط دواء السكّري كما يبيّن الفصل الثالث. ويُستكمَل تقييم خطر الانصمام الخثاري الوريدي وتُوصَف الوقاية.
Preoperative teaching is what PREVENTS postoperative complications, and it is taught before surgery because a patient in pain and drowsy afterwards will not learn anything.
والتعليم قبل الجراحة هو ما يمنع مضاعفات ما بعد الجراحة، ويُقدَّم قبلها لأن المريض المتألّم النعسان بعدها لن يتعلّم شيئاً.
1
Deep breathing and the incentive spirometer
Practised BEFORE, so he can do it after — which is what prevents atelectasis and chest infection.
التنفّس العميق ومقياس التنفّس التحفيزي — يُتدرَّب عليهما قبل الجراحة ليتمكّن المريض من أدائهما بعدها، وهذا ما يمنع الانخماص وعدوى الصدر.
2
How to SUPPORT the wound when coughing
A pillow or his hands — because a patient afraid the wound will burst does not cough, and then gets a chest infection.
كيفية دعم الجرح عند السعال — بوسادة أو بيديه، لأن المريض الذي يخشى انفتاح الجرح لا يسعل، ثم يُصاب بعدوى في الصدر.
3
Leg exercises and early mobilisation
And WHY — thromboembolism prevention, said as a reason rather than an instruction.
تمارين الساقين والتحريك المبكّر — ولماذا: الوقاية من الانصمام الخثاري، ويُذكر ذلك بوصفه سبباً لا أمراً.
4
Pain management and how to ask for it
Ask BEFORE the pain is severe — and controlling it is what lets him move and breathe.
تدبير الألم وكيف يطلبه — قبل أن يشتدّ الألم، فضبطه هو ما يتيح للمريض أن يتحرّك ويتنفّس.
5
What to expect on waking
Drains, catheters, oxygen, drips and monitors — NAMED in advance, because waking attached to things nobody mentioned is frightening.
ماذا يتوقّع عند الاستيقاظ — المنازح والقثاطر والأكسجين والتسريب الوريدي وأجهزة المراقبة، تُسمّى مسبقاً لأن الاستيقاظ وهو موصول بأشياء لم يذكرها أحد أمر مخيف.
🚩
Watch out
تنبيه
If the consent form is unsigned and the premedication is due, deal with the consent first. A sedated patient cannot give valid consent.
إن كان نموذج الموافقة غير موقّع وحان موعد الدواء قبل الجراحة فتُعالَج الموافقة أولاً. فالمريض المهدَّأ لا يستطيع إعطاء موافقة صحيحة.
⭐
Key point
نقطة أساسية
A patient who says he does not understand what will be done has not given informed consent. Stop and notify the surgeon — do not explain it yourself and proceed.
المريض الذي يقول إنه لا يفهم ما سيُجرى لم يعطِ موافقة مستنيرة. يجب التوقّف وإبلاغ الجرّاح — وعدم تولّي الشرح شخصياً ثم المضيّ قدماً.
3
8.2 · Risk Classification and Preparation Detail٨٫٢ · تصنيف الخطر وتفاصيل التحضير
1
ASA I
A normal healthy patient.
الأولى — مريض سليم طبيعي.
2
ASA II
Mild systemic disease — controlled hypertension, a smoker.
الثانية — مرض جهازي خفيف: ارتفاع ضغط الدم المضبوط، مدخّن.
3
ASA III
SEVERE systemic disease — poorly controlled diabetes, COPD.
الثالثة — مرض جهازي شديد: سكّري سيّئ الضبط، داء الانسداد الرئوي المزمن.
4
ASA IV
Severe systemic disease that is a constant threat to life.
الرابعة — مرض جهازي شديد يشكّل تهديداً دائماً للحياة.
5
ASA V
A moribund patient not expected to survive without the operation.
الخامسة — محتضر لا يُتوقّع بقاؤه دون العملية.
6
ASA VI
A declared brain-dead organ donor. And ‘E’ is added for an EMERGENCY — which raises the risk at every grade.
السادسة — متبرّع بأعضاء معلَن موته الدماغي؛ وتُضاف E للحالة الطارئة — مما يرفع الخطر في كل درجة.
It grades fitness for anaesthesia and is recorded before every operation — and the point that matters on a ward: it describes the patient, not the operation, and a high grade is a reason to optimise, not simply to accept a worse outcome.
ويُدرّج اللياقة للتخدير ويُسجَّل قبل كلّ عملية — والمهمّ في الجناح: أنه يصف المريض لا العملية والدرجة العالية سبب للتحسين لا لقبول نتيجة أسوأ.
•Two preparation points commonly got wrongنقطتان في التحضير كثيراً ما تُنفَّذان خطأً
HAIR REMOVAL — clippers, never a razorDone ONLY if the hair will interfere with the procedure, and as close to the time of surgery as possible. A razor causes microscopic skin trauma that increases surgical site infection — the instrument matters more than the timing.إزالة الشعر — بمقصّ آلي لا بشفرة حلاقة أبداً: وتُجرى فقط إن كان الشعر سيعيق الإجراء، وقبل موعد الجراحة بأقرب وقت ممكن. فالشفرة تسبّب رضّاً مجهرياً في الجلد يزيد عدوى الموقع الجراحي — فنوع الأداة أهمّ من التوقيت.
And FASTING is not ‘nil by mouth from midnight’Modern guidance allows CLEAR FLUIDS up to a defined short interval before surgery. Prolonged fasting causes dehydration, hypoglycaemia, discomfort and delirium, and does not make the stomach emptier. Follow the actual interval, and stop starving patients from midnight for an afternoon list.والصيام ليس «لا شيء بالفم من منتصف الليل» — فالإرشادات الحديثة تسمح بالسوائل الصافية حتى فترة قصيرة محدّدة قبل الجراحة. فالصيام المطوّل يسبّب الجفاف وهبوط سكّر الدم والانزعاج والهذيان، ولا يجعل المعدة أكثر فراغاً. ويُتّبع الفاصل الزمني المحدّد فعلياً، ويجب التوقّف عن تجويع المرضى منذ منتصف الليل لقائمة جراحية بعد الظهر.
1
SIGN IN — BEFORE induction of anaesthesia
Confirms the patient’s identity, the site and procedure, consent, allergies, airway risk and blood loss risk. Before he is asleep, so he can still answer.
تسجيل الدخول — قبل بدء التخدير: يؤكّد هوية المريض والموضع والإجراء والموافقة والحساسيات وخطر المجرى الهوائي وخطر فقد الدم. وذلك قبل أن ينام المريض كي يظلّ قادراً على الإجابة.
2
TIME OUT — BEFORE the incision
The whole team pauses.Everyone introduces themselves by name and role; the patient, site and procedure are confirmed OUT LOUD; and anticipated critical events, antibiotic prophylaxis and imaging are checked.
الوقفة — قبل الشقّ: يتوقّف الفريق كلّه ويعرّف كلّ فرد بنفسه بالاسم والدور؛ ويُؤكَّد المريض والموضع والإجراء بصوت عالٍ؛ وتُراجَع الأحداث الحرجة المتوقَّعة والوقاية بالمضادّات الحيوية والتصوير.
3
SIGN OUT — BEFORE the patient leaves theatre
Procedure recorded, INSTRUMENT, SWAB AND SHARPS COUNTS correct, specimens labelled, equipment problems noted, and recovery concerns handed over.
تسجيل الخروج — قبل مغادرة المريض غرفة العمليات: تُسجَّل العملية، وتُطابَق عدّات الأدوات والشاش والحادّات، وتُوسَم العيّنات، وتُدوَّن مشكلات المعدّات، وتُسلَّم شواغل الإفاقة.
Knowing there are THREE phases rather than one is what the exam tests — and the introductions are not courtesy: a team where people know each other’s names speaks up more readily, and speaking up is what the checklist exists to enable.
ومعرفة أن المراحل ثلاث لا واحدة هو ما يختبره الامتحان — وتعريف الأعضاء بأنفسهم ليس مجرّد مجاملة: فالفريق الذي يعرف أفراده أسماء بعضهم يتحدّث بسهولة أكبر، والتحدّث هو ما وُضعت القائمة لتمكينه.
🚩
Watch out
تنبيه
Remove hair with clippers, never a razor, and only if it will interfere with the procedure. Shaving the night before measurably increases surgical site infection.
يُزال الشعر بمقصّ آلي لا بشفرة حلاقة أبداً، وفقط إن كان سيعيق الإجراء. فالحلاقة في الليلة السابقة تزيد عدوى الموقع الجراحي بشكل قابل للقياس.
🔑
Memory aid
مفتاح للحفظ
The safety checklist has three phases: sign in before induction, time out before incision, sign out before the patient leaves theatre.
قائمة تحقّق السلامة ثلاث مراحل: تسجيل دخول قبل بدء التخدير ووقفة قبل الشقّ وتسجيل خروج قبل مغادرة المريض غرفة العمليات.
4
8.3 · Optimising the Patient Before Surgery٨٫٣ · تحسين حالة المريض قبل الجراحة
Preoperative anaemia is the single most MODIFIABLE predictor of transfusion and of a worse surgical outcome — and it is routinely found only on the MORNING of surgery, when nothing can be done about it.
وفقر الدم قبل الجراحة هو أكثر العوامل المنبّئة بنقل الدم وبنتيجة جراحية أسوأ قابليةً للتعديل على الإطلاق — ويُكتشَف روتينياً صباح الجراحة فقط، حين لا يمكن فعل شيء حياله.
•Identifying it WEEKS in advance is the interventionالتعرّف عليه قبل أسابيع هو التدخّل نفسه
Check the haemoglobin at PRE-ASSESSMENTNot on admission — which gives time to treat it.يُفحص الهيموغلوبين عند التقييم المسبق — لا عند الدخول، مما يتيح وقتاً لعلاجه.
Investigate the CAUSE, do not just transfuseIron deficiency is the commonest and is treatable — and in a man or a post-menopausal woman it needs investigating in its own right.يُبحث عن السبب ولا يُكتفى بنقل الدم. نقص الحديد هو الأشيع وهو قابل للعلاج — وفي الرجل أو المرأة بعد سنّ اليأس يستلزم استقصاءً مستقلاً لسببه.
Treat it, and DELAY elective surgery if neededA few weeks of iron is better than a transfusion — for the outcome and for the risk.يُعالَج فقر الدم وتُؤجَّل الجراحة الاختيارية إن لزم. فبضعة أسابيع من الحديد أفضل من نقل الدم — للنتيجة وللمخاطر.
1
Pillar 1 — OPTIMISE his own red cell mass
Before surgery — which is the anaemia work above.
الركيزة الأولى — تحسين كتلة الكريّات الحمراء لدى المريض نفسه قبل الجراحة، وهو عمل فقر الدم المذكور أعلاه.
2
Pillar 2 — MINIMISE blood loss
During and after — meticulous surgical technique, tranexamic acid where indicated, cell salvage, and reducing the volume and frequency of blood tests, which is a real cause of anaemia in a long stay.
الركيزة الثانية — تقليل فقد الدم أثناء الجراحة وبعدها: تقنية جراحية دقيقة، وحمض الترانيكساميك عند وجود استطباب، واسترداد خلايا الدم، وتقليل حجم الفحوص الدموية وتكرارها، فهي سبب حقيقي لفقر الدم في الإقامة الطويلة.
3
Pillar 3 — TOLERATE anaemia where it is safe
Using a RESTRICTIVE transfusion threshold — because transfusing more is not transfusing better, and a restrictive threshold gives outcomes as good or better in most patients.
الركيزة الثالثة — تحمُّل فقر الدم حيث يكون آمناً: باعتماد عتبة تقييدية لنقل الدم — لأن نقل المزيد من الدم لا يعني نقلاً أفضل، وتعطي العتبة التقييدية نتائج مماثلة أو أفضل لدى معظم المرضى.
The third pillar changes practice most: the reflex to transfuse a NUMBER rather than a PATIENT is what patient blood management exists to correct. Transfuse for a clinical reason, one unit at a time, and reassess — not to reach a target figure.
والركيزة الثالثة الأكثر تغييراً للممارسة: فمنعكس نقل الدم تبعاً لرقم لا لمريض هو ما وُجد تدبير دم المريض لتصحيحه. يُنقل الدم لسبب سريري، وحدة واحدة في كل مرة، مع إعادة التقييم — لا لبلوغ رقم مستهدف.
FRAILTY predicts surgical outcome better than chronological age does, and it is ASSESSED rather than assumed from the date of birth.
والهشاشة تتنبأ بنتائج الجراحة أفضل من العمر الزمني، وهي تُقيَّم ولا تُفترَض من تاريخ الميلاد.
•What it changesما الذي يغيّره
Higher risk of delirium, complications and loss of independenceProlonged stay, and discharge to a place other than home — which is often what matters most to him.خطر أعلى للهذيان والمضاعفات وفقد الاستقلال، وإقامة أطول، والخروج إلى مكان غير المنزل — وهو غالباً أكثر ما يهمّ المريض.
So the assessment changes the CONVERSATIONA realistic discussion of what he is likely to be able to DO afterwards — not only whether he survives the operation, which is the question usually answered instead.فالتقييم يغيّر الحديث — نقاش واقعي لما يُرجَّح أن يستطيع المريض فعله بعد الجراحة، لا مجرّد نجاته من العملية، وهو السؤال الذي يُجاب عنه عادةً بدلاً من ذلك.
And it changes the PLANAnaesthetic technique, delirium prevention, early mobilisation, nutrition, and discharge planning started BEFORE admission rather than after.ويغيّر الخطة — تقنية التخدير ومنع الهذيان والتحريك المبكّر والتغذية، والتخطيط للخروج الذي يبدأ قبل الدخول إلى المستشفى لا بعده.
Enhanced recovery after surgery is a bundle designed around ONE idea: return the patient to normal function as quickly as possible.
والتعافي المعزّز بعد الجراحة حزمة مصمّمة حول فكرة واحدة: إعادة المريض للوظيفة الطبيعية بأسرع ما يمكن.
1
BEFORE — avoid prolonged fasting
Carbohydrate loading where the protocol allows, optimise anaemia and comorbidity, and set expectations — a patient who knows he will be walking that evening usually is.
قبل الجراحة — تجنُّب الصيام المطوّل: تحميل الكربوهيدرات حيث يسمح البروتوكول، وتحسين فقر الدم والأمراض المرافقة، وتهيئة التوقّعات — فالمريض الذي يعلم أنه سيمشي مساء ذلك اليوم يفعل ذلك عادةً.
2
DURING — minimally invasive where possible
Avoid fluid overload, maintain normothermia, and use regional anaesthesia and opioid-sparing analgesia.
أثناء الجراحة — جراحة طفيفة التوغّل حيثما أمكن: تجنُّب فرط السوائل، والحفاظ على حرارة الجسم الطبيعية، واستخدام التخدير الناحي وتسكين الألم الموفّر للأفيونيات.
3
AFTER — EARLY oral intake
Eating and drinking on the day, not when bowel sounds return — the change people find hardest to believe.
بعد الجراحة — تناول فموي مبكّر: الأكل والشرب في اليوم نفسه، لا عند عودة أصوات الأمعاء — وهو التغيير الذي يصعب على الناس تصديقه.
4
EARLY mobilisation
Out of bed the same day — which prevents chest infection, thromboembolism, weakness and delirium at once.
تحريك مبكّر — الخروج من السرير في اليوم نفسه، وهو ما يمنع عدوى الصدر والانصمام الخثاري والضعف والهذيان معاً.
5
Remove lines and catheters EARLY
Every device is a reason not to walk and a route for infection.
نزع الخطوط والقثاطر مبكّراً — فكلّ جهاز سبب لعدم المشي ومدخل للعدوى.
6
And multimodal analgesia
Regular paracetamol and NSAIDs where safe, sparing opioids — because opioids are what stop him eating, moving and opening his bowels.
وتسكين متعدّد الأنماط — باراسيتامول بانتظام ومضادّات الالتهاب غير الستيرويدية حيث يكون آمناً، مع تجنيب الأفيونيات — لأنها ما يمنع المريض من الأكل والحركة والتبرّز.
⭐
Key point
نقطة أساسية
Preoperative anaemia is the most modifiable predictor of transfusion and poor outcome. Identify it weeks in advance so the cause can be treated, not on the morning of surgery.
فقر الدم قبل الجراحة هو أكثر العوامل المنبّئة بنقل الدم وبسوء النتيجة قابليةً للتعديل. ينبغي تحديده قبل أسابيع ليمكن علاج السبب، لا في صباح الجراحة.
🔑
Memory aid
مفتاح للحفظ
The three pillars of patient blood management: optimise the patient's own red cells, minimise blood loss, and optimise tolerance of anaemia.
ركائز تدبير دم المريض الثلاث: تحسين كريّات المريض الحمر وتقليل فقد الدم وتحسين تحمّل فقر الدم.
⭐
Key point
نقطة أساسية
Frailty predicts surgical outcome better than age. Assess it rather than assuming it from the date of birth, and let it change the plan.
الهشاشة تتنبّأ بنتيجة الجراحة أفضل من العمر. ينبغي تقييمها لا افتراضها من تاريخ الميلاد، وأن تُغيِّر الخطة.
5
8.4 · In Theatre: Roles, Sterility and Safety٨٫٤ · في غرفة العمليات: الأدوار والعقامة والسلامة
The scrub nurse is sterile: she sets up and maintains the sterile field, hands instruments to the surgeon, and takes part in the count. The circulating nurse is not sterile and works outside the field: she manages the room, obtains additional supplies, positions the patient, documents, performs the count with the scrub nurse, and — the part that matters most — acts as the patient's advocate while he is unable to speak for himself.
الممرضة المعقّمة (ممرضة الغسل الجراحي) تكونمعقّمة: فهي تهيّئ الحقل المعقّم وتحافظ عليه وتناول الجرّاح الأدوات وتشارك في العدّ. والممرضة الجوّالةغير معقّمة وتعمل خارج الحقل: فتدير الغرفة وتُحضر المستلزمات الإضافية وتضبط وضعية المريض وتوثّق وتؤدّي العدّ مع الممرضة المعقّمة، وتعمل — وهذا هو الجزء الأهمّ — مدافعةً عن المريض بينما لا يستطيع الكلام عن نفسه.
The principles of the sterile field: only sterile touches sterile; the edges of a sterile drape or package are not sterile, conventionally a border of about 2.5 centimetres; anything below waist or table level is considered contaminated; a sterile field is never left unattended and never turned your back on; moisture wicks contamination through drapes, so wet is contaminated; and reaching over the sterile field contaminates it — which is the single most examined breach.
ومبادئ الحقل المعقّم: المعقّم يلامس المعقّم فقط؛ وحواف الغطاء أو العبوة المعقّمة ليست معقّمة، وتُعتبر عادةً حاشية بعرض نحو ٢٫٥ سنتيمتر؛ وكلّ ما هو تحت مستوى الخصر أو الطاولة يُعدّ ملوّثاً؛ والحقل المعقّم لا يُترَك دون مراقبة ولا يُدار له الظهر؛ والرطوبة تنقل التلوّث عبر الأغطية فالمبلّل ملوّث؛ والمدّ فوق الحقل المعقّم يلوّثه — وهو أكثر الخروقات اختباراً.
The surgical COUNT of instruments, swabs, needles and sharps is performed BEFORE the procedure, DURING it as cavities are closed, and AT THE END — by two people, counting together, out loud.
وعدّ الأدوات والشاش والإبر والحادّات يُجرى قبل الإجراء وأثناءه عند إغلاق التجاويف وفي نهايته — بشخصين يعدّان معاً بصوت عالٍ.
•And what happens when it does not tallyوما يحدث عندما لا يتطابق العدّ
The count is repeatedAnd the surgeon is informed immediately — not at the end of the list.يُعاد العدّ — ويُبلَّغ الجرّاح فوراً، لا في نهاية القائمة الجراحية.
The wound and the theatre are searchedIncluding the floor, the bins and the drapes.يُفتَّش الجرح وغرفة العمليات، بما في ذلك الأرضية وسلال النفايات والأغطية.
And an X-ray before the patient leavesA retained foreign object is a NEVER EVENT — and the count is not a formality to be signed off to keep the list moving.وتُجرى صورة شعاعية قبل مغادرة المريض — فالجسم الأجنبي المتروك «حدث لا يجوز وقوعه»، والعدّ ليس إجراءً شكلياً يُوقَّع عليه لإبقاء القائمة الجراحية سائرة.
Two intraoperative harms the nurse guards against: positioning injury, since an anaesthetised patient cannot feel pressure or report a stretched nerve, so bony prominences are padded and limbs supported in a neutral position; and inadvertent hypothermia, from cold theatres, exposure and cold fluids, which increases bleeding, infection and cardiac events — prevented with warmed blankets, forced air warming and warmed intravenous fluids.
وضرران أثناء العملية تتوقّاهما الممرضة: إصابة الوضعية، فالمريض المخدَّر لا يشعر بالضغط ولا يستطيع الإبلاغ عن عصب مشدود، فتُبطَّن النتوءات العظمية وتُسنَد الأطراف في وضعية محايدة؛ وانخفاض الحرارة غير المقصود من غرف باردة وكشف وسوائل باردة، ويزيد النزف والعدوى والأحداث القلبية — ويُمنَع بأغطية مدفّأة وتدفئة بالهواء المدفوع وسوائل وريدية مدفّأة.
🔑
Memory aid
مفتاح للحفظ
Sterile touches sterile only. Edges are not sterile, below waist level is contaminated, wet is contaminated, and reaching over the field contaminates it.
المعقّم يلامس المعقّم فقط. والحواف ليست معقّمة، وتحت مستوى الخصر ملوّث، والمبلّل ملوّث، والمدّ فوق الحقل يلوّثه.
🚩
Watch out
تنبيه
A count discrepancy is reported to the surgeon immediately and the item is searched for, with imaging if needed. It is never recorded as correct to save time.
تباين العدّ يُبلَّغ للجرّاح فوراً ويُبحَث عن الغرض مع تصوير إن لزم. ولا يُسجَّل صحيحاً لتوفير الوقت أبداً.
6
8.5 · Theatre Safety and Handover٨٫٥ · سلامة غرفة العمليات والتسليم
Surgical FIRE is rare but catastrophic, and it needs THREE things present together.
وحريق غرفة العمليات نادر لكنه كارثي ويحتاج ثلاثة أمور معاً.
IGNITIONusually diathermy or a laserمصدر إشعال — عادةً الكيّ الكهربائي أو الليزر
FUELmost often alcohol-based skin preparation, or drapesوقود — غالباً التحضير الجلدي الكحولي، أو الستائر
OXIDISEROXYGEN, which pools under the drapesمؤكسِد — الأكسجين المتجمّع تحت الستائر
So prevention is breaking one of the three: let the alcohol preparation DRY COMPLETELY before draping, avoid pooling, use the lowest safe oxygen concentration and stop it before diathermy near the airway, and keep the diathermy in its holster when not in use. And if it happens: stop the gas flow, remove the burning material, extinguish, and care for the airway.
فالوقاية كسر أحد الثلاثة: يُترك التحضير الكحولي ليجفّ تماماً قبل التغطية، ويُتجنَّب تجمّعه، ويُستخدم أقلّ تركيز أكسجين آمن ويُوقَف قبل استعمال الكيّ الكهربائي قرب المجرى الهوائي، ويُحفَظ الكيّ الكهربائي في حاملته عند عدم استعماله. وإن وقع الحريق: يُقطَع تدفّق الغاز، وتُزال المادة المشتعلة، ويُخمَد الحريق، ويُعتنى بالمجرى الهوائي.
The handover from theatre to recovery is a recognised point at which INFORMATION IS LOST, so it is given in a structured way, with the whole receiving team listening and nobody doing anything else.
والتسليم من غرفة العمليات للإفاقة نقطة معروفة تُفقَد فيها المعلومات فيُعطى بطريقة منظّمة والفريق المستقبِل كلّه يُصغي ولا يفعل أحد شيئاً آخر.
1
The patient, the operation and the findings
What was done, and what was found.
المريض والعملية والموجودات — ما أُجري وما وُجد.
2
Anaesthetic technique and drugs given
Including analgesia, antiemetics, antibiotics and reversal, with times.
تقنية التخدير والأدوية المعطاة — بما فيها المسكّنات ومضادّات القيء والمضادّات الحيوية وعكس التخدير، بأوقاتها.
3
Blood loss and fluids
And whether blood was given or is on standby.
فقد الدم والسوائل — وهل أُعطي الدم أو هو جاهز في الانتظار.
4
Drains, packs, catheters and lines
What is in, where, and what must NOT be removed — and whether there is a pack that must come out.
المنازح والحشوات والقثاطر والخطوط الوريدية — ما هو موجود وأين، وما يجب ألّا يُنزع، وهل توجد حشوة يجب إخراجها.
5
Problems and anticipated problems
Airway difficulty, bleeding risk, and what to watch for.
المشكلات والمشكلات المتوقّعة — صعوبة المجرى الهوائي وخطر النزف وما يجب ترقّبه.
6
And the specific instructions
Position, oxygen, when he may drink, what to escalate and to whom — with a chance to ask questions before the anaesthetist leaves.
والتعليمات المحدّدة — الوضعية والأكسجين ومتى يجوز للمريض أن يشرب وما يجب تصعيده ولمن — مع فرصة للسؤال قبل مغادرة طبيب التخدير.
One caution about thromboprophylaxis worth repeating: graduated compression stockings are contraindicated in peripheral arterial disease, as Chapter 01 sets out, and also in severe leg oedema, dermatitis, recent skin graft and marked leg deformity. Check pulses and the skin before applying them, inspect underneath daily, and never fold them over, because a folded top forms a tourniquet.
وتحذير عن الوقاية من الخثار يستحقّ التكرار: الجوارب الضاغطة المتدرّجة ممنوعة في مرض الشرايين الطرفية كما يبيّن الفصل الأول، وكذلك في وذمة الساق الشديدة والتهاب الجلد والطعم الجلدي الحديث وتشوّه الساق الملحوظ. يُفحص النبض والجلد قبل وضعها، ويُفحص ما تحتها يومياً، ولا تُطوى أبداً، فالطيّة العلوية تشكّل عاصبة.
🚩
Watch out
تنبيه
Let alcohol-based skin preparation dry completely before draping and before diathermy is used. Wet preparation plus a spark plus oxygen is how surgical fires start.
يُترك تحضير الجلد الكحولي ليجفّ تماماً قبل التغطية وقبل استخدام الكيّ الكهربائي. فاجتماع التحضير المبلّل والشرارة والأكسجين هو ما تبدأ به الحرائق الجراحية.
7
8.6 · Anaesthesia and Malignant Hyperthermia٨٫٦ · التخدير وفرط الحرارة الخبيث
General anaesthesia produces unconsciousness with loss of protective reflexes, so airway management is the anaesthetist's central task and the nurse's central concern in recovery. Regional techniques block a region while the patient remains awake. Local anaesthesia numbs a small area. Sedation reduces awareness on a spectrum, and a patient can slip deeper than intended, so monitoring is required.
التخدير العامّ يُنتج فقد وعي مع فقد المنعكسات الواقية، فتدبير المجرى الهوائي هو المهمّة المركزية لطبيب التخدير والشاغل المركزي للممرضة في الإفاقة. والتقنيات الناحية تحصر منطقة والمريض مستيقظ. والتخدير الموضعي يخدّر منطقة صغيرة. والتهدئة تقلّل الوعي على طيف، وقد ينزلق المريض أعمق ممّا يُقصَد، فتلزم المراقبة.
Spinal and epidural anaesthesia block the SYMPATHETIC nerves along with the sensory and motor ones — and that is why the complication monitored most closely is HYPOTENSION.
والتخدير الشوكي وفوق الجافية يحصران الأعصاب الودّية مع الحسّية والحركية — ولهذا فالمضاعفة الأشدّ مراقبةً هبوط الضغط.
1
Sympathetic block → VASODILATATION
The vessels below the block relax.
حصر ودّي ← توسّع وعائي — تسترخي الأوعية الواقعة تحت مستوى الحصر.
2
→ Venous return falls
And with it the cardiac output.
← يهبط العود الوريدي ومعه النتاج القلبي.
3
→ HYPOTENSION, and often BRADYCARDIA
If the block is high enough to reach the cardiac sympathetic fibres.
← هبوط ضغط وبطء قلب غالباً — إذا كان الحصر عالياً بما يكفي ليصل إلى الألياف الودّية القلبية.
4
So monitor blood pressure FREQUENTLY
And treat with fluid, position and vasopressor as prescribed — anticipated, not reacted to.
فيُراقَب الضغط بتواتر — ويُعالَج بالسوائل والوضعية والمقبّض الوعائي حسب الوصفة، توقّعاً لا ردّ فعل.
5
And watch for a RISING block
Numbness or tingling in the hands, difficulty breathing or speaking, nausea — which mean the block is climbing, and it is an emergency.
ومراقبة الحصر الصاعد — خدر أو تنميل في اليدين، وصعوبة في التنفّس أو الكلام، وغثيان — وهذا يعني أن الحصر يرتفع، وهي حالة طارئة.
Malignant hyperthermia is a rare inherited reaction to certain anaesthetic agents — the volatile inhaled agents and suxamethonium — in which calcium is released uncontrollably in muscle, producing a hypermetabolic crisis. Its earliest and most sensitive sign is a rapidly rising end-tidal carbon dioxide that does not respond to increased ventilation, together with unexplained tachycardia and muscle rigidity, classically of the jaw. The high temperature is a late sign, despite the name — waiting for it is waiting too long.
وفرط الحرارة الخبيث تفاعل موروث نادر مع عوامل تخدير معيّنة — العوامل الطيّارة المستنشقة والسكساميثونيوم — يتحرّر فيه الكالسيوم دون ضبط في العضل فيُنتج أزمة فرط استقلاب. وأبكر علامة وأكثرها حساسية ارتفاع سريع في ثاني أكسيد الكربون بنهاية الزفير لا يستجيب لزيادة التهوية، مع تسرّع نبض غير مفسَّر وصلابة عضلية تظهر كلاسيكياً في الفكّ. وارتفاع الحرارة علامة متأخّرة رغم الاسم — وانتظاره يعني الانتظار أكثر مما ينبغي.
Management is immediate and specific: stop the triggering agent, give 100% oxygen, and give dantrolene sodium, which is the specific antidote and which every theatre stocks. Alongside that, active cooling, treatment of the hyperkalaemia and arrhythmias, and monitoring for rhabdomyolysis with dark urine and acute kidney injury. Prevention is preoperative: a patient or relative who reports an unexplained severe reaction, high fever or death during anaesthesia must be reported before surgery, because the condition is inherited and the anaesthetic can be planned to avoid the triggers.
والتدبير فوري ومحدّد: يُوقَف العامل المُطلِق، ويُعطى أكسجين ١٠٠٪، ويُعطى دانترولين الصوديوم وهو الترياق النوعي وتخزّنه كلّ غرفة عمليات. وإلى جانب ذلك تبريد نشط وعلاج فرط البوتاسيوم واضطرابات النظم ومراقبة انحلال الربيدات ببول داكن وأذيّة كلوية حادّة. والوقاية قبل الجراحة: فالمريض أو القريب الذي يذكر تفاعلاً شديداً غير مفسَّر أو حمّى عالية أو وفاة أثناء التخدير يجب الإبلاغ عنه قبل الجراحة، فالحالة موروثة ويمكن تخطيط التخدير لتجنّب المُطلِقات.
🚩
Watch out
تنبيه
In malignant hyperthermia the earliest sign is a rapidly rising end-tidal carbon dioxide with tachycardia and jaw rigidity. The fever is late. Stop the trigger and give dantrolene.
في فرط الحرارة الخبيث أبكر علامة ارتفاع سريع في ثاني أكسيد الكربون بنهاية الزفير مع تسرّع نبض وصلابة فكّ. والحمّى متأخّرة. يُوقَف المُطلِق ويُعطى الدانترولين.
⭐
Key point
نقطة أساسية
Ask every preoperative patient about anaesthetic problems in the family, not just in himself. Malignant hyperthermia is inherited.
يُسأل كلّ مريض قبل الجراحة عن مشكلات التخدير في أسرته لا لديه فقط. ففرط الحرارة الخبيث موروث.
8
8.7 · Airway Risk, Reversal and Awareness٨٫٧ · خطر المجرى والعكس والوعي أثناء التخدير
Under general anaesthesia the protective reflexes are LOST, so gastric contents can be regurgitated and inhaled, causing a severe chemical pneumonitis. That single risk is the reason for preoperative fasting.
وتحت التخدير العامّ تُفقَد المنعكسات الواقية فمحتويات المعدة قد تُقلَس وتُستنشَق مسبّبةً التهاب رئة كيميائياً شديداً. وذلك الخطر وحده سبب الصيام قبل الجراحة.
•Where the stomach cannot be assumed emptyالحالات التي لا يمكن فيها افتراض أن المعدة فارغة
Emergency surgery, trauma, and labourPain, opioids and pregnancy all delay gastric emptying — so ‘he has not eaten since midday’ is not reassurance in these patients.الجراحة الطارئة والرضّ والمخاض — الألم والأفيونيات والحمل كلّها تؤخّر إفراغ المعدة؛ فعبارة «لم يأكل منذ الظهر» ليست مطمئنة لدى هؤلاء المرضى.
Obesity, diabetic gastroparesis and bowel obstructionAnd anyone with reflux.السمنة وخزل المعدة السكّري وانسداد الأمعاء، وكلّ من يعاني من الارتجاع.
Then a RAPID SEQUENCE INDUCTION is usedPre-oxygenation, a rapid-onset relaxant, no bag-mask ventilation, and CRICOID PRESSURE where local practice uses it — with suction ready and turned on before induction, which is the nursing contribution.فيُستخدَم الاستحثاث بالتسلسل السريع: أكسجة مسبقة، ومرخٍّ سريع البدء، ودون تهوية بالكمامة والبالون، وضغط على الغضروف الحلقي حيث تستعمله الممارسة المحلية — مع شفط جاهز ومُشغَّل قبل الاستحثاث، وهذه هي مساهمة التمريض.
Muscle relaxants are REVERSED at the end — with neostigmine given with an antimuscarinic, or sugammadex. If reversal is incomplete, RESIDUAL NEUROMUSCULAR BLOCKADE appears in recovery — and it is dangerous and easily mistaken for sedation.
ومرخيات العضلات تُعكَس في النهاية — بالنيوستيغمين مع مضادّ مسكاريني أو السوغاماديكس. وإن كان العكس ناقصاً ظهر حصار عصبي عضلي متبقٍّ في الإفاقة وهو خطر ويُخلَط بالتهدئة بسهولة.
Weak, jerky movementsand an inability to lift the head off the pillow for five secondsحركات ضعيفة متقطّعة وعجز عن رفع الرأس عن الوسادة خمس ثوانٍ
A weak gripand difficulty swallowing or speakingقبضة ضعيفة وصعوبة بلع أو كلام
Shallow breathingand distress in a patient who cannot signal itتنفّس سطحي وكرب لدى من لا يستطيع الإشارة إليه
The reason it is frightening as well as dangerous: he may be awake and aware while unable to move or breathe adequately. Escalate immediately, support ventilation, and do not sedate him — which is the instinctive and exactly wrong response.
وسبب كونه مخيفاً وخطراً: أنه قد يكون مستيقظاً واعياً وهو عاجز عن الحركة أو التنفّس كفايةً. يجب التصعيد فوراً ودعم التهوية، ولا يُهدَّأ المريض — فهذه هي الاستجابة الغريزية وهي خاطئة تماماً.
Accidental AWARENESS under general anaesthesia is rare but profoundly distressing. He may recall sounds, conversation, pressure, pain, or — worst of all — the sensation of being PARALYSED and unable to signal.
والوعي العَرَضي تحت التخدير العامّ نادر لكنه مكرب بعمق. فقد يتذكّر أصواتاً وحديثاً وضغطاً وألماً أو — الأسوأ — إحساس الشلل والعجز عن الإشارة.
1
BELIEVE him
The single most important response. A patient who describes it and is doubted is harmed a second time.
تصديق المريض — أهمّ استجابة منفردة؛ فالمريض الذي يصفها ثم يُشكَّك فيه يتضرّر مرة ثانية.
2
Listen, and record what he says in his own words
Including what he heard, which is often verifiable and is what establishes it.
الإصغاء وتسجيل ما يقوله المريض بكلماته الخاصة — بما فيه ما سمعه، وهو غالباً قابل للتحقّق وهو ما يثبت حدوث الوعي.
3
Do not minimise or explain it away
‘You were probably dreaming’ is the response that does the damage.
عدم التقليل من شأنه ولا تبريره — فعبارة «من المرجّح أنه كان حلماً» هي الاستجابة التي تُحدث الضرر.
4
Escalate to the anaesthetist promptly
And report it through the incident system, so it is investigated.
التصعيد إلى طبيب التخدير فوراً والإبلاغ عبر نظام الحوادث ليجري التحقيق فيه.
5
And offer psychological follow-up
Post-traumatic stress is a recognised consequence — so this is a referral, not a reassurance.
وعرض متابعة نفسية — فالكرب التالي للصدمة عاقبة معروفة، ولذا فهي إحالة لا مجرّد طمأنة.
And the point that belongs to everyone in the theatre: the patient may be able to hear. Conversation about him, about the list, or about anything else is heard — which is a reason for how the room is run, not only a risk to be documented afterwards.
والنقطة التي تخصّ كلّ من في الغرفة: أن المريض قد يستطيع السماع. فالحديث عنه أو عن القائمة أو عن أيّ شيء آخر يُسمَع — وهذا سبب لطريقة إدارة الغرفة، لا مجرّد خطر يُوثَّق بعد ذلك.
🚩
Watch out
تنبيه
A patient in recovery who cannot lift his head off the pillow, has a weak grip and is breathing shallowly may have residual neuromuscular blockade, not simply sedation. Support ventilation and call the anaesthetist.
المريض في الإفاقة الذي لا يستطيع رفع رأسه عن الوسادة وقبضته ضعيفة وتنفّسه سطحي قد يكون لديه حصار عصبي عضلي متبقٍّ لا مجرّد تهدئة. تُدعم التهوية ويُستدعى طبيب التخدير.
⭐
Key point
نقطة أساسية
If a patient says he was aware during the operation, believe him and report it. Being disbelieved by the first person he tells markedly worsens the psychological harm.
إن قال مريض إنه كان واعياً أثناء العملية فيجب تصديقه والإبلاغ عن ذلك. فعدم تصديق أول من يخبره يزيد الضرر النفسي بوضوح.
9
8.8 · Recovery and the Immediate Postoperative Period٨٫٨ · الإفاقة والفترة التالية للجراحة مباشرةً
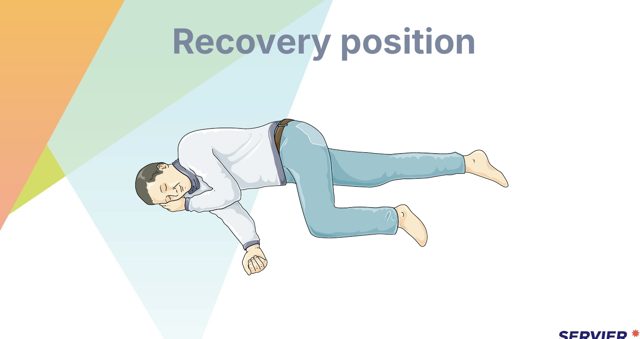
Recovery (lateral) position: lying on the side with the upper hand under the cheek and the upper leg bent at the hip and kneeوضعية الإفاقة (الوضعية الجانبية): الاستلقاء على الجانب مع وضع اليد العليا تحت الخدّ وثني الساق العليا عند الورك والركبةServier Medical Art · CC BY 4.0
On arrival in recovery the priority is always the same and it is the answer to a great many questions: airway and breathing first. Confirm a patent airway, assess the rate, depth and effort of respiration, the oxygen saturation and the colour, then move to circulation — pulse, blood pressure, perfusion, bleeding — then conscious level, pain, temperature, wound and drains, and fluid balance.
عند الوصول للإفاقة تكون الأولوية دائماً واحدة وهي جواب أسئلة كثيرة جداً: المجرى والتنفّس أولاً. يُتأكَّد من سالكية المجرى، ويُقيَّم معدّل التنفّس وعمقه وجهده والتشبّع واللون، ثم يُنتقَل إلى الدوران — النبض والضغط والتروية والنزف — ثم مستوى الوعي والألم والحرارة والجرح والمنازح وميزان السوائل.
An unconscious patient whose gag reflex has not returned is positioned on his side, or supine with the head turned to the side, so that secretions and any vomit drain out rather than being aspirated. A patient who is difficult to rouse with shallow breathing and a falling saturation is managed by opening the airway, stimulating him and supporting ventilation with oxygen — the residual anaesthetic and opioid are depressing respiration, and the response is to support breathing immediately rather than to observe.
والمريض فاقد الوعي الذي لم يعد إليه منعكس التهوّع يُوضَع على جانبه أو على ظهره والرأس مُدار للجانب، لتُصرَّف الإفرازات وأيّ قيء إلى الخارج بدلاً من أن تُستنشَق إلى الرئتين. والمريض الذي يصعب إيقاظه بتنفّس سطحي وتشبّع هابط يُدبَّر بفتح المجرى وتنبيهه ودعم التهوية بالأكسجين — فالتخدير والأفيوني المتبقّيان يثبّطان التنفّس، والاستجابة دعم التنفّس فوراً لا المراقبة.
Postoperative haemorrhage is recognised by the pattern already met in Chapter 01: restlessness, a rising pulse, a falling blood pressure, cool clammy skin, pallor and thirst, with the wound, drains and the area beneath the patient checked, because blood tracks backwards. Restlessness is an early sign of hypovolaemia and not agitation to be sedated. Shivering with a low temperature is common and is treated with warmed blankets and active warming while the temperature is monitored, since shivering greatly increases oxygen demand.
والنزف بعد الجراحة يُميَّز بالنمط الذي سبقت مصادفته في الفصل الأول: تململ وارتفاع نبض وهبوط ضغط وجلد بارد رطب وشحوب وعطش، مع فحص الجرح والمنازح والمنطقة تحت المريض فالدم يتسرّب للخلف. والتململ علامة مبكّرة لنقص الحجم لا هياج يُهدَّأ. والقشعريرة مع حرارة منخفضة شائعة وتُعالَج بأغطية مدفّأة وتدفئة فاعلة مع مراقبة الحرارة، فالقشعريرة تزيد الطلب على الأكسجين بشدّة.
A patient is discharged from recovery on defined criteria rather than by the clock — a stable and patent airway, adequate breathing and oxygenation, stable observations, a returning conscious level, controlled pain and nausea, no active bleeding, and adequate movement returning after regional anaesthesia. Scoring systems such as the Aldrete score formalise this.
ويُخرَج المريض من الإفاقة بمعايير محدّدة لا بالساعة — مجرى سالك مستقرّ وتنفّس وأكسجة كافيان وقياسات مستقرّة ووعي عائد وألم وغثيان مضبوطان ولا نزف نشط وحركة كافية عائدة بعد التخدير الناحي. وأنظمة التسجيل كمقياس ألدريت تُرسّم ذلك.
🔑
Memory aid
مفتاح للحفظ
In recovery the first assessment is always airway and breathing. Everything else follows it.
في الإفاقة يكون التقييم الأول دائماً المجرى والتنفّس. وكلّ ما عداه يتبعه.
🚩
Watch out
تنبيه
Restlessness in a postoperative patient is hypovolaemia until proved otherwise. Check the wound, the drains and underneath him before assuming it is pain or anxiety.
التململ لدى مريض بعد الجراحة نقص حجم حتى يثبت العكس. يُفحص الجرح والمنازح وما تحته قبل افتراض أنه ألم أو قلق.
10
8.9 · Postoperative Complications٨٫٩ · مضاعفات ما بعد الجراحة
Respiratory: atelectasis is the commonest early complication, typically in the first day or two, from shallow breathing and retained secretions, and it progresses to pneumonia. It is prevented by deep breathing, incentive spirometry, coughing with the wound splinted, adequate analgesia so the patient can do all of that, and getting him upright and moving.
التنفّسي: الانخماص أشيع مضاعفة مبكّرة، في اليوم الأول أو الثاني عادةً، من تنفّس سطحي واحتباس إفرازات، ويتطوّر إلى التهاب رئوي. ويُمنَع بالتنفّس العميق ومقياس التنفّس التحفيزي والسعال مع إسناد الجرح ومسكّن كافٍ ليستطيع المريض فعل ذلك كلّه وإنهاضه وتحريكه.
Circulatory: deep vein thrombosis and pulmonary embolism, prevented by mechanical and pharmacological prophylaxis, leg exercises and early mobilisation. Gastrointestinal and urinary: paralytic ileus, with absent bowel sounds, distension and no flatus as Chapter 05 describes, and urinary retention, which is assessed with a bladder scan before catheterising.
والدوراني: الخثار الوريدي العميق والانصمام الرئوي، ويُمنَعان بوقاية ميكانيكية ودوائية وتمارين ساقين وتحريك مبكّر. والهضمي والبولي: العلوص الشللي بغياب أصوات الأمعاء وانتفاخ ولا ريح كما يصف الفصل الخامس، والاحتباس البولي ويُقيَّم بماسح المثانة قبل القسطرة.
The one intervention that addresses several of these at once is early ambulation: it improves ventilation and reduces atelectasis, promotes venous return and reduces thrombosis, and stimulates peristalsis and reduces ileus. When a question asks for the single measure that prevents the most complications, this is usually it.
والتدخّل الواحد الذي يعالج عدّة من هذه في آن هو التحريك المبكّر: فهو يحسّن التهوية ويقلّل الانخماص، ويعزّز العود الوريدي ويقلّل الخثار، ويحفّز التمعّج ويقلّل العلوص. وحين يسأل سؤال عن التدبير الواحد الذي يمنع أكثر المضاعفات فهذا هو عادةً.
Day 5–7surgical site infection — fever, increasing pain, redness, warmth, swelling, purulent drainageاليوم ٥ إلى ٧ — عدوى موضع الجراحة: حمّى وألم متزايد واحمرار ودفء وتورّم وإفراز قيحي
Day 5–10dehiscence — and often preceded by a sudden gush of serosanguinous fluidاليوم ٥ إلى ١٠ — تفزّر الجرح، وكثيراً ما يسبقه خروج دفقة مفاجئة من سائل مصلي مدمّى
Any timeevisceration — protrusion of viscera through the woundفي أيّ وقت — بروز الأحشاء من الجرح
•Dehiscence and evisceration — what to do, in orderتفزّر الجرح وبروز الأحشاء — ما يُفعَل، بالترتيب
The warning sign that precedes itA sudden gush of serosanguinous (pink, watery) fluid from the wound — which is reported, not just re-dressed. It frequently precedes dehiscence by a day.العلامة المنذرة — دفقة مفاجئة من سائل مصلي مدمّى (وردي مائي) من الجرح — يُبلَّغ عنها ولا يُكتفى بتبديل الضماد. وهي كثيراً ما تسبق التفزّر بيوم.
If the wound opens — stay with himPosition him in low Fowler's with the knees bent to reduce tension on the wound.إن انفتح الجرح يُلازَم المريض — ويوضَع في وضعية فاولر المنخفضة مع ثني الركبتين لتخفيف الشدّ على الجرح.
Cover with STERILE saline-soaked gauzeDo NOT attempt to push anything back in, and do not use dry gauze, which adheres to bowel.يُغطّى بشاش معقّم مبلّل بالمحلول الملحي — ولا تُحاوَل إعادة أيّ شيء إلى الداخل، ولا يُستعمل شاش جافّ لأنه يلتصق بالأمعاء.
Then: nil by mouth, observations, escalate urgentlyPrepare for theatre, and stay with him — it is terrifying to look at, and he is watching your face.ثم الصيام وقياسات حيوية وتصعيد عاجل، مع التحضير لغرفة العمليات — ويُلازَم المريض، فمنظر الحالة مرعب والمريض يراقب وجه الممرضة.
⭐
Key point
نقطة أساسية
Early ambulation prevents atelectasis, venous thrombosis and ileus simultaneously. It is usually the answer to which single measure prevents the most complications.
التحريك المبكّر يمنع الانخماص والخثار الوريدي والعلوص في آن. وهو عادةً جواب سؤال أيّ تدبير منفرد يمنع أكثر المضاعفات.
🚩
Watch out
تنبيه
For evisceration: sterile saline-moistened gauze, low Fowler's with knees flexed, nil by mouth, notify immediately. Never push the bowel back in and never let the gauze dry.
لبروز الأحشاء: شاش معقّم مبلّل بمحلول ملحي، وفاولر منخفضة والركبتان مثنيّتان، وصيام، وإبلاغ فوري. ولا تُدفَع الأمعاء إلى الداخل أبداً ولا يُترك الشاش يجفّ أبداً.
11
8.10 · Nausea, Catheters and Wounds That Need More٨٫١٠ · الغثيان والقثاطر والجروح التي تحتاج إلى المزيد
Postoperative nausea and vomiting is one of the outcomes patients say they fear MOST — sometimes more than pain — and it is largely PREDICTABLE.
والغثيان والتقيّؤ بعد الجراحة من أكثر ما يقول المرضى إنهم يخافونه — أحياناً أكثر من الألم — وهو قابل للتنبّؤ به إلى حدّ بعيد.
1
FEMALE sex
The strongest single risk factor.
الجنس الأنثوي — أقوى عامل خطر منفرد.
2
NON-smoker
Counter-intuitive, and consistent.
غير مدخّن — مخالف للحدس ومتّسق.
3
Previous PONV or motion sickness
So ask — it is the question that identifies the high-risk patient.
غثيان سابق بعد جراحة أو دوار حركة — لذا يُسأل عن ذلك، فهو السؤال الذي يحدّد المريض عالي الخطر.
4
And POSTOPERATIVE OPIOID use
Which is the one that can be modified.
واستخدام الأفيونيات بعد الجراحة — وهو القابل للتعديل.
5
So the response is PROPHYLAXIS, not rescue
Antiemetics from more than one class given before he is sick, opioid-sparing analgesia, and avoiding dehydration — because once he is vomiting it is much harder to control.
فالاستجابة وقاية لا إنقاذ — مضادات تقيّؤ من أكثر من صنف قبل أن يتقيّأ المريض، وتسكين موفّر للأفيونيات، وتجنُّب الجفاف — لأن السيطرة على التقيّؤ بعد بدئه أصعب بكثير.
The urinary catheter inserted for an operation should come out AS SOON AS it is no longer needed, and early removal is the single most effective measure against catheter-associated urinary infection — more effective than anything done while it is in.
والقسطرة البولية المُدخَلة لعملية ينبغي أن تُزال بمجرّد انتفاء الحاجة إليها والإزالة المبكّرة هي أكثر إجراء فعالية ضدّ عدوى الجهاز البولي المرتبطة بالقسطرة — وهي أكثر فعالية من أيّ إجراء يُتّخذ أثناء وجودها.
•So the question is asked DAILY — does he still need it?لذا يُطرح السؤال يومياً — هل ما زال المريض بحاجة إليه؟
‘It is easier for measuring output’ is not an indicationOnce he is stable and can pass urine — and convenience is the commonest reason a catheter stays in.«أسهل لقياس الإخراج» ليس استطباباً متى استقرّ المريض وصار قادراً على التبوّل — والراحة أشيع سبب لبقاء القسطرة.
And a catheter is a reason not to walkWhich connects it to chest infection, thromboembolism, weakness and delirium — so it is not only an infection question.والقسطرة سبب لعدم المشي — وهذا يربطها بعدوى الصدر والانصمام الخثاري والضعف والهذيان، فهي ليست مسألة عدوى فقط.
Plus watch for retention after removalEspecially after spinal or epidural anaesthesia, opioids, or pelvic surgery — a patient who has not passed urine within the expected interval is assessed and scanned, not waited on.ومراقبة الاحتباس بعد الإزالة — خاصّةً بعد التخدير الشوكي أو فوق الجافية أو الأفيونيات أو جراحة الحوض؛ فالمريض الذي لم يتبوّل ضمن الفاصل المتوقَّع يُقيَّم ويُفحَص بالماسح ولا يُنتظَر.
🌪️NEGATIVE PRESSURE wound therapy
Applies controlled suction through a SEALED dressing
Draws out exudate, reduces oedema, and promotes granulation
The nursing: maintain the SEAL — a leaking dressing does nothing
Monitor the volume and character of what comes out
And report FRESH BLOOD in the canister urgently — it can mean a vessel has eroded
علاج الجروح بالضغط السلبي — شفط مضبوط عبر ضمادة محكمة الإغلاق: يسحب النضح ويقلّل الوذمة ويعزّز التحبّب. والتمريض: يُحافَظ على الإحكام — فالضمادة المتسرّبة لا تفيد؛ ويُراقَب حجم ما يخرج وطبيعته؛ ويُبلَّغ عاجلاً عن الدم الطازج في الوعاء فقد يعني تآكل وعاء دموي.
🩹And the general wound principles
Assess and DOCUMENT: size, depth, tissue type, exudate, odour, and the surrounding skin
Moist wound healing — not dried out and not macerated
Protect the peri-wound skin, which is where dressings do their damage
Nutrition and protein, which determine whether it heals at all
And pain relief BEFORE a dressing change, not after
ومبادئ الجروح العامّة — التقييم والتوثيق (الحجم والعمق ونوع النسيج والنضح والرائحة والجلد المحيط)، والتئام رطب لا جافّ ولا مُنقَع، وحماية الجلد المحيط بالجرح حيث تُحدث الضمادات ضررها، والتغذية والبروتين اللذان يحدّدان هل سيلتئم الجرح أصلاً، وتسكين الألم قبل تبديل الضماد لا بعده.
🔑
Memory aid
مفتاح للحفظ
Risk factors for postoperative nausea: female sex, non-smoker, previous postoperative nausea or motion sickness, and expected opioid use. Prophylaxis is given before it starts.
عوامل خطر الغثيان بعد الجراحة: الجنس الأنثوي وعدم التدخين وغثيان سابق بعد جراحة أو دوار حركة والاستخدام المتوقّع للأفيونيات. وتُعطى الوقاية قبل البدء.
⭐
Key point
نقطة أساسية
Early removal of the urinary catheter is the single most effective measure against catheter-associated infection. Ask daily whether it is still needed.
النزع المبكّر للقسطرة البولية أكثر تدبير منفرد فعالية ضدّ العدوى المرتبطة بها. يُسأل يومياً هل ما زالت لازمة.
12
8.11 · Wounds, Drains and Later Complications٨٫١١ · الجروح والمنازح والمضاعفات المتأخّرة
1
PRIMARY intention
A clean wound with edges approximated by sutures, staples or glue — heals quickly with minimal scarring.
القصد الأولي — جرح نظيف تُقرَّب حوافّه بالخيوط أو الدبابيس أو الغراء: يلتئم بسرعة وبندب أدنى.
2
SECONDARY intention
The wound is left OPEN and heals from the base up by granulation — slower, with more scarring, used where there is infection or tissue loss.
القصد الثانوي — يُترَك الجرح مفتوحاً ويلتئم من القاعدة بالتحبّب — أبطأ وبندب أكبر، ويُستخدم حيث توجد عدوى أو فقد نسيجي.
3
TERTIARY — delayed primary
Left open deliberately for a period, then closed — used where contamination or oedema make immediate closure unsafe.
القصد الثالثي (الأولي المتأخّر) — يُترَك مفتوحاً عمداً مدّةً ثم يُغلَق، ويُستخدم حيث يجعل التلوّث أو الوذمة الإغلاق الفوري غير آمن.
4
And the phases run through all three
Haemostasis, inflammation, proliferation and maturation — with maturation continuing for months to years, which is worth telling a patient who thinks the scar is finished.
والمراحل تجري عبر الثلاثة — إرقاء والتهاب وتكاثر ونضج، ويستمرّ النضج أشهراً إلى سنوات — وهذا يستحقّ أن يُخبَر به المريض الذي يظنّ أن الندبة اكتملت.
💧PASSIVE drains
Penrose — open, draining by GRAVITY and capillary action into a dressing
No suction
Output is estimated from the dressing, which is imprecise
And the open system carries a higher infection risk
منازح منفعلة — بينروز: مفتوح ينزح بالجاذبية والخاصّية الشعرية إلى ضماد، بلا شفط؛ ويُقدَّر الإخراج من الضماد وهو غير دقيق؛ والنظام المفتوح يحمل خطر عدوى أعلى.
🔽ACTIVE / closed drains
Redivac / vacuum — a closed system under suction
Output measured accurately
Lower infection risk
And the vacuum must be CHECKED and recharged — a collapsed vacuum is a drain that has stopped working
Chest drains are a separate matter entirely and follow their own rules
منازح فاعلة مغلقة — ريديفاك (خلاء): نظام مغلق تحت شفط؛ يُقاس الإخراج بدقّة وخطر عدوى أقلّ؛ ويجب فحص الخلاء وإعادة شحنه — فالخلاء المنهار منزح توقّف عن العمل. أما المنازح الصدرية فمسألة منفصلة تماماً ولها قواعدها الخاصة.
The nursing for any drain: secure it so it cannot pull; measure and record output each shift and note a CHANGE in volume or character; keep the bag below the site; never irrigate or advance it without an instruction; and report a sudden increase, fresh blood, or a sudden STOP — because a drain that has stopped may be blocked rather than finished, and the fluid is still collecting.
والتمريض لأيّ منزح: يُثبَّت كي لا يُشدّ؛ ويُقاس الإخراج ويُسجَّل كلّ مناوبة ويُلاحَظ أيّ تغيّر في الحجم أو الطبيعة؛ ويُبقى الكيس أسفل موضع المنزح؛ ولا يُغسَل المنزح ولا يُدفَع إلى الداخل دون تعليمات؛ ويُبلَّغ عن زيادة مفاجئة أو دم طازج أو توقّف مفاجئ — فالمنزح المتوقّف قد يكون مسدوداً لا منتهياً، والسائل ما زال يتجمّع.
Sutures and staples are removed once the wound has sufficient strength, and the timing varies with the site: earlier on the face, where healing is rapid and cosmetic result matters, and later over joints, the back and areas under tension. If there is any concern about wound strength, alternate sutures are removed first and the rest a day or two later. Inspect the wound before and after, and report any separation, gaping, discharge or surrounding redness rather than proceeding.
والخيوط والدبابيس تُنزَع بعد اكتساب الجرح قوّة كافية، والتوقيت يتباين بالموقع: أبكر في الوجه حيث الالتئام سريع والنتيجة التجميلية تهمّ، وأكثر تأخّراً فوق المفاصل والظهر والمناطق تحت الشدّ. وإن وُجد أيّ قلق بشأن قوّة الجرح تُنزَع الخيوط بالتناوب أولاً والباقي بعد يوم أو يومين. ويُفحص الجرح قبل النزع وبعده، ويُبلَّغ عن أيّ انفصال أو تباعد أو نضح أو احمرار محيط بدلاً من المضيّ في الإجراء.
⚡Postoperative DELIRIUM
ACUTE, within hours to days
FLUCTUATES, and impairs attention
Usually reversible once the cause is treated
Look for pain, infection, retention, constipation, hypoxia, drugs
الهذيان بعد الجراحة — حادّ يبدأ خلال ساعات إلى أيام، ويتذبذب ويعطّل الانتباه، وهو عكوس عادةً متى عولج السبب؛ ويُبحَث عن الألم والعدوى والاحتباس والإمساك ونقص الأكسجة والأدوية.
🧠Postoperative COGNITIVE DYSFUNCTION
DISTINCT from delirium
A more PERSISTENT impairment of memory, concentration and processing
Lasting weeks to months
Commoner after major surgery and in older patients
And warning about it in advance is the intervention — a family who expects it copes; one who does not thinks something went wrong
الخلل المعرفي بعد الجراحة — متميّز عن الهذيان؛ قصور أكثر استمراراً في الذاكرة والتركيز والمعالجة الذهنية، يدوم أسابيع إلى أشهر، وهو أشيع بعد الجراحة الكبرى ولدى المسنّين؛ والتحذير منه مسبقاً هو التدخّل — فالأسرة التي تتوقّعه تتأقلم معه، والتي لا تتوقّعه تظنّ أن خطأً قد حدث.
The second later complication worth naming: chronic post-surgical pain — persistent pain at the surgical site months after healing, commoner after certain operations and after severe uncontrolled acute pain. Which gives postoperative analgesia a second purpose: controlling the acute pain well reduces the chance of the chronic pain, so it is not only about comfort this week.
والمضاعفة المتأخّرة الثانية الجديرة بالتسمية: الألم المزمن بعد الجراحة — ألم مستمرّ في موضع الجراحة بعد أشهر من الالتئام، وهو أشيع بعد عمليات معيّنة وبعد الألم الحادّ الشديد غير المضبوط. وهذا يعطي التسكين بعد الجراحة غرضاً ثانياً: أن ضبط الألم الحادّ جيّداً يقلّل احتمال الألم المزمن، فلا يتعلّق الأمر بالراحة في هذا الأسبوع فقط.
🚩
Watch out
تنبيه
A vacuum drain must be recompressed after emptying, or the suction is lost and it stops draining. It is a common and easily missed error.
المنزح الخلائي يجب إعادة ضغطه بعد إفراغه وإلا فُقد الشفط وتوقّف عن التصريف. وهو خطأ شائع سهل الإغفال.
⭐
Key point
نقطة أساسية
In venous air embolism, position the patient on the left side with the head down and give 100% oxygen, so air is trapped in the right ventricle.
في الانصمام الهوائي الوريدي يوضع المريض على جانبه الأيسر ورأسه إلى الأسفل ويُعطى أكسجين ١٠٠٪، ليُحتبَس الهواء في البطين الأيمن.
13
8.12 · Day Surgery, Analgesia and Surgical Risk٨٫١٢ · جراحة اليوم الواحد والتسكين والخطر الجراحي
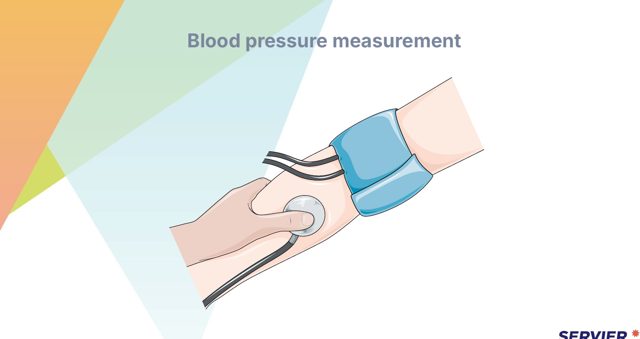
Auscultatory blood pressure measurement: the cuff wrapped around the bare upper arm and the stethoscope diaphragm placed over the brachial artery at the elbow crease, just below the cuffقياس ضغط الدم بالإصغاء: الكُفّة ملفوفة حول الذراع العارية، وقرص السمّاعة موضوع فوق الشريان العضدي عند ثنية المرفق أسفل الكُفّة مباشرةًServier Medical Art · CC BY 4.0
Day surgery discharges the patient the SAME DAY, and the discharge criteria are what PROTECT him.
وجراحة اليوم الواحد تُخرج المريض في اليوم نفسه ومعايير الخروج ما يحميه.
1
Stable observations, fully orientated
Back to his own baseline.
قياسات مستقرّة ومتوجّه تماماً — وعائد إلى حالته الأساسية.
2
Tolerating oral fluids, and pain controlled ORALLY
On what he will actually have at home.
يتحمّل السوائل الفموية والألم مضبوط فموياً — بما سيتناوله فعلاً في المنزل.
3
Has PASSED URINE where required
Particularly after spinal anaesthesia or pelvic surgery.
تبوّل حيث يلزم — خاصّةً بعد التخدير الشوكي أو جراحة الحوض.
4
Minimal bleeding, and the wound checked
And any dressing intact.
نزف أدنى والجرح مفحوص — وأيّ ضماد سليم.
5
A RESPONSIBLE ADULT to take him home and stay
For the first 24 hours — which is a criterion, not a preference.
بالغ مسؤول يأخذه للمنزل ويبقى — أول ٢٤ ساعة: معيار لا تفضيل.
6
And written instructions with a number that is answered
Plus the warning: no driving, no operating machinery, no important decisions or legal documents for the specified period — because residual anaesthetic impairs judgement he does not notice is impaired.
وتعليمات مكتوبة برقم هاتف يُردّ عليه — مع التحذير: لا قيادة ولا تشغيل آلات ولا قرارات مهمّة ولا وثائق قانونية طوال المدة المحدّدة — لأن بقايا التخدير تُضعف الحكم بدرجة لا يلاحظها المريض.
A laparoscopic approach uses small incisions and a camera, giving less pain, shorter stay and faster recovery than open surgery, though a procedure may be converted to open if difficulty arises — patients should be warned of that possibility beforehand so it is not experienced as a failure. The carbon dioxide used to inflate the abdomen causes referred shoulder-tip pain, as Chapter 05 sets out, which is expected and eases with walking.
والنهج التنظيري يستخدم شقوقاً صغيرة وكاميرا فيعطي ألماً أقلّ وإقامة أقصر وتعافياً أسرع من الجراحة المفتوحة، وإن كان الإجراء قد يُحوَّل لمفتوح إن نشأت صعوبة — وينبغي تحذير المرضى من ذلك الاحتمال مسبقاً كي لا يُعاش كإخفاق. وثاني أكسيد الكربون المستخدم لنفخ البطن يسبّب ألم طرف الكتف المُحال كما يبيّن الفصل الخامس، وهو متوقّع ويخفّ بالمشي.
Patient-controlled analgesia lets the patient press a button to deliver a set dose, with a LOCKOUT interval preventing another dose too soon.
والتسكين المتحكَّم به من المريض يتيح له ضغط زرّ لإيصال جرعة محدّدة بفترة إقفال تمنع جرعةً أخرى مبكّراً.
•Its safety rests on ONE principle — and one rule that followsتقوم سلامته على مبدأ واحد — وقاعدة واحدة تترتّب عليه
ONLY THE PATIENT presses the buttonNever a relative, and never a nurse.The principle is that a patient too sedated to press it is too sedated to need another dose — which is the built-in safety mechanism, and pressing it for him removes the only protection the system has.المريض وحده يضغط الزرّ — لا قريب ولا ممرضة أبداً. والمبدأ أن المريض الذي بلغ من التهدئة حدّاً يعجزه عن الضغط على الزرّ لا يحتاج إلى جرعة أخرى — وهذه آلية السلامة المدمجة، والضغط عنه يُزيل الحماية الوحيدة التي يملكها النظام.
So teach him BEFORE the operationHow it works, that he cannot overdose himself, and that he should press it BEFORE the pain is severe — because a patient who is afraid of it will not use it and will be in pain.فيُعلَّم المريض قبل العملية كيف يعمل الجهاز، وأنه لا يستطيع إعطاء نفسه جرعة زائدة، وأن عليه الضغط على الزرّ قبل أن يشتدّ الألم — لأن المريض الذي يخاف منه لن يستعمله وسيبقى متألّماً.
And monitor for the opioid effectsSedation score, respiratory rate, oxygen saturation and pain score — with naloxone available, and the sedation score as the earliest warning, before the respiratory rate falls.ومراقبة آثار الأفيونيات — درجة التهدئة ومعدّل التنفّس وتشبّع الأكسجين ودرجة الألم، مع توافر النالوكسون، وتكون درجة التهدئة أبكر تحذير، قبل أن ينخفض معدّل التنفّس.
1
CLEAN
No hollow viscus entered — lowest infection risk.
نظيف — لم يجرِ الدخول إلى عضو مجوّف: أدنى خطر عدوى.
2
CLEAN-CONTAMINATED
A hollow viscus entered under controlled conditions, with no significant spillage.
نظيف ملوَّث — جرى الدخول إلى عضو مجوّف بظروف مضبوطة بلا انسكاب معتبر.
3
CONTAMINATED
Significant spillage, an open fresh trauma wound, or a major break in sterile technique.
ملوَّث — انسكاب معتبر أو جرح رضّي مفتوح حديث أو خرق كبير في التقنية المعقّمة.
4
DIRTY / INFECTED
Existing infection or perforated viscus — highest risk, and the wound is often left open to heal by secondary intention.
قذر أو مُصاب بعدوى — عدوى قائمة أو عضو مثقوب: أعلى خطر، وكثيراً ما يُترك الجرح مفتوحاً ليلتئم بالقصد الثانوي.
5
And the risk rises ACROSS the categories
Which is why the classification determines antibiotic prophylaxis, closure technique and how closely the wound is watched.
والخطر يرتفع عبر الفئات — ولهذا يحدّد التصنيف الوقاية بالمضادّات الحيوية وتقنية الإغلاق ومدى مراقبة الجرح عن كثب.
🚩
Watch out
تنبيه
Only the patient presses the analgesia button. If a relative or a nurse presses it for him, the safety mechanism of his own sedation is removed and he can be overdosed.
المريض وحده يضغط زرّ المسكّن. فإن ضغطه قريب أو ممرضة عنه زالت آلية السلامة المتمثّلة في نعاسه هو وقد يتعرّض لجرعة زائدة.
⭐
Key point
نقطة أساسية
Day surgery discharge needs a responsible adult to escort and stay, and written instructions. No driving, machinery, alcohol or legal documents for about 24 hours.
خروج جراحة اليوم الواحد يحتاج بالغاً مسؤولاً يرافق ويبقى وتعليمات مكتوبة. ولا قيادة ولا آلات ولا كحول ولا وثائق قانونية نحو ٢٤ ساعة.
14
8.13 · Epidural Analgesia and the Danger of a Spinal Haematoma٨٫١٣ · التسكين فوق الجافية وخطر الورم الدموي الشوكي
An epidural gives excellent analgesia after major surgery, and its nursing care has a specific list: monitor the level of the block, motor power in the legs, blood pressure, respiratory rate, sedation score and pain score at the intervals specified; inspect the insertion site for leakage, redness or tenderness; ensure the catheter and all connections are clearly labelled and secured; and never inject anything into an epidural line. Watch for urinary retention, and for hypotension from sympathetic blockade as described in the anaesthesia section.
وفوق الجافية يعطي تسكيناً ممتازاً بعد الجراحة الكبرى ورعايته التمريضية لها قائمة محدّدة: يُراقَب مستوى الحصار والقوّة الحركية في الساقين وضغط الدم ومعدّل التنفّس ودرجة التهدئة ودرجة الألم بالفواصل المحدّدة؛ ويُفحص موقع الإدخال بحثاً عن تسرّب أو احمرار أو إيلام؛ ويُتأكَّد من وسم القسطرة وكلّ الوصلات بوضوح وتثبيتها؛ ولا يُحقَن أيّ شيء في خطّ فوق الجافية أبداً. ويُراقَب الاحتباس البولي وهبوط الضغط الناجم عن الحصار الودّي كما وُصف في قسم التخدير.
The complication that must NEVER be missed is a SPINAL or EPIDURAL HAEMATOMA, which compresses the spinal cord and causes PERMANENT PARALYSIS if it is not decompressed within HOURS.
والمضاعفة التي يجب ألّا تُغفَل أبداً ورم دموي شوكي أو فوق الجافية يضغط النخاع ويسبّب شللاً دائماً إن لم يُزَل الضغط خلال ساعات.
🚨The warning signs
Severe or increasing BACK PAIN
New or WORSENING leg weakness
A block that is DENSER or HIGHER than expected
Numbness that is spreading
Bladder or bowel dysfunction
العلامات المنذرة — ألم ظهر شديد أو متزايد، وضعف ساق جديد أو متفاقم، وحصار أكثف أو أعلى ممّا هو متوقَّع، وخدر منتشر، وخلل في وظيفة المثانة أو الأمعاء.
⚠️And why they are missed
They are easily mistaken for the block itself
‘His legs are heavy — that is the epidural’
So the rule is about DIRECTION, not presence
A block that is WEARING OFF and then comes BACK is a haematoma until proved otherwise
Escalate IMMEDIATELY — hours decide whether he walks
ولماذا تُغفَل — تُخلَط بسهولة بالحصار نفسه: «ساقاه ثقيلتان — هذا بسبب فوق الجافية». فالقاعدة تتعلّق بالاتّجاه لا بالوجود: الحصار الذي يزول ثم يعود يُعدّ ورماً دموياً حتى يثبت العكس. ويُصعَّد الأمر فوراً — فالساعات تحدّد هل سيمشي المريض.
Which makes REGULAR, DOCUMENTED motor and sensory assessment the core nursing task of epidural care — not the pump, not the dressing. Recorded each time, so the trend is visible, because a single observation cannot show a block that is deepening.
ما يجعل التقييم الحركي والحسّي المنتظم الموثَّق المهمّة التمريضية الجوهرية لرعاية فوق الجافية — لا المضخّة ولا الضمادة. ويُسجَّل التقييم في كل مرة ليظهر الاتجاه العام، لأن ملاحظة واحدة لا تكشف حصاراً يزداد عمقاً.
•Anticoagulants and neuraxial blocks — one of the most important safety rules in perioperative nursingمضادّات التخثّر والحصار المحوري العصبي — من أهمّ قواعد السلامة في تمريض ما حول الجراحة
A DEFINED TIME INTERVAL is requiredBetween the last dose of an anticoagulant and inserting OR REMOVING the catheter — and REMOVAL is as dangerous as insertion, which is the half people forget.يلزم فاصل زمني محدّد بين آخر جرعة من مضادّ التخثّر وإدخال القسطرة أو إزالتها — والإزالة خطرة كالإدخال، وهذا هو النصف الذي ينساه الناس.
The interval differs by drugCheck it for THAT drug and THAT dose — prophylactic and treatment doses have different intervals, and they are not interchangeable.الفاصل يختلف بالدواء — يُفحص لذلك الدواء وتلك الجرعة بعينهما؛ فللجرعات الوقائية والعلاجية فواصل مختلفة، ولا يجوز تبادلها.
And the next dose is delayed after removalBy a defined interval too — so the timing is planned in both directions and written on the chart.والجرعة التالية تُؤخَّر بعد الإزالة — بفاصل محدّد أيضاً، فيُخطَّط التوقيت في الاتجاهين ويُكتب في السجل.
So the nursing action is simple and absoluteDo not remove an epidural catheter without checking the anticoagulant timing — and if you cannot establish it, do not remove it. It can wait an hour; a haematoma cannot.فالإجراء التمريضي بسيط وقطعي — لا تُنزَع قسطرة فوق الجافية دون فحص توقيت مضادّ التخثّر، وإن تعذّر تحديده فلا تُنزَع؛ فهي تستطيع الانتظار ساعة، أما الورم الدموي فلا.
🌉BRIDGING anticoagulation
Covering the gap in long-term anticoagulation with a short-acting heparin
NOT needed by most patients
And giving it unnecessarily CAUSES bleeding
The decision balances the individual thrombotic risk against the bleeding risk
A specialist decision, not a routine one
العلاج الجسري بمضادّات التخثّر — سدّ الفجوة في العلاج طويل الأمد بمضادّات التخثّر باستخدام هيبارين قصير المفعول: غير لازم لمعظم المرضى — وإعطاؤه دون داعٍ يسبّب النزف؛ والقرار يوازن بين خطر الخثار لدى المريض وخطر النزف؛ وهو قرار اختصاصي لا روتيني.
⚖️And which drugs to STOP or CONTINUE
Most long-term medication is CONTINUED through surgery
Stopping a beta-blocker or a steroid abruptly is more dangerous than continuing it
Diabetes medication and insulin follow a specific plan, not omission
And the list of what to stop, when, is drug-specific and written down
‘Nil by mouth’ does not mean ‘omit all medication’ — which is the error
وأيّ الأدوية تُوقَف أو تُواصَل — فمعظم الدواء طويل الأمد يُواصَل خلال الجراحة؛ والتوقّف المفاجئ عن حاصرات بيتا أو الستيرويد أخطر من متابعتهما؛ ودواء السكّري والإنسولين يتبعان خطة محدّدة لا الإهمال؛ وقائمة ما يُوقَف ومتى خاصّة بكل دواء ومكتوبة؛ و«الصيام» لا يعني «إهمال كل الدواء» — وهذا هو الخطأ.
🚩
Watch out
تنبيه
New or worsening back pain, new leg weakness, or a block that is not wearing off when it should may be a spinal haematoma. Escalate immediately — decompression within hours determines whether function returns.
ألم ظهر جديد أو متفاقم أو ضعف ساق جديد أو حصار لا يزول حين ينبغي قد يكون ورماً دموياً شوكياً. يجب التصعيد فوراً — فتخفيف الضغط خلال ساعات يحدّد هل تعود الوظيفة.
🚩
Watch out
تنبيه
An epidural catheter is never removed at the wrong point in the anticoagulant schedule. If the timing is unclear, the catheter stays in and you ask.
لا تُنزَع قسطرة فوق الجافية أبداً في النقطة الخاطئة من جدول مضادّ التخثّر. وإن كان التوقيت غير واضح تبقى القسطرة ويُستفسَر عن التوقيت.
⭐
Key point
نقطة أساسية
Never inject anything into an epidural line, and ensure the catheter and all connections are clearly labelled.
لا يُحقَن أيّ شيء في خطّ فوق الجافية أبداً، ويُتأكَّد من وسم القسطرة وكلّ الوصلات بوضوح.
15
8.14 · The Anaemias٨٫١٤ · فقر الدم بأنواعه
Whatever the cause, anaemia reduces oxygen delivery, and the shared features are fatigue, pallor, breathlessness on exertion, tachycardia, dizziness and headache, with a systolic flow murmur in severe cases. The cause is what determines the treatment, so classifying it matters.
مهما كان السبب فإن فقر الدم يقلّل توصيل الأكسجين، والسمات المشتركة تعب وشحوب وضيق نفس بالجهد وتسرّع نبض ودوخة وصداع، مع نفخة جريان انقباضية في الحالات الشديدة. والسبب هو ما يحدّد العلاج، فالتصنيف يهمّ.
Iron deficiency anaemia is the commonest — from blood loss (menstrual or gastrointestinal), poor intake or malabsorption. And the rule that matters: in an adult, and particularly in a MAN or a POST-MENOPAUSAL WOMAN, iron deficiency anaemia needs the CAUSE investigated, because it is gastrointestinal blood loss until proved otherwise.
وفقر دم نقص الحديد الأشيع — من فقد دم (طمثي أو هضمي) أو قلّة المتناول الغذائي أو سوء امتصاص. والقاعدة المهمّة: يجب تقصّي السبب لدى البالغ، ولا سيّما الرجل أو المرأة بعد سنّ اليأس، لأن فقر دم نقص الحديد يُعدّفقداً للدم عبر الجهاز الهضمي حتى يثبت خلاف ذلك.
1
Take it with VITAMIN C
Orange juice or a supplement — which substantially improves absorption.
يُتناول مع فيتامين ج (عصير البرتقال أو مكمّل) — ما يحسّن الامتصاص بدرجة كبيرة.
2
AWAY from tea, coffee, milk, calcium and antacids
All of which BIND it — and tea with tablets is a common reason iron does not work.
بعيداً عن الشاي والقهوة والحليب والكالسيوم ومضادّات الحموضة — فكلّها تربطه، والشاي مع الأقراص سبب شائع لعدم فعالية الحديد.
3
Warn about BLACK STOOLS and constipation
Because these are why people stop — and the black stool frightens them into thinking they are bleeding.
التحذير من البراز الأسود والإمساك — فهما سبب توقّف الناس عن الدواء، والبراز الأسود يخيفهم فيظنّون أنهم ينزفون.
4
And explain how LONG
Continued for months AFTER the haemoglobin normalises, to refill the stores — which is the instruction most often not given, and why it recurs.
وشرح مدّة العلاج — تُواصَل أشهراً بعد عودة الهيموغلوبين لطبيعته لإعادة ملء المخازن — وهذا هو التوجيه الأكثر إغفالاً ولهذا يعود فقر الدم.
Vitamin B12 deficiency most often arises as PERNICIOUS ANAEMIA — an autoimmune loss of INTRINSIC FACTOR from the stomach, without which B12 cannot be absorbed.
ونقص فيتامين ب١٢ ينشأ غالباً كفقر دم وبيل — فقد مناعي ذاتي للعامل الداخلي من المعدة الذي بدونه لا يُمتصّ ب١٢.
🧠B12 deficiency
Macrocytic anaemia
PLUS NEUROLOGICAL features — paraesthesia, numbness, unsteady gait, cognitive change
The neurological damage can be IRREVERSIBLE if treatment is delayed
Treated by INJECTION, lifelong, because the absorption problem does not go away
Standard-dose oral B12 is unreliable in pernicious anaemia
نقص ب١٢ — فقر دم كبير الكريّات مع علامات عصبية (تنميل وخدر واختلال في المشية وتغيّر معرفي)، وقد يكون الضرر العصبي غير عكوس إن تأخّر العلاج؛ ويُعالَج بالحقن مدى الحياة لأن مشكلة الامتصاص لا تزول؛ وفيتامين ب١٢ الفموي بالجرعة المعتادة غير موثوق في فقر الدم الوبيل.
🥬FOLATE deficiency
Also macrocytic
But NO neurological features
From poor intake, pregnancy, malabsorption, or drugs
And the trap: giving FOLATE to someone who is actually B12 deficient
Corrects the anaemia and lets the NEUROLOGICAL damage progress unnoticed — which is why B12 is checked and corrected FIRST
نقص الفولات — كبير الكريّات أيضاً لكن بلا علامات عصبية؛ وينجم عن قلّة المتناول أو الحمل أو سوء الامتصاص أو الأدوية. والفخّ: إعطاء الفولات لمن يعاني فعلاً من نقص ب١٢ يصحّح فقر الدم ويدع الضرر العصبي يتقدّم دون أن يُلاحَظ — ولهذا يُفحص ب١٢ ويُصحَّح أولاً.
Aplastic anaemia is failure of the bone marrow producing pancytopenia — a fall in all three cell lines at once — so the patient has anaemia, infection risk from neutropenia and bleeding risk from thrombocytopenia together. The nursing priorities follow directly: protect from infection and apply bleeding precautions. Haemolytic anaemia is premature destruction of red cells, giving anaemia with jaundice, dark urine and splenomegaly and a raised reticulocyte count. Anaemia of chronic disease accompanies chronic inflammation, infection, malignancy and kidney disease, and it improves by treating the underlying condition.
وفقر الدم اللاتنسّجي فشل نقي العظم يُنتج قلّة الخلايا الشاملة — أي هبوط الخطوط الثلاثة معاً — فيكون لدى المريض فقر دم وخطر عدوى من قلّة العدلات وخطر نزف من قلّة الصفيحات معاً. والأولويات التمريضية تتبع مباشرةً: الحماية من العدوى وتطبيق احتياطات النزف. وفقر الدم الانحلالي تدمير مبكّر للكريّات الحمر يعطي فقر دم مع يرقان وبول داكن وضخامة طحال وارتفاع الشبكيات. وفقر دم المرض المزمن يرافق الالتهاب المزمن والعدوى والخباثة ومرض الكلى، ويتحسّن بعلاج الحالة الكامنة.
🔑
Memory aid
مفتاح للحفظ
Iron with vitamin C, away from tea, coffee, milk and antacids. It turns the stools black — that is expected and is not melaena.
الحديد مع فيتامين ج بعيداً عن الشاي والقهوة والحليب ومضادّات الحموضة. ويُسوِّد البراز — وهذا متوقَّع وليس غائطاً قطرانياً (ميلينا).
⭐
Key point
نقطة أساسية
B12 deficiency is the anaemia with neurological signs, and pernicious anaemia is treated with lifelong injections because intrinsic factor is absent. Folate deficiency has no neurological signs.
نقص ب١٢ هو فقر الدم ذو العلامات العصبية، وفقر الدم الوبيل يُعالَج بحقن مدى الحياة لغياب العامل الداخلي. ونقص الفولات بلا علامات عصبية.
Erythropoiesis: maturation from proerythroblast through basophilic, polychromatic and acidophil erythroblasts to the reticulocyte and the mature erythrocyteتكوّن كريات الدم الحمراء: مراحل النضج من طليعة الأرومة الحمراء، مروراً بالأرومة الحمراء المحبّة للأساس ثم متعدّدة الصبغات ثم المحبّة للحمض، إلى الخلية الشبكية ثم كرية الدم الحمراء الناضجةServier Medical Art · CC BY 4.0
16
8.15 · Interpreting the Blood Count٨٫١٥ · تفسير تعداد الدم
The mean cell volume is the most useful single figure for classifying an anaemia, because it points directly at the cause. A low MCV — microcytic anaemia suggests iron deficiency or thalassaemia. A normal MCV — normocytic anaemia suggests acute blood loss, anaemia of chronic disease, or renal disease. A high MCV — macrocytic anaemia suggests vitamin B12 or folate deficiency, and also alcohol excess, liver disease and hypothyroidism. Reading the MCV first narrows the possibilities before any other test is considered.
متوسّط حجم الكريّة أنفع رقم منفرد لتصنيف فقر الدم، فهو يشير مباشرةً للسبب. فانخفاضه — فقر دم صغير الكريّات يوحي بنقص الحديد أو الثلاسيميا. والطبيعي — سويّ الكريّات يوحي بفقد دم حادّ أو فقر دم المرض المزمن أو مرض كلوي. والمرتفع — كبير الكريّات يوحي بنقص فيتامين ب١٢ أو الفولات وأيضاً إفراط الكحول ومرض الكبد وقصور الدرقية. وقراءة متوسّط حجم الكريّة أولاً تضيّق الاحتمالات قبل النظر في أيّ فحص آخر.
FERRITIN measures the body’s IRON STORES, and a LOW ferritin confirms iron deficiency. But it carries a trap worth knowing: ferritin is an ACUTE PHASE PROTEIN, so it RISES in inflammation, infection and malignancy — which means a normal or high ferritin does NOT exclude iron deficiency in an unwell patient. Where there is inflammation, the CRP is read alongside it and other iron studies are used.
والفيريتين يقيس مخازن الحديد والمنخفض يؤكّد النقص. لكنه يحمل فخّاً يستحقّ المعرفة: أنه بروتين طور حادّ فيرتفع في الالتهاب والعدوى والخباثة — ما يعني أن الفيريتين الطبيعي أو المرتفع لا يستبعد نقص الحديد في مريض متوعّك. وحيث يوجد التهاب يُقرأ البروتين المتفاعل C (CRP) إلى جانبه وتُستخدم دراسات الحديد الأخرى.
Haemoglobin electrophoresis, or high performance liquid chromatography, is the test that identifies the type of haemoglobin present and therefore confirms sickle cell disease and thalassaemia and — importantly — distinguishes the trait from the disease. That distinction is exactly what the premarital screening programme rests on, since a person with the trait is healthy but can pass the gene on. A simple sickling or solubility test can indicate that sickle haemoglobin is present but cannot separate trait from disease, which is why electrophoresis is required for a definitive answer.
والرحلان الكهربائي للهيموغلوبين أو الاستشراب السائل عالي الأداء هو الفحص الذي يحدّد نوع الهيموغلوبين الموجود فيؤكّد داء الخلايا المنجلية والثلاسيميا، ويميّز — وهذا هو الأهمّ — السمة من المرض. وذلك التمييز هو بالضبط ما يقوم عليه برنامج الفحص قبل الزواج، فحامل السمة سليم لكنه يستطيع توريث الجين. واختبار التمنجل أو الذوبانية البسيط قد يشير لوجود هيموغلوبين منجلي لكنه لا يفصل السمة عن المرض، ولهذا يلزم الرحلان لجواب قاطع.
🔑
Memory aid
مفتاح للحفظ
Low MCV — iron deficiency or thalassaemia. Normal MCV — blood loss, chronic disease or renal disease. High MCV — B12 or folate deficiency.
متوسّط حجم كريّة منخفض — نقص حديد أو ثلاسيميا. وطبيعي — فقد دم أو مرض مزمن أو كلوي. ومرتفع — نقص ب١٢ أو فولات.
🚩
Watch out
تنبيه
Ferritin is an acute phase reactant, so a patient with inflammation can be iron deficient with a normal or raised ferritin. Interpret it alongside the inflammatory markers.
الفيريتين مفاعل طور حادّ، فالمريض بالتهاب قد يكون ناقص الحديد بفيريتين طبيعي أو مرتفع. ويجب تفسيره إلى جانب واسمات الالتهاب.
17
8.16 · Sickle Cell Disease and Thalassaemia٨٫١٦ · داء الخلايا المنجلية والثلاسيميا
In sickle cell disease an abnormal haemoglobin polymerises when deoxygenated, distorting red cells into a rigid sickle shape that blocks small vessels and is destroyed early. The result is vaso-occlusion causing pain and tissue infarction, plus a chronic haemolytic anaemia. It is inherited autosomal recessively: a person with one gene has the trait and is generally well, while two genes give the disease.
في داء الخلايا المنجلية يتبلمر هيموغلوبين شاذّ عند نزع الأكسجين فيشوّه الكريّات الحمر إلى شكل منجلي صلب يسدّ الأوعية الصغيرة، وتُدمَّر الكريّات مبكّراً. والنتيجة انسداد وعائي يسبّب ألماً واحتشاء نسيج مع فقر دم انحلالي مزمن. وهو يُورَّث بنمط صبغي جسمي متنحٍّ: فمن لديه جين واحد لديه السمة وهو بخير عموماً، ومن لديه جينان لديه المرض.
The triggers of a crisis are worth memorising because avoiding them is the patient's daily work: infection, dehydration, hypoxia, cold, physical exertion, emotional stress, high altitude or flying, alcohol and pregnancy. A vaso-occlusive crisis presents with severe pain, most often in the bones, back, chest or abdomen, and the pain is frequently under-treated because staff underestimate it — a patient in crisis needs prompt and adequate analgesia, often including strong opioids, and doubting him is a documented and serious failure of care.
ومحفّزات النوبة تستحقّ الحفظ فتجنّبها هو العمل اليومي للمريض: العدوى والجفاف ونقص الأكسجة والبرد والجهد البدني والكرب النفسي والارتفاعات العالية أو الطيران والكحول والحمل. والنوبة الانسدادية الوعائية تتظاهر بألم شديد في العظام أو الظهر أو الصدر أو البطن غالباً، والألم كثيراً ما يُعالَج بأقلّ من اللازم لأن الطاقم يقلّل تقديره — فالمريض في نوبة يحتاج مسكّناً سريعاً وكافياً يشمل أفيونيات قوية غالباً، والتشكيك فيه إخفاق موثّق وخطير في الرعاية.
1
HYDRATION
Adequate hydration — oral if the patient can drink, intravenous if not, and avoiding over-hydration (risk of pulmonary oedema and acute chest syndrome) — to reduce blood viscosity — which is what stops the sickling propagating.
الإماهة — إماهة كافية: فموياً إن استطاع المريض الشرب ووريدياً إن لم يستطع، مع تجنّب فرط الإماهة (خطر الوذمة الرئوية ومتلازمة الصدر الحادّة) — لتقليل لزوجة الدم، وهذا ما يمنع استمرار التمنجل في الانتشار.
2
OXYGENATION
Oxygen if the saturation is below target — and treat the cause of any hypoxia.
الأكسجة — أكسجين إن كان التشبّع دون الهدف — ومعالجة سبب أيّ نقص أكسجة.
3
ANALGESIA — and this is the one that is got wrong
Crisis pain is SEVERE and needs STRONG OPIOIDS, promptly and regularly — not ‘as required’ after a wait.
التسكين — وهذا ما يُخطأ فيه: ألم النوبة شديد ويحتاج أفيونيات قوية فوراً وبانتظام — لا «عند الطلب» بعد انتظار.
4
Plus WARMTH, rest and treating the trigger
Infection, dehydration, cold, hypoxia, stress and exertion — each identified and addressed.
مع الدفء والراحة وعلاج المحفّز — العدوى والجفاف والبرد ونقص الأكسجة والكرب والجهد، يُحدَّد كلّ منها ويُعالَج.
5
And the point that must be said
Patients with sickle cell disease are systematically UNDER-TREATED for pain, and are frequently wrongly suspected of drug-seeking. A patient who says his pain is 10 and knows exactly what works for him is describing his own disease, not manipulating.
والنقطة الواجب قولها — ألم مرضى داء الخلايا المنجلية يُعالَج بأقلّ من اللازم على نحو منهجي، ويُشتبه بهم كثيراً خطأً في السعي وراء المخدّرات؛ والمريض الذي يقول إن ألمه ١٠ ويعرف تماماً ما ينفعه إنما يصف مرضه هو ولا يتلاعب.
THALASSAEMIA is a different inherited defect — REDUCED PRODUCTION of a globin chain — and in its severe form produces severe anaemia from early childhood requiring REGULAR LIFELONG TRANSFUSION.
الثلاسيميا عيب موروث مختلف — إنتاج منقوص لسلسلة غلوبين وفي شكلها الشديد تُنتج فقر دم شديداً من الطفولة المبكّرة يتطلّب نقل دم منتظماً مدى الحياة.
•Which creates the problem that DEFINES its managementوهذا ما يُنشئ المشكلة التي تحدّد طريقة تدبيره
Repeated transfusion causes IRON OVERLOADThe body has no way to excrete excess iron — so it accumulates in the heart, liver and endocrine glands.نقل الدم المتكرّر يسبّب فرط حمل الحديد — فلا سبيل للجسم لطرح الفائض، فيتراكم في القلب والكبد والغدد الصماء.
And iron overload is what kills themCardiac failure and arrhythmia, cirrhosis, diabetes, delayed puberty and growth failure — not the anaemia.وفرط حمل الحديد ما يقتلهم — قصور القلب واضطراب النظم والتشمّع والسكّري وتأخّر البلوغ وفشل النموّ — لا فقر الدم.
So CHELATION is the treatment that determines survivalAnd adherence to it is the single most important thing — which is hard, because it is burdensome, and the benefit is invisible while the burden is daily.فالاستخلاب هو العلاج الذي يحدّد البقاء — والالتزام به هو الأمر الأهمّ على الإطلاق — وهو أمر صعب لأنه مرهق، والفائدة غير مرئية بينما العبء يومي.
Which makes the nursing about adherenceAsk HOW he takes it rather than IF; address the practical barriers; and explain what it prevents rather than what it does — the same problem as every invisible-benefit medicine in this book.ما يجعل التمريض يدور حول الالتزام — يُسأل المريض كيف يتناوله لا هل يتناوله؛ وتُعالَج العوائق العملية؛ ويُشرَح ما يمنعه العلاج لا ما يفعله — وهي المشكلة نفسها لكل دواء فائدته غير مرئية في هذا الكتاب.
🔑
Memory aid
مفتاح للحفظ
Sickle cell crisis: hydration, oxygen and analgesia, keep him warm and look for infection. Triggers are infection, dehydration, hypoxia, cold, exertion and stress.
نوبة المنجلية: إماهة وأكسجين وتسكين، ويُبقى المريض دافئاً ويُبحث عن عدوى. والمحفّزات عدوى وجفاف ونقص أكسجة وبرد وجهد وكرب.
🚩
Watch out
تنبيه
Chest pain, fever and breathlessness in sickle cell disease is acute chest syndrome, a leading cause of death. Escalate urgently rather than treating it as part of the pain crisis.
ألم الصدر والحمّى وضيق النفس في المنجلية متلازمة صدر حادّة وهي سبب رئيس للوفاة. يجب التصعيد عاجلاً وعدم التعامل معها كجزء من نوبة الألم.
⭐
Key point
نقطة أساسية
Sickle cell pain is routinely under-treated because staff doubt it. Give the analgesia prescribed, promptly and adequately.
ألم المنجلية يُعالَج بأقلّ من اللازم روتينياً لأن الطاقم يشكّ فيه. يُعطى المسكّن الموصوف سريعاً وبكفاية.
Thrombocytopenia — a low platelet count — gives petechiae, purpura, easy bruising, bleeding gums, nosebleeds, prolonged bleeding from puncture sites and, when severe, internal and intracranial bleeding. Bleeding precautions are the nursing response: a soft toothbrush and no flossing, an electric razor rather than a blade, avoiding intramuscular injections and rectal procedures where possible, applying prolonged pressure after any venepuncture, preventing constipation and straining, avoiding aspirin and non-steroidal anti-inflammatory drugs, and protecting from falls and knocks.
قلّة الصفيحات — أي انخفاض عددها — تعطي حبرات وفرفرية وسهولة التكدّم ونزف لثة ورعاف ونزفاً مطوّلاً من مواقع الوخز، وعند الشدّة نزفاً داخلياً وداخل القحف. واحتياطات النزف هي الاستجابة التمريضية: فرشاة ناعمة ولا خيط أسنان، وماكينة حلاقة كهربائية لا شفرة، وتجنّب الحقن العضلي والإجراءات الشرجية حيث أمكن، وتطبيق ضغط مطوّل بعد أيّ وخز وريدي، ومنع الإمساك والإجهاد، وتجنّب الأسبرين ومضادّات الالتهاب غير الستيرويدية، والحماية من السقوط والصدمات.
HAEMOPHILIA is an inherited deficiency of a clotting factor, affecting mainly MALES — X-linked recessive — and it causes bleeding into JOINTS (haemarthrosis) and muscles, as well as prolonged bleeding after injury or surgery.
الناعور نقص موروث لعامل تخثّر يصيب الذكور أساساً — متنحٍّ مرتبط بالصبغي X — ويسبّب نزفاً في المفاصل (تدمّي المفصل) والعضلات، فضلاً عن نزف مطوّل بعد الإصابة أو الجراحة.
1
Give FACTOR REPLACEMENT first — and early
Before imaging, before assessment, before anything else — bleeding into a joint destroys it, and the damage begins immediately.
يُعطى بديل العامل أولاً ومبكّراً — قبل التصوير وقبل التقييم وقبل أيّ شيء آخر؛ فالنزف داخل المفصل يدمّره، ويبدأ الضرر فوراً.
2
Then rest, ice, compression and elevation
For the joint — after the factor, not instead of it.
ثم الراحة والثلج والضغط والرفع للمفصل — بعد العامل لا بدلاً عنه.
3
NO intramuscular injections
And no aspirin or NSAIDs — which is the list that is broken by someone who does not know the diagnosis.
لا حقن عضلية — ولا أسبرين ولا مضادّات الالتهاب غير الستيرويدية — وهذه هي القائمة التي يخرقها من لا يعرف التشخيص.
4
Avoid contact sports; use a soft toothbrush
And pressure for longer after any venepuncture.
تُتجنَّب رياضات التماسّ وتُستخدم فرشاة ناعمة — ويُطبَّق ضغط أطول بعد أيّ وخز وريدي.
5
And BELIEVE him when he says he is bleeding
A patient with haemophilia knows what an internal bleed feels like before there is anything to see — and treating on his report rather than on a sign is the standard.
وتصديق المريض حين يقول إنه ينزف — فهو يعرف شعور النزف الداخلي قبل ظهور أيّ شيء، والمعيار هو العلاج بناءً على ما يخبر به لا على علامة.
Glucose-6-phosphate dehydrogenase deficiency is an inherited enzyme defect, X-linked and therefore affecting mainly males, and it is highly prevalent in this region — studies from the Eastern Province have reported it in a substantial proportion of those screened. The red cells lack protection against oxidative stress, so exposure to an oxidant precipitates acute haemolysis: sudden pallor, jaundice, dark or cola-coloured urine, back or abdominal pain and rapidly falling haemoglobin.
نقص إنزيم نازعة هيدروجين الغلوكوز-٦-فوسفات عيب إنزيمي موروث مرتبط بالصبغي X ومن ثمّ يصيب الذكور أساساً، وهو عالي الانتشار في هذه المنطقة — فقد أبلغت دراسات من المنطقة الشرقية عنه لدى نسبة معتبرة ممّن فُحصوا. والكريّات الحمر تفتقر للحماية من الكرب التأكسدي، فالتعرّض لمؤكسد يُحدث انحلال دم حادّاً: شحوب مفاجئ ويرقان وبول داكن أو بلون الكولا وألم ظهر أو بطن وهبوط سريع في الهيموغلوبين.
The whole management of G6PD deficiency is AVOIDANCE, and the list must be taught EXPLICITLY, because the triggers are ORDINARY THINGS.
تدبير نقص G6PD كلّه تجنّب، والقائمة يجب تعليمها صراحةً لأن المحفّزات أشياء عادية.
•The triggers — named, in writing, and given to the familyالمحفّزات — تُسمّى كتابةً وتُعطى للأسرة
FAVA BEANS — broad beansWhich is where ‘favism’ comes from, and it includes anything cooked with them, and inhaled pollen from the plant.الفول (الباقلاء) — ومنه اسم التفوّل: ويشمل أيّ شيء يُطهى معه، وحبوب لقاح النبات المستنشَقة.
Certain drugsSome antimalarials, sulphonamides, nitrofurantoin, and others — which is why the deficiency is flagged on the record and checked before prescribing.أدوية معيّنة — بعض مضادّات الملاريا والسلفوناميدات والنيتروفورانتوين وغيرها — ولهذا يُوسَم نقص الإنزيم في السجل ويُتحقَّق منه قبل وصف الدواء.
Naphthalene — mothballsIncluding clothes stored with them, which is how an infant is exposed without anyone eating anything.النفتالين — كرات العثّ: بما فيه الملابس المخزّنة معها، وبهذا يتعرّض الرضيع دون أن يأكل أحد شيئاً.
And INFECTION itselfWhich is the commonest trigger of all, and the one that cannot be avoided — so a child with G6PD deficiency who becomes unwell is watched for haemolysis.والعدوى نفسها — أشيع محفّز على الإطلاق ولا يمكن تجنّبه — ولذا يُراقَب الطفل المصاب بنقص G6PD إذا توعّك بحثاً عن انحلال الدم.
The signs of haemolysis to reportSudden pallor, jaundice, dark urine, fatigue, breathlessness and back or abdominal pain — given in writing, because it happens fast.علامات الانحلال الواجب الإبلاغ عنها — شحوب مفاجئ ويرقان وبول داكن وتعب وضيق نفس وألم في الظهر أو البطن — وتُعطى مكتوبة لأن الأمر يحدث بسرعة.
🔑
Memory aid
مفتاح للحفظ
Bleeding precautions: soft toothbrush, electric razor, no intramuscular injections, prolonged pressure after venepuncture, no aspirin or NSAIDs.
احتياطات النزف: فرشاة ناعمة وماكينة حلاقة كهربائية ولا حقن عضلية وضغط مطوّل بعد الوخز الوريدي ولا أسبرين ولا مضادّات الالتهاب غير الستيرويدية.
🚩
Watch out
تنبيه
In G6PD deficiency, fava beans, infection and a defined list of drugs precipitate acute haemolysis. Give the family the written list and tell them to check every new medicine.
في نقص G6PD يُحدث الفول والعدوى وقائمة أدوية محدّدة انحلال دم حادّاً. تُعطى الأسرة القائمة المكتوبة وتُخبَر بوجوب مراجعة كلّ دواء جديد.
19
8.18 · Von Willebrand Disease and Surgery in Sickle Cell٨٫١٨ · داء فون ويلبراند والجراحة في المنجلية
Von Willebrand disease is the COMMONEST inherited bleeding disorder and, unlike haemophilia, it affects BOTH SEXES equally — which is why it is under-recognised in women, whose symptoms are attributed to something else.
داء فون ويلبراند أشيع اضطراب نزفي موروث وخلافاً للناعور يصيب الجنسين بالتساوي — ولهذا لا يُتعرَّف عليه بما يكفي لدى النساء، إذ تُنسب أعراضهنّ إلى سبب آخر.
•How it presents — and why it is missedكيف يظهر — ولماذا يُغفَل عنه
HEAVY MENSTRUAL BLEEDINGFrequently the only symptom, and frequently normalised — ‘heavy periods run in our family’ is sometimes a bleeding disorder running in the family.نزف طمثي غزير — غالباً العرَض الوحيد، وكثيراً ما يُعدّ أمراً طبيعياً — فعبارة «الدورات الغزيرة تسري في عائلتنا» تعني أحياناً اضطراب نزف يسري في العائلة.
Easy bruising, nosebleeds, bleeding gumsAnd prolonged bleeding after dental extraction or minor surgery — which is the history that identifies it.تكدّم سهل ورعاف ونزف لثة — ونزف مطوّل بعد قلع سنّ أو جراحة بسيطة — وهذه هي القصة التي تكشفه.
So take a bleeding history properlyAsk about dental extractions, tonsillectomy, childbirth and previous surgery, and about the family — not just ‘do you bleed easily?’فتؤخذ قصّة النزف كما ينبغي — يُسأل عن قلع الأسنان واستئصال اللوزتين والولادة والجراحات السابقة وعن الأسرة، لا عن «هل تنزف بسهولة؟» فقط.
And plan surgery in advanceTreatment before the procedure, and tranexamic acid — arranged with haematology, not discovered when the bleeding starts.ويُخطَّط للجراحة مسبقاً — علاج قبل الإجراء وحمض الترانيكساميك، بالتنسيق مع أمراض الدم، لا اكتشافاً عند بدء النزف.
A patient with sickle cell disease coming to surgery needs SPECIFIC PLANNING, because anaesthesia and surgery expose him to EVERY trigger of a crisis at once.
HYPOXIAfrom the anaesthetic and from atelectasisنقص الأكسجة — من التخدير والانخماص
DEHYDRATIONfrom fasting and from blood lossالجفاف — من الصيام وفقد الدم
COLDthe theatre is cold and he is uncoveredالبرد — غرفة العمليات باردة وهو مكشوف
ACIDOSIS, PAIN and STASISfrom tourniquets and from lying stillالحماض والألم والركود — من العاصبات والاستلقاء دون حركة
1
Involve haematology BEFORE the operation
Not on the day — transfusion may be planned to reduce the sickle proportion.
إشراك أمراض الدم قبل العملية — لا في يومها؛ فقد يُخطَّط لنقل دم لتقليل نسبة الخلايا المنجلية.
2
Keep him WARM
Actively warmed throughout, including in transfer — which is the easiest one to get wrong.
يُبقى المريض دافئاً — بتدفئة فاعلة طوال الوقت بما فيه أثناء النقل، وهذا أسهل ما يقع فيه الخطأ.
3
Keep him HYDRATED
Intravenous fluids through the fasting period — he is not left dry from midnight.
يُبقى المريض مُماهاً — سوائل وريدية طوال فترة الصيام، فلا يُترك جافّاً منذ منتصف الليل.
4
Keep him OXYGENATED
Supplemental oxygen, and attention to atelectasis afterwards — which is what acute chest syndrome grows from.
يُبقى المريض مؤكسَجاً — أكسجين إضافي وانتباه للانخماص بعد الجراحة — فمنه تنشأ متلازمة الصدر الحادّة.
5
Treat pain PROPERLY
Uncontrolled pain is itself a trigger — so analgesia is prevention here, not comfort.
يُعالَج الألم كما ينبغي — فالألم غير المضبوط محفّز بذاته، فالتسكين هنا وقاية لا راحة.
6
And watch for ACUTE CHEST SYNDROME
Fever, chest pain, breathlessness, hypoxia and a new infiltrate — the commonest cause of death in sickle cell disease, and it is a postoperative complication. Escalate at the first sign.
ومراقبة متلازمة الصدر الحادّة — حمّى وألم صدر وضيق نفس ونقص أكسجة وارتشاح جديد؛ وهي أشيع سبب وفاة في الداء المنجلي، وهي مضاعفة تحدث بعد الجراحة. ويُصعَّد الأمر عند أول علامة.
⭐
Key point
نقطة أساسية
Von Willebrand disease is the commonest inherited bleeding disorder and affects both sexes. Heavy menstrual bleeding since the first period is the presentation most often missed.
داء فون ويلبراند أشيع اضطراب نزفي موروث ويصيب الجنسين. والنزف الطمثي الغزير منذ أول دورة التظاهر الأكثر إغفالاً.
🚩
Watch out
تنبيه
Surgery exposes a patient with sickle cell disease to every trigger of a crisis at once. Keep him warm, hydrated and oxygenated, treat pain promptly, and involve haematology before the operation.
الجراحة تعرّض مريض المنجلية لكلّ محفّزات النوبة في آن. يُبقى المريض دافئاً ومُماهاً ومؤكسَجاً، ويُعالَج الألم فوراً، وتُشرَك أمراض الدم قبل العملية.
20
8.19 · Leukaemia, Lymphoma and Myeloma٨٫١٩ · ابيضاض الدم واللمفوما والورم النقوي
Leukaemia is malignant proliferation of white cell precursors in the marrow, which CROWDS OUT normal production.That single mechanism explains the presentation.
ابيضاض الدم تكاثر خبيث لطلائع الكريّات البيضاء في النقي يزاحم الإنتاج الطبيعي. وتلك الآلية وحدها تفسّر التظاهر.
1
Crowds out RED cells
→ ANAEMIA — fatigue, pallor, breathlessness.
يزاحم الكريّات الحمراء ← فقر دم: تعب وشحوب وضيق نفس.
→ INFECTION — despite a high total white count, because the cells present do not work.
يزاحم الكريّات البيضاء الطبيعية ← عدوى رغم ارتفاع التعداد الكلّي، لأن الخلايا الموجودة لا تعمل.
4
Plus infiltration and turnover
Bone pain, lymphadenopathy, hepatosplenomegaly, and fever, night sweats and weight loss.
مع الارتشاح وزيادة دوران الخلايا — ألم عظم واعتلال عقد لمفية وضخامة كبد وطحال، وحمّى وتعرّق ليلي ونقص وزن.
Lymphoma arises in the lymphatic system and typically presents with painless enlarged lymph nodes, classically in the neck, together with the B symptoms — fever, drenching night sweats and unexplained weight loss, which carry prognostic weight. Multiple myeloma is a malignancy of plasma cells in the marrow, and its characteristic combination is bone pain — especially back pain — with hypercalcaemia, along with anaemia, renal impairment, recurrent infection and pathological fractures. The bone destruction and the hypercalcaemia together are what identify it.
اللمفوما تنشأ في الجهاز اللمفي وتتظاهر عادةً بضخامة عقد لمفية غير مؤلمة في العنق كلاسيكياً، مع أعراض ب — حمّى وتعرّق ليلي غزير ونقص وزن غير مفسَّر ولها دلالة إنذارية. والورم النقوي المتعدّد خباثة خلايا بلازمية في النقي، واجتماعه المميّز ألم عظمي — وخاصّةً ألم ظهر — مع فرط كالسيوم الدم، إضافةً إلى فقر دم واختلال كلوي وعدوى متكرّرة وكسور مرضية. وتدمير العظم وفرط الكالسيوم معاً هما ما يميّزانه.
NEUTROPENIA — a low neutrophil count, usually from chemotherapy or marrow failure — REMOVES the ability to mount a normal inflammatory response.So the usual signs of infection are ABSENT.
قلّة العدلات — تعداد عدلات منخفض ناجم عن العلاج الكيميائي أو فشل النقي عادةً — تُزيل القدرة على استجابة التهابية طبيعية. فعلامات العدوى المعتادة غائبة.
❌What is ABSENT
No pus — because pus is neutrophils
Little redness or swelling
No localising signs — the chest X-ray may be clear
So the infection is INVISIBLE until he is septic
ما هو غائب — لا قيح (لأن القيح هو العدلات)، ولا احمرار أو تورّم يُذكَر، ولا علامات موضعية، وقد تكون صورة الصدر الشعاعية سليمة؛ فتبقى العدوى غير مرئية حتى يصاب المريض بالإنتان.
🌡️What is left — and it is enough
FEVER — and it may be the ONLY sign
Or simply feeling unwell, with rigors or hypotension
NEUTROPENIC SEPSIS IS A MEDICAL EMERGENCY
Broad-spectrum antibiotics within ONE HOUR
Cultures taken — but antibiotics NOT delayed for them
ما يبقى ويكفي — الحمّى وقد تكون العلامة الوحيدة، أو مجرّد الشعور بالتوعّك مع رعشة أو هبوط ضغط: الإنتان بقلّة العدلات حالة طبية إسعافية — تُعطى مضادّات حيوية واسعة الطيف خلال ساعة واحدة، وتُؤخذ المزارع لكن لا يُؤخَّر إعطاء المضادّات الحيوية بسببها.
And the teaching that goes home with him: a temperature above the stated threshold, or feeling unwell, means come in IMMEDIATELY — day or night, without waiting to see how it goes, with a card and a direct number. He does not take paracetamol first, because it masks the only sign he has.
والتعليم الذي يذهب معه للمنزل: أن حرارةً فوق العتبة المذكورة أو الشعور بالتوعّك تعني الحضور فوراً — ليلاً أو نهاراً، دون انتظار لمعرفة كيف ستتطوّر الحالة، ببطاقة ورقم مباشر. ولا يتناول باراسيتامول أولاً فهو يحجب العلامة الوحيدة لديه.
Bone marrow aspiration and biopsy is usually taken from the POSTERIOR ILIAC CREST under local anaesthetic.
ورشف نقي العظم وخزعته يُؤخَذان من العرف الحرقفي الخلفي تحت تخدير موضعي عادةً.
1
Explain what it will FEEL like
The aspiration causes a brief, intense, dragging pain that the local anaesthetic does NOT prevent — because the local numbs the skin and periosteum, not the marrow cavity. Saying this in advance is the whole of the preparation; discovering it is what makes it traumatic.
شرح كيف سيكون الإحساس — فالرشف يسبّب ألماً قصيراً شديداً أشبه بالسحب لا يمنعه المخدّر الموضعي، لأن المخدّر الموضعي يخدّر الجلد والسمحاق لا جوف النقي. وقول ذلك مسبقاً هو التحضير كلّه؛ أما اكتشافه فجأة فهو ما يجعل التجربة صادمة.
2
Position and support him
Lateral or prone, and someone stays at his head talking to him.
وضع المريض ودعمه — جانبياً أو منبطحاً، ويبقى شخص عند رأسه يتحدّث إليه.
3
Afterwards — pressure, then a dressing
Pressure for longer if the platelets are low, and lie him on the site for a period.
بعدها — ضغط ثم ضمادة: وضغط أطول إن كانت الصفيحات منخفضة، ويُضجَع المريض على موضع الأخذ لفترة.
4
Then observe for bleeding
And tell him to report increasing pain, swelling or bleeding at the site, and to keep the dressing dry.
ثم مراقبة النزف — ويُطلب من المريض الإبلاغ عن ألم متزايد أو تورّم أو نزف في الموضع، وإبقاء الضماد جافّاً.
🔑
Memory aid
مفتاح للحفظ
Leukaemia presents as anaemia plus infection plus bleeding — the three failing cell lines together.
الابيضاض يتظاهر بفقر دم مع عدوى مع نزف — الخطوط الخلوية الثلاثة الفاشلة معاً.
🚩
Watch out
تنبيه
A fever in a neutropenic patient is a medical emergency needing cultures and antibiotics within the hour. The usual signs of infection are blunted, so fever may be the only one.
الحمّى لدى مريض قليل العدلات طارئ طبي يحتاج مزارع ومضادّات حيوية خلال الساعة. فعلامات العدوى المعتادة خامدة وقد تكون الحمّى الوحيدة.
21
8.20 · Further Haematological Conditions٨٫٢٠ · حالات دموية أخرى
Polycythaemia is an excess of red cells, raising the blood viscosity. It gives headache, dizziness, visual disturbance, a plethoric red complexion, and characteristically itching that is worse after a hot bath or shower, and its danger is thrombosis — stroke, myocardial infarction and venous thrombosis. Treatment includes venesection to remove blood, alongside aspirin and sometimes cytoreductive drugs. Myelodysplastic syndrome is a group of marrow disorders producing ineffective blood cell production and cytopenias, and it may transform into acute leukaemia.
كثرة الحمر فائض في الكريّات الحمر يرفع لزوجة الدم. ويعطي صداعاً ودوخة واضطراب رؤية ولوناً أحمر محتقناً، وحكّة مميِّزة تزداد سوءاً بعد حمّام ساخن أو دُشّ، وخطره الخثار — سكتة دماغية واحتشاء عضلة القلب وخثار وريدي. والعلاج يشمل الفصد الوريدي لسحب الدم مع أسبرين وأدوية خافضة لعدد الخلايا (مثبّطة للنقي) أحياناً. ومتلازمة خلل التنسّج النقوي مجموعة اضطرابات نقي تُنتج إنتاجاً غير فعّال لخلايا الدم وقلّة خلايا، وقد تتحوّل لابيضاض حادّ.
After a SPLENECTOMY — or where the spleen has been damaged by disease, as happens in sickle cell disease — the patient loses a major defence against ENCAPSULATED ORGANISMS, and is at lifelong risk of OVERWHELMING POST-SPLENECTOMY INFECTION, which can kill within hours.
بعد استئصال الطحال — أو حيث تلف الطحال بسبب المرض كما في الداء المنجلي — يفقد المريض دفاعاً رئيساً ضدّ الكائنات المحفَّظة ويكون في خطر مدى الحياة من عدوى ساحقة بعد استئصال الطحال قد تقتل خلال ساعات.
1
VACCINATION
Against the encapsulated organisms — pneumococcus, meningococcus and Haemophilus influenzae type b — plus annual influenza. Given BEFORE an elective splenectomy where possible.
التطعيم — ضدّ الكائنات المحفَّظة: المكوّرات الرئوية والمكوّرات السحائية والمستدمية النزلية من النمط ب، إضافةً إلى الإنفلونزا السنوية. يُعطى قبل الاستئصال الاختياري حيثما أمكن.
2
Prophylactic ANTIBIOTICS
Long-term, and lifelong in many — and this is the one people stop taking because they feel well.
مضادات حيوية وقائية — طويلة الأمد، ومدى الحياة لدى كثيرين؛ وهي الأدوية التي يتوقّف الناس عن تناولها لأنهم يشعرون بالعافية.
3
A standby supply and a card
To start at the first sign of infection, plus a medical alert card or bracelet.
إمداد احتياطي وبطاقة — للبدء عند أول علامة عدوى، إضافةً إلى بطاقة أو سوار تنبيه طبي.
4
Seek help URGENTLY for any fever
Same day, not the next — because the deterioration is measured in hours.
طلب المساعدة العاجلة عند أيّ حمّى — في اليوم نفسه لا في اليوم التالي، لأن التدهور يُقاس بالساعات.
5
And tell them about travel
Malaria and animal bites carry a much higher risk — so travel advice is part of the discharge, not an afterthought.
وإخبار المريض بشأن السفر — فالملاريا وعضّات الحيوانات تحمل خطراً أعلى بكثير؛ لذلك فإرشادات السفر جزء من تعليمات الخروج لا فكرة لاحقة.
•Three complications of treatment◆ ثلاث مضاعفات للعلاج
TUMOUR LYSIS syndromeFollows rapid destruction of cancer cells, usually soon after starting chemotherapy in a bulky, fast-growing tumour. The cells release their contents: HIGH potassium, HIGH phosphate, HIGH uric acid and LOW calcium — causing arrhythmia and acute kidney injury. Prevented by hydration and drugs to lower urate, and the nursing is strict fluid balance and urgent reporting of the electrolytes.متلازمة انحلال الورم تعقب التدمير السريع للخلايا السرطانية، وتحدث عادةً بُعيد بدء العلاج الكيميائي في ورم ضخم سريع النموّ. تُطلِق الخلايا محتوياتها: ارتفاع البوتاسيوم وارتفاع الفوسفات وارتفاع حمض اليوريك وانخفاض الكالسيوم — ممّا يسبّب اضطراب النظم القلبي وأذيّة كلوية حادّة. وتُمنَع بالإماهة وبأدوية خافضة لمستوى اليورات، ويتمثّل التمريض في الموازنة الصارمة للسوائل والإبلاغ العاجل عن نتائج الشوارد.
GRAFT-VERSUS-HOST diseaseAfter a stem cell transplant — the donated immune cells attack the RECIPIENT’S tissues. It affects the skin, gut and liver: rash, diarrhoea and jaundice. The direction is the opposite of rejection, which is what questions test.داء الطعم ضدّ المضيف: يحدث بعد زرع الخلايا الجذعية — إذ تهاجم الخلايا المناعية المتبرَّع بها أنسجة المتلقّي. ويصيب الجلد والأمعاء والكبد: طفح وإسهال ويرقان. واتجاهه عكس الرفض، وهذا ما تختبره الأسئلة.
And DISSEMINATED INTRAVASCULAR COAGULATIONThe clotting system is activated and CONSUMES its own factors, so he clots and bleeds at the same time — oozing from cannula sites, gums and wounds. Oozing from a puncture site in an unwell patient is a sign, not a nuisance, and the treatment is treating the cause.التخثّر المنتشر داخل الأوعية: يُنشَّط جهاز التخثّر ويستهلك عوامله هو نفسه، فيتخثّر المريض وينزف في آن واحد — مع رشح الدم من مواضع القنيّات واللثة والجروح. ورشح الدم من موضع وخز لدى مريض معتلّ الحالة علامة سريرية لا مجرّد إزعاج، وعلاجه معالجة السبب.
Anticoagulant reversal is worth knowing: warfarin is reversed with vitamin K, with prothrombin complex concentrate for urgent major bleeding, and heparin is reversed with protamine sulphate. Hydroxyurea is used in sickle cell disease to raise fetal haemoglobin and reduce the frequency of crises and acute chest syndrome; it requires blood count monitoring and is teratogenic. And an intravenous iron infusion, used where oral iron is not tolerated or absorbed, carries a small risk of anaphylaxis, so the patient is observed during and after the infusion with resuscitation equipment available.
عكس مضادّات التخثّر يستحقّ المعرفة: فالوارفارين يُعكَس بفيتامين ك مع مركّز معقّد البروثرومبين للنزف الكبير العاجل، والهيبارين يُعكَس بكبريتات البروتامين. والهيدروكسي يوريا يُستخدَم في المنجلية لرفع الهيموغلوبين الجنيني وتقليل تواتر النوبات ومتلازمة الصدر الحادّة؛ ويتطلّب مراقبة تعداد الدم وهو مشوّه للأجنّة. وتسريب الحديد الوريدي المستخدم حيث لا يُحتمَل الحديد الفموي أو لا يُمتَصّ يحمل خطراً صغيراً من التأق، فيُراقَب المريض أثناء التسريب وبعده ومعدّات الإنعاش متاحة.
🚩
Watch out
تنبيه
After splenectomy the patient needs vaccination against encapsulated organisms, often prophylactic antibiotics, a medical alert card, and urgent care for any fever. Infection can go from well to fatal within hours.
بعد استئصال الطحال يحتاج المريض تطعيماً ضدّ الكائنات المحفَّظة ومضادّات حيوية وقائية غالباً وبطاقة تنبيه طبي ورعاية عاجلة لأيّ حمّى. فالعدوى قد تنتقل من العافية للموت خلال ساعات.
🔑
Memory aid
مفتاح للحفظ
Tumour lysis syndrome: potassium up, phosphate up, urate up, calcium down — prevented by aggressive hydration before and during chemotherapy.
متلازمة انحلال الورم: بوتاسيوم مرتفع وفوسفات مرتفع وبولات مرتفعة وكالسيوم منخفض — وتُمنَع بإماهة مكثّفة قبل العلاج الكيميائي وأثناءه.
22
8.21 · Blood Components and Safe Transfusion٨٫٢١ · مكوّنات الدم ونقل الدم الآمن
Central venous catheter set — inserted under full surgical asepsis, with position confirmed before useطقم قسطرة وريدية مركزية — يُدخَل بعقامة جراحية كاملة ويُؤكّد موضعه قبل الاستخدامنص المخطط: القسطرة الوريدية المركزية — اللُّمَع؛ الوريد الأجوف العلوي. الخطّ المركزي: تُعرف وظيفة كلّ لُمعة؛ يُغسل الخطّ بين الأدوية؛ لا يُدفع بالقوة في خطّ مسدود؛ يُسجَّل تاريخ الإدخال، فخطر العدوى يزداد مع مدّة البقاء؛ وتُراجَع الحاجة إليه يومياً.Educational schematic (AL-FAHAD diagram, not a patient image) · مخطط تعليمي توضيحي وليس صورة لمريض
Blood is given as components, each for a purpose: packed red cells to raise the haemoglobin and oxygen-carrying capacity; platelets for thrombocytopenia with bleeding or before a procedure; fresh frozen plasma to replace clotting factors; and cryoprecipitate for fibrinogen. The ABO and Rhesus groups must be compatible, and giving ABO-incompatible blood causes the most dangerous reaction there is.
يُعطى الدم كمكوّنات لكلّ منها غرض: كريّات حمر مركّزة لرفع الهيموغلوبين وسعة حمل الأكسجين؛ وصفيحات لقلّة الصفيحات مع نزف أو قبل إجراء؛ وبلازما طازجة مجمّدة لتعويض عوامل التخثّر؛ والراسب البردي للفيبرينوجين. ويجب توافق زمرتي ABO والريصي، وإعطاء دم غير متوافق ABO يسبّب أخطر تفاعل ممكن الحدوث.
The safety of transfusion rests ALMOST ENTIRELY on the CHECKING PROCEDURE, because the most dangerous avoidable error, ABO-incompatible transfusion, comes from the WRONG UNIT being given to the WRONG PATIENT — not from the blood itself.
سلامة نقل الدم تقوم كلّها تقريباً على إجراء التحقّق، لأن أخطر خطأ يمكن تجنّبه، وهو نقل دم غير متوافق ABO، يأتي من إعطاء الوحدة الخاطئة للمريض الخاطئ — لا من الدم نفسه.
1
Positive patient identification AT THE BEDSIDE
Ask him to STATE his name and date of birth — not ‘are you Mr A?’ — and check against the wristband.
التعرّف الإيجابي على المريض عند السرير — يُطلَب من المريض أن يذكر بنفسه اسمه وتاريخ ميلاده، لا أن يُسأل «هل أنت السيد أ؟»، ثم يُطابَق ذلك مع سوار المعصم.
2
Check the unit against the prescription and the compatibility label
Blood group, unit number, expiry, and the patient’s details — all four.
مطابقة الوحدة مع الوصفة وبطاقة التوافق — زمرة الدم، ورقم الوحدة، وتاريخ انتهاء الصلاحية، وبيانات المريض: العناصر الأربعة جميعها.
3
Two people, checking INDEPENDENTLY
Not one reading aloud while the other agrees — which is the commonest way a two-person check fails.
شخصان يفحصان باستقلال — لا أن يقرأ أحدهما بصوت عالٍ والآخر يوافق، وهذه أشيع طريقة يفشل بها الفحص الثنائي.
4
Inspect the unit
Discolouration, clots, leaks or a damaged pack — returned, not used carefully.
فحص الوحدة — تغيّر اللون أو الخثرات أو التسرّب أو تلف الكيس: تُعاد الوحدة ولا تُستخدَم بحذر.
5
Baseline observations BEFORE starting
Temperature, pulse, blood pressure, respiratory rate — because a reaction is recognised by a CHANGE, and without a baseline there is nothing to change from.
قياسات أساسية قبل البدء — الحرارة والنبض وضغط الدم ومعدّل التنفّس، لأن التفاعل يُعرَف بحدوث تغيّر، ومن دون قياسات أساسية لا يوجد ما يُقاس التغيّر انطلاقاً منه.
6
And stay with him for the FIRST 15 MINUTES
Most severe reactions begin then — then observe as protocol directs.
والبقاء مع المريض أول ١٥ دقيقة — فمعظم التفاعلات الشديدة تبدأ حينها، ثم تُتابَع الملاحظة بحسب البروتوكول.
•The practical rules around the giving set◆ القواعد العملية المتعلّقة بطقم الإعطاء
NORMAL SALINE only — to prime and to flushNEVER dextrose, which haemolyses the cells, and never a calcium-containing solution such as Ringer’s or Hartmann’s, which causes clotting in the line by overcoming the citrate anticoagulant.المحلول الملحي العادي فقط — لتهيئة الخطّ ولغسله. ولا دكستروز أبداً، لأنه يسبّب انحلال الكريّات، ولا أيّ محلول يحوي الكالسيوم كمحلول رنغر أو هارتمان، لأنه يسبّب تخثّراً في الخطّ بتغلّبه على السترات المانعة للتخثّر.
The correct giving set, with a FILTERAnd changed per protocol — a set used for hours accumulates debris.طقم الإعطاء الصحيح مزوّد بمرشّح، ويُغيَّر بحسب البروتوكول — فالطقم المستعمل لساعات تتراكم فيه الشوائب.
Nothing else added to the unitNo drugs, ever — and nothing running into the same lumen.لا يُضاف شيء آخر إلى الوحدة — لا أدوية أبداً، ولا يجري شيء آخر عبر اللُّمعة نفسها.
And complete it within the time limitA unit out of controlled storage has a defined maximum time to be transfused — and one that has been out too long is discarded, not hurried.وإكمال نقلها ضمن الحدّ الزمني — فللوحدة الخارجة من التخزين المضبوط مدّة قصوى محدّدة لنقلها، والوحدة التي بقيت خارجه أطول من ذلك تُتلَف ولا يُستعجَل نقلها.
🚩
Watch out
تنبيه
Prime and flush blood lines with normal saline only. Dextrose haemolyses red cells and calcium-containing solutions can cause clotting in the line.
تُملأ خطوط الدم وتُغسل بمحلول ملحي عادي فقط. فالدكستروز يسبّب انحلال الكريّات الحمر والمحاليل الحاوية للكالسيوم قد تسبّب تخثّراً في الخطّ.
⭐
Key point
نقطة أساسية
Stay with the patient for the first fifteen minutes. The most severe reactions appear early, and this is the observation period that matters most.
يجب البقاء مع المريض أول خمس عشرة دقيقة. فأشدّ التفاعلات تظهر مبكّراً وهذه فترة الملاحظة الأهمّ.
23
8.22 · Transfusion Reactions٨٫٢٢ · تفاعلات نقل الدم
Whatever the reaction, the first action is always the same: stop the transfusion immediately. Then keep the intravenous line open with normal saline using a new giving set, assess the patient, take observations, and notify the doctor and the blood bank, keeping the unit and the giving set for investigation. Nothing is gained by pausing to decide which reaction it is first — stopping is the answer, and identification follows.
مهما كان التفاعل فالإجراء الأول واحد دائماً: يُوقَف نقل الدم فوراً. ثم يُبقى الخطّ الوريدي مفتوحاً بمحلول ملحي عادي بطقم إعطاء جديد، ويُقيَّم المريض وتؤخذ القياسات ويُبلَّغ الطبيب وبنك الدم، مع الاحتفاظ بالوحدة وطقم الإعطاء للتحقيق. ولا يُكسَب شيء من التوقّف لتحديد أيّ تفاعل هو أولاً — فالإيقاف هو الجواب والتحديد يتبع.
An acute haemolytic reaction is the one that kills, and it follows ABO incompatibility. It begins within minutes with fever and chills, low back or flank pain, a feeling of impending doom, flushing, tachycardia, hypotension, and dark or red urine as haemoglobin is released, progressing to renal failure, disseminated intravascular coagulation and shock. Stop, maintain the circulation, and expect aggressive fluids and monitoring of the urine output.
التفاعل الانحلالي الحادّ هو القاتل ويتبع عدم توافق ABO. ويبدأ خلال دقائق بحمّى وقشعريرة وألم أسفل الظهر أو الخاصرة وإحساس بهلاك وشيك واحمرار الوجه وتسرّع نبض وهبوط ضغط وبول داكن أو أحمر مع تحرّر الهيموغلوبين، ويتقدّم لفشل كلوي وتخثّر منتشر داخل الأوعية وصدمة. يُوقَف النقل ويُحافَظ على الدوران ويُتوقَّع إعطاء سوائل مكثّفة ومراقبة إدرار البول.
A febrile non-haemolytic reaction is the commonest and much less dangerous: fever and chills without haemolysis, usually from antibodies to donor white cells. It is still managed by stopping, because it cannot be distinguished from a haemolytic reaction at the bedside. An allergic reaction gives urticaria and itching, and a severe one gives anaphylaxis with wheeze, angioedema and hypotension.
التفاعل الحموي غير الانحلالي الأشيع وأقلّ خطراً بكثير: حمّى وقشعريرة دون انحلال، من أضداد لكريّات المتبرّع البيض عادةً. ويُدبَّر بالإيقاف مع ذلك، فلا يمكن تمييزه عن التفاعل الانحلالي عند السرير. والتفاعل التحسّسي يعطي شرى وحكّة، والشديد يعطي تأقاً مع أزيز ووذمة وعائية وهبوط ضغط.
Risk: elderly, cardiac or renal disease, rapid transfusion
فرط الحمل الدوراني المرتبط بنقل الدم (TACO) — فرط في الحجم: ضيق نفس وخراخر وارتفاع الضغط الوريدي الوداجي، مع ارتفاع ضغط الدم؛ ويستجيب للإبطاء أو الإيقاف وللمدرّ. عوامل الخطر: التقدّم في العمر، ومرض القلب أو الكلى، ونقل الدم السريع.
🫁TRALI — acute LUNG INJURY
An immune reaction in the lung, not a volume problem
Dyspnoea, hypoxia, bilateral infiltrates
HYPOTENSION, often with fever
NORMAL jugular venous pressure
A DIURETIC does not help and makes it worse — it needs respiratory support
أذيّة الرئة الحادّة المرتبطة بالنقل (TRALI) — تفاعل مناعي في الرئة وليس مشكلة حجم: ضيق نفس ونقص أكسجة وارتشاحات ثنائية الجانب، مع هبوط ضغط الدم وغالباً حمّى، وضغط وريدي وداجي طبيعي؛ ولا يفيد المدرّ بل يزيد الحالة سوءاً — فهي تحتاج دعماً تنفّسياً.
The discriminator that decides treatment: the BLOOD PRESSURE and the JVP. Overload is hypertensive with a raised JVP and responds to a diuretic; lung injury is hypotensive with a normal JVP and does not.Giving a diuretic to TRALI is the error the distinction exists to prevent.
المميّز الذي يحسم العلاج: ضغط الدم والضغط الوريدي الوداجي. فرط الحمل يترافق مع ارتفاع ضغط الدم وارتفاع الضغط الوريدي الوداجي ويستجيب للمدرّ؛ أمّا أذيّة الرئة فمع هبوط ضغط الدم وضغط وريدي وداجي طبيعي ولا تستجيب له. وإعطاء المدرّ في حالة TRALI هو الخطأ الذي وُجد هذا التمييز لمنعه.
MASSIVE TRANSFUSION — replacing a large proportion of the blood volume — brings its OWN problems.
نقل الدم الهائل — استبدال نسبة كبيرة من حجم الدم — يجلب مشكلاته الخاصّة.
HYPOTHERMIAfrom cold blood — and cold blood does not clotانخفاض حرارة الجسم — من الدم البارد، والدم البارد لا يتخثّر
HYPOCALCAEMIAfrom the CITRATE anticoagulant, which binds calciumنقص كالسيوم الدم — من السترات المانعة للتخثّر التي تربط الكالسيوم
HYPERKALAEMIAfrom potassium leaking out of stored cellsفرط بوتاسيوم الدم — من تسرّب البوتاسيوم من الخلايا المخزّنة
COAGULOPATHYfrom dilution of clotting factors and plateletsاعتلال التخثّر — من تخفيف عوامل التخثّر والصفيحات
Which is why massive transfusion is given in DEFINED RATIOS of red cells, plasma and platelets rather than red cells alone — and why the nursing is warming every unit and the patient, and monitoring calcium, potassium, temperature and clotting throughout. The lethal triad is hypothermia, acidosis and coagulopathy, and each one worsens the other two — which is why keeping him warm is a clotting intervention, not a comfort measure.
ولهذا يُعطى نقل الدم الهائل بنسب محدّدة من الكريّات والبلازما والصفيحات لا بالكريّات وحدها — ولهذا يتمثّل التمريض في تدفئة كلّ وحدة والمريض ومراقبة الكالسيوم والبوتاسيوم والحرارة والتخثّر طوال الوقت. والثلاثي المميت انخفاض الحرارة والحماض واعتلال التخثّر وكلّ منها يسوّئ الآخرين — ولهذا إبقاؤه دافئاً تدخّل تخثّري لا إجراء راحة.
🚩
Watch out
تنبيه
In any suspected transfusion reaction the first action is to stop the transfusion, then keep the line open with normal saline through a new giving set and notify.
في أيّ تفاعل نقل دم مشتبه يكون الإجراء الأول إيقاف نقل الدم ثم إبقاء الخطّ مفتوحاً بمحلول ملحي عادي عبر طقم جديد والإبلاغ.
🔑
Memory aid
مفتاح للحفظ
Overload gives crackles with a high blood pressure and raised neck veins. Lung injury gives crackles with a normal or low pressure and no fluid overload.
فرط الحمل يعطي خراخر مع ضغط مرتفع وأوردة عنق بارزة. والأذيّة الرئوية تعطي خراخر مع ضغط طبيعي أو منخفض ولا فرط في حجم السوائل.
24
8.23 · Special Components, Protocols and Documentation٨٫٢٣ · المكوّنات الخاصّة والبروتوكولات والتوثيق
Some patients need specially prepared components. Irradiated components have had donor lymphocytes inactivated to prevent transfusion-associated graft versus host disease, and are required for severely immunocompromised patients, certain transplant recipients and some congenital immunodeficiencies. Leucodepleted components have had white cells removed, which reduces febrile non-haemolytic reactions and the risk of transmitting cytomegalovirus. These special requirements must be communicated to the blood bank, because a standard unit given to a patient who needs an irradiated one can be fatal, and the requirement is recorded so it follows the patient.
بعض المرضى يحتاجون مكوّنات محضّرة خصيصاً. فالمكوّنات المشعّعة عُطّلت فيها لمفاويات المتبرّع لمنع داء الطعم ضدّ المضيف المرتبط بنقل الدم، وتلزم للمرضى شديدي كبت المناعة وبعض متلقّي الزرع وبعض حالات نقص المناعة الخلقي. والمكوّنات منزوعة الكريّات البيض أُزيلت منها الكريّات البيض، ما يقلّل التفاعلات الحموية غير الانحلالية وخطر نقل الفيروس المضخّم للخلايا. وهذه المتطلّبات الخاصّة يجب إبلاغها لبنك الدم، فالوحدة القياسية المعطاة لمريض يحتاج مشعّعة قد تكون مميتة، ويُسجَّل المتطلّب ليتبع المريض.
A MAJOR HAEMORRHAGE PROTOCOL is a pre-agreed pathway activated in massive bleeding, which releases blood components RAPIDLY in DEFINED RATIOS without waiting for individual requests.
بروتوكول النزف الكبير مسار متّفَق عليه مسبقاً يُفعَّل في نزف هائل ويُطلق مكوّنات الدم بسرعة وبنسب محدّدة دون انتظار طلبات فردية.
1
ACTIVATE it early
One call, with a defined phrase — and activating it and standing it down is far better than activating it late.
التفعيل المبكّر للبروتوكول — مكالمة واحدة بعبارة محدّدة، وتفعيله ثم إيقافه أفضل بكثير من تفعيله متأخّراً.
2
One person coordinates
A named runner, and a named person communicating with the laboratory — because in a massive haemorrhage the commonest failure is communication, not blood supply.
شخص واحد ينسّق — ساعٍ مسمّى وشخص مسمّى يتواصل مع المختبر، لأن أشيع إخفاق في النزف الكبير هو التواصل لا إمداد الدم.
3
Keep taking samples
Clotting, calcium, potassium and blood gas repeatedly — the picture changes fast.
الاستمرار في أخذ العيّنات — التخثّر والكالسيوم والبوتاسيوم وغازات الدم بشكل متكرّر، فالصورة تتغيّر بسرعة.
4
Warm everything
The blood, the fluids and the patient.
تدفئة كلّ شيء — الدم والسوائل والمريض.
5
And STAND IT DOWN when it is over
Explicitly — so components are not wasted and the laboratory is released.
وإيقاف التفعيل صراحةً حين ينتهي الأمر — كي لا تُهدَر المكوّنات ويتحرّر المختبر.
Anti-D immunoglobulin is given to a rhesus negative woman who may have been exposed to rhesus positive fetal blood — after delivery of a rhesus positive baby, and after any potentially sensitising event such as miscarriage, termination, antepartum bleeding, amniocentesis or abdominal trauma. It prevents her forming antibodies that would attack the red cells of a future rhesus positive baby, causing haemolytic disease of the newborn. It is preventive and time-critical, and it is covered further in Part 03.
الغلوبولين المناعي المضادّ للمستضد D يُعطى لامرأة سالبة الريصي قد تكون تعرّضت لدم جنيني موجب الريصي — بعد ولادة طفل موجب الريصي وبعد أيّ حدث محسّس محتمل كإجهاض أو إنهاء حمل أو نزف قبل الولادة أو بزل سلى أو رضّ بطني. وهو يمنعها من تكوين أضداد تهاجم كريّات طفل مستقبلي موجب الريصي فتسبّب الداء الانحلالي للوليد. وهو وقائي وحسّاس للوقت ويُغطّى أكثر في الجزء الثالث.
Finally, traceability. Every component must be traceable from donor to recipient, so the unit number, component type, date and time of transfusion and the outcome are documented, and the required part of the label or the electronic record is returned to the blood bank. This is not administrative box-ticking: if a donor is later found to have an infection, or a recipient develops a reaction, tracing every unit is how other patients are protected. Reactions are reported through the local haemovigilance system.
وأخيراً إمكانية التتبّع. فكلّ مكوّن يجب تتبّعه من المتبرّع للمتلقّي، فيُوثَّق رقم الوحدة ونوع المكوّن وتاريخ ووقت نقل الدم والنتيجة، ويُعاد الجزء المطلوب من الملصق أو السجلّ الإلكتروني لبنك الدم. وهذا ليس تأشيراً إدارياً على مربّعات: فإن تبيّن لاحقاً أن متبرّعاً مصاب بعدوى أو تطوّر لدى متلقٍّ تفاعل، فتتبّع كلّ وحدة هو ما يحمي المرضى الآخرين. وتُبلَّغ التفاعلات عبر نظام يقظة الدم المحلّي.
🚩
Watch out
تنبيه
Special requirements such as irradiated components must be communicated to the blood bank and recorded so they follow the patient. A standard unit given instead can be fatal.
المتطلّبات الخاصّة كالمكوّنات المشعّعة يجب إبلاغها لبنك الدم وتسجيلها لتتبع المريض. فالوحدة القياسية المعطاة بدلاً منها قد تكون مميتة.
25
8.24 · Platelets, Chemotherapy Support and Body Image٨٫٢٤ · الصفيحات ودعم العلاج الكيميائي وصورة الجسد
Plateletsالصُّفيحات الدمويةServier Medical Art · CC BY 4.0
🟡PLATELETS
Stored at ROOM TEMPERATURE with gentle continuous AGITATION
NOT refrigerated — refrigeration destroys them
Short shelf life, so they are a scarce resource
Given over a SHORTER time than red cells
Higher bacterial risk because of the storage temperature — so reactions are taken seriously
الصفيحات — تُخزَّن في درجة حرارة الغرفة مع رجّ لطيف مستمرّ: لا تُبرَّد، فالتبريد يتلفها. عمر رفّها قصير، لذا فهي مورد شحيح. وتُعطى خلال مدّة أقصر من الكريّات الحمر. وخطر العدوى الجرثومية فيها أعلى بسبب درجة حرارة التخزين، لذلك تؤخذ التفاعلات على محمل الجدّ.
🔴RED CELLS
Refrigerated, in controlled storage
Defined maximum time out of storage before it must be transfused or discarded
Longer infusion time
Never warmed except with a proper blood warmer
And never left on a ward bench to ‘come to room temperature’
الكريّات الحمراء — مبرَّدة في تخزين مضبوط؛ ولها حدّ أقصى محدّد للمدة خارج التخزين يجب بعدها نقلها أو إتلافها؛ ومدّة نقلها أطول؛ ولا تُدفَّأ إلا بمدفّئ دم مناسب؛ ولا تُترك أبداً على طاولة في الجناح كي «تصل إلى حرارة الغرفة».
1
ACUTE — within hours of the dose
Treated with antiemetics given BEFORE the chemotherapy.
حادّ — خلال ساعات من الجرعة: يُعالَج بمضادّات القيء المعطاة قبل العلاج الكيميائي.
2
DELAYED — after 24 hours, lasting days
Frequently under-treated, because he is at home by then — so he goes home with the antiemetics and instructions to take them regularly, not as required.
متأخّر — بعد ٢٤ ساعة ويدوم أياماً: كثيراً ما يُعالَج بأقلّ من اللازم لأن المريض يكون في المنزل حينها — لذا يغادر ومعه مضادّات القيء وتعليمات بتناولها بانتظام لا عند الحاجة.
3
ANTICIPATORY — BEFORE the next cycle
A learned response, triggered by the sight or smell of the hospital — and once established it is very difficult to treat.
استباقي — قبل الدورة التالية: استجابة متعلَّمة تُثيرها رؤية المستشفى أو رائحته، وبمجرّد ترسّخها يصعب علاجها كثيراً.
4
Which makes the message one line
PREVENTING the first episode is what prevents the anticipatory nausea — so the antiemetics are given properly from cycle one, not escalated after he has been sick.
ما يجعل الرسالة سطراً واحداً — منع النوبة الأولى هو ما يمنع الغثيان الاستباقي، لذا تُعطى مضادّات القيء بصورة صحيحة منذ الدورة الأولى بدلاً من تصعيدها بعد أن يتقيّأ المريض.
Fertility must be raised before treatment begins, not afterwards, because chemotherapy and radiotherapy can cause permanent infertility and the options — sperm banking, oocyte or embryo storage — require action beforehand. It is frequently omitted, particularly in younger patients and in the urgency of starting treatment, and its omission causes lasting grief. The conversation is handled sensitively and with awareness of what is culturally and religiously appropriate, and it is escalated to the treating team rather than left.
الخصوبة يجب طرحها قبل بدء العلاج لا بعده، فالعلاج الكيميائي والشعاعي قد يسبّبان عقماً دائماً والخيارات — حفظ النطاف أو تخزين البويضات أو الأجنّة — تتطلّب إجراءً مسبقاً. وكثيراً ما تُغفَل خاصّةً لدى المرضى الأصغر سنّاً وفي عجلة بدء العلاج، وإغفالها يسبّب حزناً باقياً. ويُدار الحديث بحسّاسية ووعي بما هو مناسب ثقافياً ودينياً ويُصعَّد للفريق المعالج لا يُترَك.
Body image changes after surgery and cancer treatment are REAL CLINICAL CONCERNS rather than vanity.A visible scar, a stoma, an amputation, weight change, hair loss or a mastectomy affect identity, relationships, work, prayer and how a person is seen by his own family.
تغيّرات صورة الجسد بعد الجراحة وعلاج السرطان شواغل سريرية حقيقية لا غرور. فندبة ظاهرة أو فغرة أو بتر أو تغيّر وزن أو فقد شعر أو استئصال ثدي تؤثّر على الهويّة والعلاقات والعمل والصلاة وكيف يراه أهله.
1
ASK, rather than waiting to be told
Nobody volunteers this — and a direct, ordinary question gives permission.
السؤال بدلاً من انتظار الإفصاح — فلا أحد يتطوّع بذلك، والسؤال المباشر العادي يمنح الإذن بالحديث.
2
Let him look when HE is ready
Not on a timetable, and be there when he does — the first time is the one that matters.
ترك المريض ينظر حين يكون هو مستعدّاً — لا وفق جدول زمني، مع الحضور إلى جانبه حين يفعل؛ فالمرّة الأولى هي الأهمّ.
3
Watch your own face
He is reading it — and a flicker of reaction is remembered for years.
الانتباه إلى تعابير وجه مقدّم الرعاية نفسه — فالمريض يقرؤها، وقد تبقى لمحة ردّ الفعل في الذاكرة سنوات.
4
Involve the partner or family carefully
Ask HIM who he wants present — and note that their reaction shapes his more than yours does.
إشراك الشريك أو الأسرة بعناية — يُسأل المريض عمّن يريد حضوره، ويُلاحَظ أن ردّ فعل أفراد الأسرة يشكّل ردّ فعله أكثر من ردّ فعل الطاقم.
5
And offer the practical
Stoma products and clothing, prosthesis fitting, scar management, wigs and head coverings — and refer for specialist support, because this is treatable and is not simply something to get used to.
وتقديم الدعم العملي — منتجات الفغرة والملابس، وتركيب الأطراف أو البدائل الصناعية، والعناية بالندبات، والباروكات وأغطية الرأس — مع الإحالة إلى دعم متخصّص، لأن هذا قابل للعلاج وليس مجرّد أمر ينبغي التعوّد عليه.
🚩
Watch out
تنبيه
Never put platelets in the ward refrigerator. They are stored at room temperature with agitation, have a short shelf life, and are used promptly.
لا تُوضَع الصفيحات في ثلّاجة الجناح أبداً. فهي تُخزَّن في حرارة الغرفة مع رجّ ولها عمر رفّ قصير وتُستخدَم فوراً.
⭐
Key point
نقطة أساسية
Antiemetics are given before chemotherapy, not after vomiting starts. Once vomiting is established it is much harder to control and it sets up anticipatory nausea.
مضادّات القيء تُعطى قبل العلاج الكيميائي لا بعد بدء التقيّؤ. فبمجرّد ترسّخه يصعب ضبطه كثيراً ويؤسّس الغثيان الاستباقي.
⭐
Key point
نقطة أساسية
Raise fertility before treatment begins. Afterwards it is too late, and the omission causes lasting grief.
يجب طرح موضوع الخصوبة قبل بدء العلاج. فبعده يكون قد فات الأوان، وإغفالها يسبّب حزناً باقياً.
26
8.25 · Blood Disorders in the Saudi Setting٨٫٢٥ · اضطرابات الدم في السياق السعودي
The National Premarital Screening Programme is the single most important piece of Saudi public health in this chapter and it is very frequently examined. It became mandatory in 2004 for couples intending to marry, and it screens for the two commonest inherited blood disorders in the Kingdom — sickle cell disease and beta thalassaemia — together with HIV and hepatitis B and C. Its purpose is not to prevent marriage but to identify at-risk couples and offer them genetic counselling so that the decision is informed; the couple then choose.
البرنامج الوطني للفحص قبل الزواج أهمّ معلومة صحّة عامّة سعودية في هذا الفصل ويُختبَر كثيراً جداً. وقد صار إلزامياً عام ٢٠٠٤ للمقبلين على الزواج، ويفحص أشيع اضطرابين دمويين موروثين في المملكة — داء الخلايا المنجلية وثلاسيميا بيتا — مع فيروس نقص المناعة البشرية والتهاب الكبد ب وج. وغرضه ليس منع الزواج بل تحديد الأزواج المعرّضين وعرض الاستشارة الوراثية عليهم ليكون القرار مستنيراً؛ ثم يختار الزوجان.
The national screening data explain why the programme exists. Of nearly half a million people screened in its early years, about 4% carried the sickle cell trait and about 3% the thalassaemia trait, with a smaller proportion having the disease itself. The distribution is markedly regional, concentrated in the eastern, western and southwestern parts of the country, with the Eastern Province carrying the heaviest burden. That regional pattern matters clinically: in those areas a nurse should expect to meet these conditions routinely rather than rarely.
بيانات المسح الوطني تفسّر سبب وجود البرنامج. فمن نحو نصف مليون شخص فُحصوا في سنواته الأولى حمل نحو ٤٪ سمة المنجلية ونحو ٣٪ سمة الثلاسيميا، مع نسبة أصغر لديها المرض نفسه. والتوزّع إقليمي بوضوح ويتركّز في الأجزاء الشرقية والغربية والجنوبية الغربية من البلاد، والمنطقة الشرقية تحمل أثقل عبء. وذلك النمط الإقليمي يهمّ سريرياً: ففي تلك المناطق ينبغي أن تتوقّع الممرضة مقابلة هذه الحالات روتينياً لا نادراً.
Consanguineous marriage is the reason these AUTOSOMAL RECESSIVE conditions cluster in families, and it raises the chance that both parents carry the same gene; the high local carrier rates of sickle cell disease, thalassaemia and G6PD deficiency (which is X-linked, not autosomal) mainly reflect past malaria selection.
زواج الأقارب سبب تجمّع هذه الحالات الجسمية المتنحّية في الأسر ويزيد احتمال حمل الوالدين الجين نفسه؛ أمّا ارتفاع نسب الحاملين للجين محلياً للداء المنجلي والثلاسيميا ونقص G6PD (المرتبط بالصبغي X وليس جسمياً) فيعود أساساً إلى الانتقاء التاريخي بفعل الملاريا.
•What that changes for a nurse here◆ ما الذي يغيّره ذلك بالنسبة للعاملين في التمريض هنا
The family history includes whether the parents are RELATEDAsked routinely — and a positive answer reframes an unexplained anaemia, jaundice or recurrent infection.القصّة العائلية تشمل ما إذا كان الوالدان أقارب — ويُسأل عن ذلك روتينياً، والإجابة الإيجابية تعيد تفسير فقر الدم غير المفسَّر أو اليرقان أو العدوى المتكرّرة.
The PREMARITAL SCREENING programme exists precisely for thisMandatory since 2004 for sickle cell and thalassaemia, later expanded — and a carrier result identified before marriage is useless if it is not in the notes years later. So ask about it, and record it.برنامج الفحص قبل الزواج موجود لهذا بالضبط — إلزامي منذ ٢٠٠٤ للمنجلية والثلاسيميا ثم وُسِّع لاحقاً؛ ونتيجة حمل السمة المكتشفة قبل الزواج لا فائدة منها إذا لم تكن مدوَّنة في السجلّ بعد سنوات. لذلك يُسأل عنها وتُسجَّل.
And CASCADE testing for the familyA diagnosis in one child is a question about siblings and cousins — which is how a programme reaches the people who never attended.والفحص المتتالي للأسرة — فتشخيص طفل واحد يعني السؤال عن أشقّائه وأبناء عمومته، وبهذه الطريقة يصل البرنامج إلى من لم يحضروا قطّ.
Plus the G6PD point that is specific to hereThe prevalence is high enough that the trigger list matters to every nurse, not only to a specialist — and fava beans, mothballs and certain drugs are ordinary things in an ordinary household.مع نقطة G6PD الخاصّة بهذه البيئة — فالانتشار عالٍ بما يكفي لأن تهمّ قائمة المحفّزات كلّ العاملين في التمريض لا المتخصّص وحده؛ فالفول وكرات النفتالين وبعض الأدوية أمور عادية في أيّ بيت.
•Two further practical points◆ نقطتان عمليتان إضافيتان
Blood SUPPLY depends on voluntary donorsAnd patients with thalassaemia and sickle cell disease consume a substantial share of it — which is why patient blood management, restrictive thresholds and avoiding unnecessary transfusion are not abstractions here. A unit not given to one patient is a unit available to another.إمداد الدم يعتمد على متبرّعين متطوّعين — ومرضى الثلاسيميا والمنجلية يستهلكون حصّةً كبيرة منه، ولهذا فإن تدبير دم المريض والعتبات التقييدية وتجنّب نقل الدم غير الضروري ليست مفاهيم نظرية هنا؛ فالوحدة التي لا تُعطى لمريض هي وحدة متاحة لمريض آخر.
And religious observance around transfusion and surgeryBlood transfusion is permitted in mainstream Islamic scholarship, and saying so plainly resolves a hesitation some families hold. Ramadan raises the practical questions covered elsewhere — and elective surgery timing, fasting, and medication schedules are discussed BEFORE Ramadan, not negotiated during it.والالتزام الديني حول نقل الدم والجراحة — نقل الدم مباح في الفقه السائد، والتصريح بذلك بوضوح يزيل تردّداً لدى بعض الأسر. ويثير رمضان أسئلة عملية جرت معالجتها في موضع آخر — ويُبحث توقيت الجراحة الاختيارية والصيام وجداول الأدوية قبل رمضان، لا أن يُتفاوض عليها خلاله.
Plus the modesty and family points that run through this bookFemale staff where requested, privacy during examination and transfer, and the family present and informed — which are practical arrangements, not concessions.مع نقاط الحشمة والأسرة التي تتخلّل هذا الكتاب — طاقم نسائي عند الطلب، وخصوصية أثناء الفحص والنقل، ووجود الأسرة وإبلاغها؛ وهذه ترتيبات عملية وليست تنازلات.
⭐
Key point
نقطة أساسية
The premarital screening programme became mandatory in 2004 and screens for sickle cell disease and thalassaemia alongside HIV and hepatitis B and C. Its purpose is informed choice through genetic counselling, not preventing marriage.
برنامج الفحص قبل الزواج صار إلزامياً عام ٢٠٠٤ ويفحص المنجلية والثلاسيميا مع فيروس نقص المناعة البشرية والتهاب الكبد ب وج. وغرضه الاختيار المستنير بالاستشارة الوراثية لا منع الزواج.
⭐
Key point
نقطة أساسية
Sickle cell and thalassaemia cluster in the eastern, western and southwestern regions. In those areas expect to meet them routinely.
المنجلية والثلاسيميا تتجمّعان في المناطق الشرقية والغربية والجنوبية الغربية. وفي تلك المناطق ينبغي توقّع مقابلتهما روتينياً.
Test yourselfالاختبار الذاتي
Loading… جارٍ التحميل…
Loading… جارٍ التحميل…
Loading… جارٍ التحميل…
Medical disclaimer. The content of this platform is for education and exam preparation only. It is not medical advice and does not replace consultation with a qualified physician or other licensed healthcare professional, or current clinical guidelines. Do not use it to diagnose or treat any person.
إخلاء المسؤولية الطبية: محتوى هذه المنصة مخصص للتعليم والتحضير للاختبار فقط، وليس نصيحة طبية، ولا يغني عن استشارة الطبيب المختص أو الممارس الصحي المرخّص، ولا عن الإرشادات السريرية الحالية. ولا يجوز استخدامه لتشخيص أي شخص أو علاجه.