
Gastrointestinal & Liver Nursing
In this chapterفي هذا الفصل
Key terms (11)المصطلحات الأساسية
Chapter outline (28 sections)مخطط الفصل
- Learning Objectivesأهداف التعلّم
- 5.1 · Assessing the Abdomen٥٫١ · تقييم البطن
- 5.2 · Stools, Vomit and What They Tell You٥٫٢ · البراز والقيء وما يدلّان عليه
- 5.3 · Gastrointestinal Investigations٥٫٣ · فحوصات الجهاز الهضمي
- 5.4 · Reflux and the Oesophagus٥٫٤ · الارتجاع والمريء
- 5.5 · Swallowing, the Mouth and the Oesophagus٥٫٥ · البلع والفم والمريء
- 5.6 · Peptic Ulcer Disease٥٫٦ · داء القرحة الهضمية
- 5.7 · Upper Gastrointestinal Bleeding and Varices٥٫٧ · النزف الهضمي العلوي والدوالي
- 5.8 · After Gastric Surgery: Dumping Syndrome٥٫٨ · بعد جراحة المعدة: متلازمة الإغراق
- 5.9 · Inflammatory Bowel Disease٥٫٩ · داء الأمعاء الالتهابي
- 5.10 · Coeliac Disease, IBS and Diverticular Disease٥٫١٠ · الداء البطني والقولون المتهيّج وداء الرتوج
- 5.11 · Appendicitis and Bowel Obstruction٥٫١١ · التهاب الزائدة وانسداد الأمعاء
- 5.12 · Colorectal Disease and Stomas٥٫١٢ · أمراض القولون والمستقيم والفغرات
- 5.13 · Anorectal Conditions and Gut Infections٥٫١٣ · حالات الشرج والمستقيم وعدوى الأمعاء
- 5.14 · Hepatitis٥٫١٤ · التهاب الكبد
- 5.15 · Cirrhosis and Portal Hypertension٥٫١٥ · التليف وارتفاع الضغط البابي
- 5.16 · Hepatic Encephalopathy٥٫١٦ · اعتلال الدماغ الكبدي
- 5.17 · Gallbladder and Biliary Disease٥٫١٧ · أمراض المرارة والقنوات الصفراوية
- 5.18 · Pancreatitis٥٫١٨ · التهاب البنكرياس
- 5.19 · Gastrointestinal Cancer and Major Surgery٥٫١٩ · سرطان الجهاز الهضمي والجراحة الكبرى
- 5.20 · Tubes, Drains and Abdominal Surgery٥٫٢٠ · الأنابيب والمنازح وجراحة البطن
- 5.21 · Nutrition in Gastrointestinal Disease٥٫٢١ · التغذية في المرض الهضمي
- 5.22 · Gastrointestinal Emergencies٥٫٢٢ · الطوارئ الهضمية
- 5.23 · Gastrointestinal Drugs٥٫٢٣ · الأدوية الهضمية
- 5.24 · Antiemetics and Other Gut Drugs٥٫٢٤ · مضادّات القيء وأدوية هضمية أخرى
- 5.25 · Living With Gastrointestinal Disease٥٫٢٥ · التعايش مع المرض الهضمي
- 5.26 · Gastrointestinal Health in the Saudi Setting٥٫٢٦ · الصحّة الهضمية في السياق السعودي
- 5.27 · Zoonotic and Regional Infections٥٫٢٧ · العدوى الحيوانية المنشأ والإقليمية
Start learningبدء التعلّم Learning objectivesأهداف التعلّم Test yourselfالاختبار الذاتي
Learning Objectivesأهداف التعلّم
5.1 · Assessing the Abdomen٥٫١ · تقييم البطن
The order is different from every other system and it is examined for that reason: inspect, auscultate, percuss, then palpate. Auscultation comes before palpation because pressing on the abdomen alters bowel sounds, so palpating first gives a false reading.
الترتيب يختلف عن كلّ جهاز آخر ولهذا السبب يُختبَر: النظر ثم الإصغاء ثم القرع ثم الجسّ. فالإصغاء يأتي قبل الجسّ لأن الضغط على البطن يغيّر أصوات الأمعاء، فالجسّ أولاً يعطي قراءة كاذبة.
Bowel sounds: normal sounds are irregular gurgles every few seconds. Hyperactive, loud and rushing sounds occur in gastroenteritis and in early mechanical obstruction as the bowel fights to push past the blockage. Hypoactive or absent sounds occur in paralytic ileus, peritonitis and late obstruction — and before recording sounds as absent, listen over one quadrant for a full five minutes, because declaring them absent after thirty seconds is a common error.
أصوات الأمعاء: الطبيعية قرقرات غير منتظمة كلّ بضع ثوانٍ. والمفرطة النشاط العالية المندفعة تحدث في التهاب المعدة والأمعاء وفي الانسداد الميكانيكي المبكّر مع كفاح الأمعاء للدفع عبر السدّ. والناقصة أو الغائبة تحدث في العلوص الشللي والتهاب البريتون والانسداد المتأخّر — وقبل تسجيل الأصوات كغائبة، يجب الإصغاء فوق ربع واحد خمس دقائق كاملة، فإعلان غيابها بعد ثلاثين ثانية خطأ شائع.
On palpation, guarding is voluntary or involuntary tensing; rebound tenderness — pain worse on releasing the hand than on pressing — indicates peritoneal irritation; and a board-like rigid abdomen is the sign of perforation and peritonitis. Named signs worth knowing: Murphy's sign, arrest of inspiration on pressing the right upper quadrant, suggesting cholecystitis; McBurney's point tenderness in the right lower quadrant, suggesting appendicitis; and Rovsing's sign, where pressing the left lower quadrant produces pain in the right.
في الجسّ، التحارس شدّ إرادي أو لاإرادي؛ والإيلام الارتدادي — ألم أشدّ عند رفع اليد منه عند الضغط — يدلّ على تهيّج بريتوني؛ والبطن الصلب كاللوح علامة الانثقاب والتهاب البريتون. والعلامات المسمّاة الجديرة بالمعرفة: علامة مورفي، أي توقّف الشهيق عند الضغط على الربع العلوي الأيمن، وتوحي بالتهاب المرارة؛ وإيلام نقطة ماكبرني في الربع السفلي الأيمن، ويوحي بالتهاب الزائدة؛ وعلامة روفسينغ حيث يُنتج الضغط على الربع السفلي الأيسر ألماً في الأيمن.
Two bruising signs indicate retroperitoneal haemorrhage and mark severe pancreatitis: Cullen's sign, bruising around the umbilicus, and Grey Turner's sign, bruising in the flanks. For ascites, look for shifting dullness and a fluid thrill, and measure the abdominal girth at a marked point, at the same time each day, after voiding, so the measurements are comparable.
علامتا كدم تدلّان على نزف خلف الصفاق وتُميّزان التهاب البنكرياس الشديد: علامة كولن، أي كدم حول السرّة، وعلامة غراي تيرنر، أي كدم في الخاصرتين. وللاستسقاء يُبحَث عن البلادة المتنقّلة وموجة السائل، ويُقاس محيط البطن عند نقطة معلَّمة في الوقت نفسه كلّ يوم بعد التبوّل، لتكون القياسات قابلة للمقارنة.
5.2 · Stools, Vomit and What They Tell You٥٫٢ · البراز والقيء وما يدلّان عليه
Coffee-ground vomit is blood that has been in the stomach long enough for acid to alter it, so it indicates an upper gastrointestinal bleed. Fresh bright red haematemesis means brisk bleeding above the stomach or a large volume — classically oesophageal varices.
القيء بلون تفل القهوة دم بقي في المعدة مدّةً كافية ليغيّره الحمض، فيدلّ على نزف هضمي علوي. والقيء الدموي الأحمر الفاتح الطازج يعني نزفاً غزيراً فوق المعدة أو حجماً كبيراً — وكلاسيكياً دوالي المريء.
Melaena is black, tarry, sticky and characteristically offensive stool, and it is digested blood from an upper gastrointestinal bleed — the black colour comes from the blood passing through the gut. It is not the same as the harmless black stool caused by iron tablets or bismuth, which is not tarry and not offensive, so ask what the patient is taking before assuming a bleed.
البراز الزفتي براز أسود قطراني لزج كريه الرائحة بشكل مميّز، وهو دم مهضوم من نزف هضمي علوي — واللون الأسود من مرور الدم عبر الأمعاء. وهو ليس البراز الأسود غير الضارّ الذي تسبّبه أقراص الحديد أو البزموت، فذلك ليس قطرانياً ولا كريهاً، فيجب سؤال المريض عمّا يتناوله قبل افتراض وجود نزف.
Fresh red blood passed rectally suggests a lower gastrointestinal source — haemorrhoids, fissure, diverticular disease, inflammatory bowel disease or malignancy — although a very brisk upper bleed can also present this way. Pale, bulky, greasy stool that floats and is difficult to flush is steatorrhoea, indicating fat malabsorption, as in chronic pancreatitis or coeliac disease. Pale clay-coloured stool with dark urine points to obstructive jaundice.
الدم الأحمر الطازج من المستقيم يوحي بمصدر هضمي سفلي — بواسير أو شقّ أو داء رتوج أو داء أمعاء التهابي أو خباثة — وإن كان النزف العلوي الغزير جداً قد يتظاهر هكذا أيضاً. والبراز الشاحب الضخم الدهني الذي يطفو ويصعب شطفه إسهال دهني يدلّ على سوء امتصاص الدهن كما في التهاب البنكرياس المزمن أو الداء البطني. والبراز الشاحب بلون الطين مع بول داكن يشير إلى يرقان انسدادي.
5.3 · Gastrointestinal Investigations٥٫٣ · فحوصات الجهاز الهضمي
Upper endoscopy: fasting beforehand, dentures out, consent confirmed. Afterwards the throat has been anaesthetised, so the patient is nil by mouth until the gag reflex returns — the same rule as after bronchoscopy in Chapter 02, and for the same reason. Watch for the complication that matters: perforation, which presents with pain, fever, bleeding, difficulty swallowing or subcutaneous emphysema in the neck.
التنظير العلوي: صيام مسبق ونزع أطقم الأسنان وتأكيد الموافقة. وبعده يكون الحلق قد خُدِّر، فيبقى المريض صائماً حتى يعود منعكس التهوّع — وهي القاعدة نفسها كبعد تنظير القصبات في الفصل الثاني وللسبب نفسه. وتجب مراقبة المضاعفة التي تهمّ: الانثقاب ويتظاهر بألم وحمّى ونزف وصعوبة بلع أو نفاخ تحت الجلد في العنق.
Colonoscopy needs bowel preparation, which is the part patients find hardest — explain it properly, since an inadequate preparation means a repeat procedure. Afterwards, flatus and mild cramping are expected from the air insufflated; severe pain, abdominal distension, fever or significant bleeding are not and suggest perforation. ERCP examines the biliary tree, and its characteristic complication is post-ERCP pancreatitis, so watch for abdominal pain radiating to the back with a rising amylase or lipase.
تنظير القولون يحتاج تحضير أمعاء وهو الجزء الأصعب على المرضى — ويجب شرحه كما ينبغي، فالتحضير غير الكافي يعني إعادة الإجراء. وبعده الريح والمغص الخفيف متوقّعان من الهواء المنفوخ؛ أما الألم الشديد وانتفاخ البطن والحمّى والنزف الملحوظ فليست متوقّعة، بل توحي بانثقاب. وتصوير القنوات الصفراوية والبنكرياسية بالتنظير يفحص الشجرة الصفراوية، ومضاعفته المميّزة التهاب البنكرياس بعده، فتجب مراقبة ألم بطني ينتشر للظهر مع ارتفاع الأميلاز أو الليباز.
Liver blood tests divide into two groups that answer different questions. ALT and AST rise with hepatocellular damage; alkaline phosphatase and GGT rise with cholestasis — obstruction of bile flow. But neither measures how well the liver is working. That is shown by albumin, which falls in chronic liver disease because the liver makes it, and by the prothrombin time or INR, which rises acutely because clotting factors are made in the liver and have a short half-life. Lipase is more specific to the pancreas than amylase.
تحاليل الكبد تنقسم لمجموعتين تجيبان أسئلة مختلفة. فـALT وAST يرتفعان مع تلف الخلايا الكبدية؛ والفوسفاتاز القلوية وGGT يرتفعان مع الركود الصفراوي أي انسداد جريان الصفراء. لكن أياً منهما لا يقيس مدى عمل الكبد. وذلك يُظهره الألبومين الذي ينخفض في مرض الكبد المزمن لأن الكبد يصنعه، وزمن البروثرومبين أو النسبة المعيارية الدولية (INR) الذي يرتفع بصورة حادّة لأن عوامل التخثّر تُصنَع في الكبد وعمر نصفها قصير. والليباز أكثر نوعيةً للبنكرياس من الأميلاز.
5.4 · Reflux and the Oesophagus٥٫٤ · الارتجاع والمريء
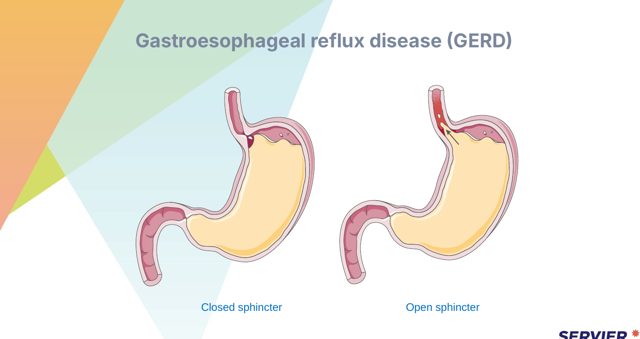
Gastro-oesophageal reflux gives burning retrosternal discomfort, an acid or bitter taste, and regurgitation, characteristically worse lying flat, bending forward and after large meals. It can also present atypically as a chronic cough, hoarseness or a sensation of a lump in the throat.
الارتجاع المعدي المريئي يسبب انزعاجاً حارقاً خلف القصّ وطعماً حامضاً أو مرّاً وقلساً، وتكون بصورة مميّزة أسوأ عند الاستلقاء المسطّح والانحناء للأمام وبعد الوجبات الكبيرة. وقد يتظاهر بصورة غير نمطية بسعال مزمن أو بحّة أو إحساس بكتلة في الحلق.
Long-standing reflux can produce Barrett's oesophagus, in which the normal lining is replaced by a different type of cell. It matters because it carries an increased risk of oesophageal adenocarcinoma, so these patients enter endoscopic surveillance. A hiatus hernia, where part of the stomach moves above the diaphragm, contributes to reflux and is managed the same way.
الارتجاع المزمن قد يُنتج مريء باريت حيث تُستبدَل البطانة الطبيعية بنوع خلايا مختلف. وهو يهمّ لأنه يحمل خطراً متزايداً لسرطان المريء الغدّي، فيخضع هؤلاء المرضى للمراقبة التنظيرية. والفتق الحجابي حيث ينتقل جزء من المعدة فوق الحجاب يسهم في الارتجاع ويُدبَّر بالطريقة نفسها.
5.5 · Swallowing, the Mouth and the Oesophagus٥٫٥ · البلع والفم والمريء
Dysphagia is difficulty swallowing and it is a red flag: new, progressive dysphagia — particularly to solids first and then liquids, with weight loss — suggests an obstructing lesion and is investigated urgently. Dysphagia to both solids and liquids from the outset points instead to a motility disorder. The immediate nursing concern is aspiration, so a patient with suspected dysphagia is kept nil by mouth until a swallow assessment has been done, as Part 01 Chapter 07 sets out, and referred to speech and language therapy.
عسر البلع صعوبة في البلع وهو علامة إنذار: فعسر البلع الجديد التقدّمي — خاصّةً للصلب أولاً ثم السائل مع نقص وزن — يوحي بآفة سادّة ويُستقصى عاجلاً. أما عسر البلع للصلب والسائل معاً من البداية فيشير لاضطراب حركية. والشاغل التمريضي الفوري هو الاستنشاق، فالمريض بعسر بلع مشتبه يبقى صائماً حتى يُجرى تقييم بلع كما يبيّن الفصل السابع من الجزء الأول، ويُحال إلى علاج النطق واللغة.
Achalasia is failure of the lower oesophageal sphincter to relax, so food is held above it. It gives dysphagia to solids and liquids equally, regurgitation of undigested food — often at night, with a risk of aspiration — chest discomfort and weight loss. Treatment is endoscopic dilation, botulinum injection or surgical myotomy, and patients are advised to eat slowly, chew thoroughly, drink with meals and avoid lying flat afterwards.
تعذّر الارتخاء المريئي فشل المصرّة المريئية السفلية في الارتخاء، فيُحتبَس الطعام فوقها. ويعطي عسر بلع للصلب والسائل بالتساوي وقلساً لطعام غير مهضوم — ليلاً غالباً مع خطر الاستنشاق — وانزعاجاً صدرياً ونقص وزن. والعلاج توسيع بالتنظير أو حقن بوتولينوم أو بضع عضلي جراحي، ويُنصَح المرضى بالأكل ببطء والمضغ جيّداً والشرب مع الوجبات وتجنّب الاستلقاء المسطّح بعدها.
ORAL CANDIDIASIS — white plaques on the tongue and buccal mucosa that leave a RAW SURFACE when wiped — occurs in the immunosuppressed, in diabetes, after antibiotics, in denture wearers, and in anyone using an INHALED CORTICOSTEROID.
داء المبيضات الفموي — لويحات بيضاء على اللسان والغشاء المخاطي الشدقي تترك سطحاً أحمر متسحّجاً عند مسحها — يحدث لدى مثبَّطي المناعة ومرضى السكّري وبعد المضادات الحيوية ولدى لابسي أطقم الأسنان ولدى كلّ من يستخدم ستيرويداً قشرياً مستنشَقاً.
5.6 · Peptic Ulcer Disease٥٫٦ · داء القرحة الهضمية
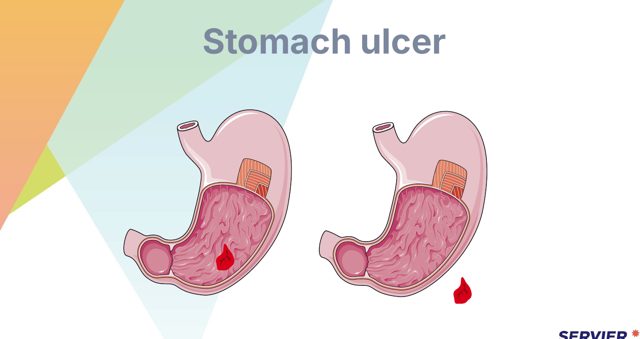
The pain pattern distinguishes the two, and it is asked in almost every paper. A gastric ulcer hurts soon after eating — within about thirty minutes to an hour — so food makes it worse, the patient avoids eating and tends to lose weight. A duodenal ulcer hurts two to three hours after eating and at night, when the stomach is empty, and is relieved by eating or by antacids — so the patient eats more and the weight is stable or rises.
نمط الألم يميّز بينهما، ويُسأل عنه في كلّ امتحان تقريباً. فالقرحة المعدية تؤلم بعيد الأكل — خلال نحو ثلاثين دقيقة إلى ساعة — فالطعام يزيدها سوءاً، ويتجنّب المريض الأكل ويميل لفقد الوزن. والقرحة الاثنا عشرية تؤلم بعد ساعتين إلى ثلاث من الأكل وليلاً حين تفرغ المعدة، وتزول بالأكل أو بمضادّات الحموضة — فيأكل المريض أكثر ويستقرّ وزنه أو يزيد.
The two dominant causes are Helicobacter pylori and non-steroidal anti-inflammatory drugs, with corticosteroids and smoking adding to the risk. Eradication of H. pylori is a combination regimen — a proton pump inhibitor with two antibiotics for a set course. The teaching point is completing the whole course: patients feel better within days and stop, and incomplete treatment fails to eradicate the organism and encourages resistance.
السببان المهيمنان الملوية البوابية ومضادّات الالتهاب غير الستيرويدية، مع إضافة الستيرويدات القشرية والتدخين للخطر. واستئصال الملوية نظام مركّب — مثبّط مضخّة بروتون مع مضادّين حيويين لدورة محدّدة. ونقطة التعليم إكمال الدورة كاملةً: فالمرضى يتحسّنون خلال أيام فيتوقّفون، والعلاج غير الكامل يفشل في استئصال الكائن ويشجّع المقاومة.
Three complications matter. Bleeding — presenting as haematemesis, coffee grounds or melaena. Obstruction at the gastric outlet — vomiting of undigested food, fullness, weight loss. And perforation, which is the emergency: sudden severe abdominal pain, a board-like rigid abdomen, absent bowel sounds, and a patient who lies completely still because any movement hurts. Perforation is managed as a surgical emergency: nil by mouth, notify immediately, intravenous access and fluids, analgesia, and preparation for theatre.
ثلاث مضاعفات تهمّ. النزف — ويتظاهر بقيء دموي أو تفل قهوة أو براز زفتي. والانسداد عند مخرج المعدة — تقيّؤ طعام غير مهضوم وامتلاء ونقص وزن. والانثقاب وهو الطارئ: ألم بطني شديد مفاجئ وبطن صلب كاللوح وغياب أصوات الأمعاء ومريض يستلقي ساكناً تماماً لأن أيّ حركة تؤلم. ويُدبَّر الانثقاب كطارئ جراحي: صيام وإبلاغ فوري ومدخل وريدي وسوائل ومسكّن وتحضير للعمليات.
5.7 · Upper Gastrointestinal Bleeding and Varices٥٫٧ · النزف الهضمي العلوي والدوالي
An upper gastrointestinal bleed presents with haematemesis, coffee-ground vomit or melaena, and the patient may be tachycardic, hypotensive, pale, cold and restless — remembering from Chapter 01 that restlessness is an early sign of hypovolaemia, not anxiety. The priorities are airway first, because a patient vomiting blood can aspirate, then two large-bore intravenous cannulae, bloods including crossmatch, fluid resuscitation and blood as prescribed, continuous monitoring and strict output measurement.
النزف الهضمي العلوي يتظاهر بقيء دموي أو بلون تفل القهوة أو براز زفتي، وقد يكون المريض متسرّع النبض هابط الضغط شاحباً بارداً متململاً — مع التذكير بما ورد في الفصل الأول من أن التململ علامة مبكّرة لنقص الحجم لا قلق. والأولويات مجرى الهواء أولاً، فالمريض الذي يتقيّأ دماً قد يستنشقه، ثم قنيتان وريديتان واسعتان، وتحاليل تشمل مطابقة الزمر، وإنعاش بالسوائل ودم كما يُوصَف، ومراقبة مستمرّة وقياس صادر دقيق.
Oesophageal varices are dilated veins that form when portal hypertension from cirrhosis forces blood through collateral channels. They bleed torrentially and are the cause of massive bright red haematemesis. The airway priority is even more pressing here, and the patient is often coagulopathic from the liver disease, so the bleeding is harder to stop.
دوالي المريء أوردة متوسّعة تتشكّل حين يدفع ارتفاع الضغط البابي من التليف الدم عبر قنوات جانبية. وهي تنزف بغزارة وهي سبب القيء الدموي الأحمر الفاتح الهائل. وأولوية مجرى الهواء أشدّ إلحاحاً هنا، والمريض مضطرب التخثّر غالباً من مرض الكبد، فيصعب إيقاف النزف.
Management: resuscitate, then endoscopic band ligation as the definitive treatment, with vasoactive drugs such as terlipressin or octreotide to reduce portal pressure, and antibiotics, which improve outcomes in a bleeding cirrhotic. Balloon tamponade is a temporary measure only, used to buy time until endoscopy, and it carries real risks. Afterwards, beta-blockade is used to reduce the risk of rebleeding.
التدبير: إنعاش، ثم ربط الدوالي بالتنظير كعلاج نهائي، مع أدوية فعّالة وعائياً كالتيرليبريسين أو الأوكتريوتيد لتقليل الضغط البابي، ومضادات حيوية تحسّن النتائج لدى مرضى التليف مع النزيف. والسدّ بالبالون تدبير مؤقّت فقط يُستخدَم لكسب وقت حتى التنظير، وهو يحمل مخاطر حقيقية. وبعدها يُستخدَم حصر بيتا لتقليل خطر إعادة النزف.
5.8 · After Gastric Surgery: Dumping Syndrome٥٫٨ · بعد جراحة المعدة: متلازمة الإغراق
When part of the stomach has been removed or bypassed — including after bariatric surgery, which is increasingly common — food can pass into the small bowel too quickly. The rapid arrival of a concentrated load draws fluid into the gut and triggers a hormonal response.
حين يُزال جزء من المعدة أو يُتجاوَز — بما في ذلك بعد جراحة السمنة المتزايدة الشيوع — قد يمرّ الطعام للأمعاء الدقيقة بسرعة مفرطة. فالوصول السريع لحمل مركّز يسحب السوائل للأمعاء ويُطلق استجابة هرمونية.
Early dumping, within about thirty minutes of eating, gives cramping abdominal pain, nausea, diarrhoea, dizziness, sweating, palpitations and a feeling of faintness. Late dumping, one to three hours after eating, is a reactive hypoglycaemia and gives sweating, tremor, hunger and confusion — the picture described in Chapter 03.
الإغراق المبكّر، خلال نحو ثلاثين دقيقة من الأكل، يعطي ألماً بطنياً مغصياً وغثياناً وإسهالاً ودوخة وتعرّقاً وخفقاناً وإحساساً بالإغماء. والإغراق المتأخّر، بعد ساعة إلى ثلاث من الأكل، نقص سكّر ارتكاسي ويعطي تعرّقاً ورعاشاً وجوعاً وتشوّشاً — وهي الصورة الموصوفة في الفصل الثالث.
The dietary advice is specific and is the answer in the exam: small, frequent, dry meals; take fluids between meals rather than with them, because liquid with food speeds gastric emptying; reduce simple sugars and increase protein and fat; and lie down or recline for about half an hour after eating, which slows emptying using gravity. It usually improves over months as the gut adapts.
النصيحة الغذائية محدّدة وهي الجواب في الامتحان: وجبات صغيرة متكرّرة جافّة؛ وتناول السوائل بين الوجبات لا معها، فالسائل مع الطعام يسرّع إفراغ المعدة؛ وتقليل السكّريات البسيطة وزيادة البروتين والدهن؛ والاستلقاء أو الاتّكاء نحو نصف ساعة بعد الأكل، ما يبطئ الإفراغ مستعيناً بالجاذبية. وتتحسّن عادةً عبر أشهر مع تكيّف الأمعاء.
5.9 · Inflammatory Bowel Disease٥٫٩ · داء الأمعاء الالتهابي
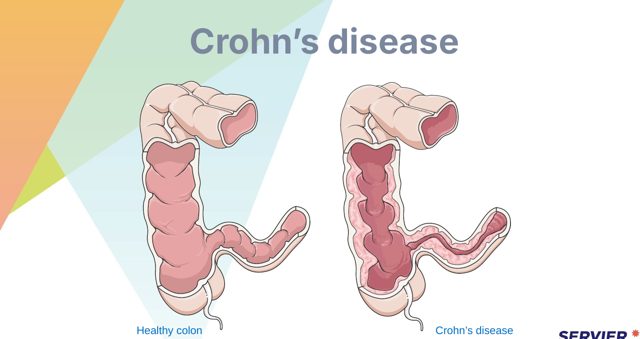
Ulcerative colitis is continuous inflammation limited to the mucosa, beginning at the rectum and extending proximally without skipping. Its characteristic presentation is frequent bloody diarrhoea with mucus, urgency and tenesmus, with lower abdominal cramping relieved by defaecation.
التهاب القولون التقرّحي التهاب متّصل محدود بالمخاطية، يبدأ من المستقيم ويمتدّ صعوداً دون تخطٍّ. وتظاهره المميّز إسهال دموي متكرّر مع مخاط وإلحاح وزحير، مع مغص بطني سفلي يزول بالتغوّط.
Crohn disease can affect anywhere from mouth to anus, is patchy with skip lesions, and involves the full thickness of the bowel wall. That transmural depth is why Crohn produces fistulae, abscesses, strictures and perianal disease, which ulcerative colitis does not. It presents with abdominal pain, often right lower quadrant, diarrhoea that is less often bloody, weight loss and malabsorption.
داء كرون قد يصيب أيّ مكان من الفم للشرج، وهو مرقّع بآفات متخطّية، ويشمل كامل سماكة جدار الأمعاء. وذلك العمق عبر الجدار هو سبب إنتاج كرون نواسير وخرّاجات وتضيّقات ومرضاً حول الشرج، وهو ما لا يفعله التهاب القولون التقرّحي. ويتظاهر بألم بطني في الربع السفلي الأيمن غالباً وإسهال أقلّ دموية ونقص وزن وسوء امتصاص.
Toxic megacolon is the emergency of ulcerative colitis: the colon dilates and stops moving, and it can perforate. The signs are abdominal distension with a tender abdomen, fever, tachycardia, and a sudden reduction in the number of stools in a patient who was passing many — which looks like improvement and is not. Bowel sounds become absent. It is reported urgently.
تضخّم القولون السمّي هو طارئ التهاب القولون التقرّحي: فيتوسّع القولون ويتوقّف عن الحركة وقد ينثقب. والعلامات انتفاخ بطني مع بطن مؤلم وحمّى وتسرّع نبض وانخفاض مفاجئ في عدد البرازات لدى مريض كان يُخرج كثيراً — ويبدو ذلك تحسّناً وليس كذلك. وتغيب أصوات الأمعاء. ويُبلَّغ عاجلاً.
Treatment uses aminosalicylates for maintenance in colitis, corticosteroids for flares — short courses, never stopped abruptly as Chapter 03 sets out — immunomodulators and biologics, which suppress immunity and therefore raise infection risk and require screening for tuberculosis and hepatitis before starting. Nursing care covers nutrition, fluid and electrolyte balance, skin care around a sore perianal area, and the psychological burden of a relapsing disease in a young person.
العلاج يستخدم الأمينوساليسيلات للعلاج المداوم في التهاب القولون، والستيرويدات القشرية للهجمات — دورات قصيرة لا تُوقَف فجأةً كما يبيّن الفصل الثالث — ومُعدّلات المناعة والبيولوجيات التي تكبت المناعة فترفع خطر العدوى وتتطلّب مسحاً للسلّ والتهاب الكبد قبل البدء. والرعاية التمريضية تغطّي التغذية وميزان السوائل والشوارد والعناية بالجلد في المنطقة المؤلمة حول الشرج والعبء النفسي لمرض ناكس لدى شابّ.
5.10 · Coeliac Disease, IBS and Diverticular Disease٥٫١٠ · الداء البطني والقولون المتهيّج وداء الرتوج
COELIAC DISEASE is an immune reaction to GLUTEN — found in WHEAT, BARLEY and RYE — which damages the small bowel lining and causes MALABSORPTION: diarrhoea, steatorrhoea, weight loss, bloating, fatigue, iron or folate deficiency anaemia, and in children faltering growth.
الداء البطني تفاعل مناعي مع الغلوتين — في القمح والشعير والجاودار — يُتلف بطانة الأمعاء الدقيقة ويسبّب سوء امتصاص: إسهالاً وإسهالاً دهنياً ونقص وزن وانتفاخاً وتعباً وفقر دم بعوز الحديد أو الفولات، وتعثّراً في النموّ لدى الأطفال.
Irritable bowel syndrome is a functional disorder — the bowel is structurally normal — giving abdominal pain related to defaecation, with altered stool frequency or form, bloating, and symptoms that fluctuate with stress. It is a diagnosis made after excluding other causes, and the red flags that make it something else are weight loss, rectal bleeding, anaemia, a family history of bowel cancer, onset over the age of fifty and nocturnal symptoms.
متلازمة القولون المتهيّج اضطراب وظيفي — أي أن الأمعاء تكون طبيعية من ناحية التركيب — يعطي ألماً بطنياً مرتبطاً بالتغوّط مع تغيّر تواتر البراز أو شكله وانتفاخاً وأعراضاً تتذبذب مع الكرب. وهي تشخيص يُوضَع بعد استبعاد أسباب أخرى، وعلامات الإنذار التي تجعلها شيئاً آخر هي نقص الوزن والنزف المستقيمي وفقر الدم وقصّة عائلية لسرطان الأمعاء والبدء فوق الخمسين والأعراض الليلية.
Diverticula are outpouchings of the colon wall, common with age and low fibre intake; having them is diverticulosis and is usually silent. Diverticulitis is when one becomes inflamed or infected, giving left lower quadrant pain, fever, altered bowel habit and raised inflammatory markers. Acutely the bowel is rested and antibiotics are given where indicated (selectively, not routinely, in uncomplicated attacks); once settled, a high-fibre diet with good fluid intake reduces recurrence — but fibre is increased after the acute episode, not during it. Complications are abscess, perforation, fistula and stricture.
الرتوج جيوب في جدار القولون شائعة مع العمر وقلّة الألياف؛ ووجودها داء رتوج وهو صامت عادةً. والتهاب الرتج حين يلتهب أحدها أو يُصاب بالعدوى، فيعطي ألماً في الربع السفلي الأيسر وحمّى وتغيّر عادة الأمعاء وارتفاع واسمات الالتهاب. وفي المرحلة الحادّة تُراح الأمعاء وتُعطى المضادات الحيوية عند وجود دواعٍ لها (انتقائياً لا روتينياً في النوبات غير المعقّدة)؛ وبعد هدوء النوبة تقلّل الحمية عالية الألياف مع وارد جيّد من السوائل من النكس — لكن الألياف تُزاد بعد النوبة الحادّة لا أثناءها. والمضاعفات خرّاج وانثقاب وناسور وتضيّق.
5.11 · Appendicitis and Bowel Obstruction٥٫١١ · التهاب الزائدة وانسداد الأمعاء
Appendicitis classically begins as vague central abdominal pain that later localises to the right lower quadrant at McBurney's point, with anorexia, nausea, low-grade fever, rebound tenderness and guarding. The nursing rules are absolute: no heat to the abdomen and no laxatives or enemas, because both increase peristalsis and pressure and raise the risk of rupture. Keep the patient nil by mouth and give analgesia as prescribed.
التهاب الزائدة يبدأ كلاسيكياً بألم بطني مركزي غامض يتوضّع لاحقاً في الربع السفلي الأيمن عند نقطة ماكبرني، مع فقد شهيّة وغثيان وحمّى خفيفة وإيلام ارتدادي وتحارس. والقواعد التمريضية قطعية: لا حرارة على البطن ولا مليّنات ولا حقن شرجية، فكلاهما يزيد التمعّج والضغط ويرفع خطر التمزّق. ويُبقى المريض صائماً ويُعطى المسكّن الموصوف.
The finding that must not be misread: if the pain suddenly stops and the patient feels briefly better, suspect that the appendix has ruptured — the pressure has been relieved. Relief is followed within hours by the diffuse pain, rigidity, fever and deterioration of peritonitis. Report a sudden cessation of pain rather than recording it as improvement.
الموجودة التي يجب ألّا تُساء قراءتها: إن توقّف الألم فجأةً وشعر المريض بتحسّن وجيز فيُشتبَه في أن الزائدة انفجرت — فقد زال الضغط. ويتبع الارتياح خلال ساعات ألم منتشر وصلابة وحمّى وتدهور التهاب البريتون. يُبلَّغ عن توقّف الألم المفاجئ ولا يُسجَّل تحسّناً.
Bowel obstruction divides by level and by mechanism. Small bowel obstruction gives early, frequent vomiting, colicky pain and less distension. Large bowel obstruction gives marked distension, absolute constipation and later, faeculent vomiting. Mechanical obstruction — adhesions, hernia, tumour, volvulus — gives hyperactive, high-pitched bowel sounds early as the bowel strains against the block. Paralytic ileus — after surgery, with electrolyte disturbance or opioids — gives absent bowel sounds from the start, because the bowel is not contracting at all.
انسداد الأمعاء ينقسم بالمستوى وبالآلية. فانسداد الأمعاء الدقيقة يعطي تقيّؤاً مبكّراً متكرّراً وألماً مغصياً وانتفاخاً أقلّ. وانسداد الأمعاء الغليظة يعطي انتفاخاً ملحوظاً وإمساكاً تامّاً ولاحقاً تقيّؤاً برازياً. والانسداد الميكانيكي — التصاقات أو فتق أو ورم أو انفتال — يعطي أصوات أمعاء مفرطة النشاط عالية النبرة مبكّراً مع كفاح الأمعاء ضدّ السدّ. والعلوص الشللي — بعد الجراحة أو مع اضطراب شوارد أو أفيونيات — يعطي غياب أصوات الأمعاء من البداية، فالأمعاء لا تنقبض إطلاقاً.
Management of obstruction: nil by mouth, a nasogastric tube on free drainage or suction to decompress, intravenous fluids and electrolyte correction, strict input and output, analgesia and antiemetics, and monitoring for strangulation — increasing constant pain rather than colic, fever, tachycardia, peritonism and a rising lactate, which indicates the bowel is losing its blood supply and needs surgery.
تدبير الانسداد: صيام، وأنبوب أنفي معدي على تصريف حرّ أو شفط لتخفيف الضغط، وسوائل وريدية وتصحيح شوارد، وميزان وارد وصادر دقيق، ومسكّن ومضادّ قيء، ومراقبة الاختناق — أي ألم متزايد ثابت لا مغصي وحمّى وتسرّع نبض وأعراض بريتونية وارتفاع لاكتات، ما يدلّ على فقد الأمعاء إمدادها الدموي وحاجتها للجراحة.
5.12 · Colorectal Disease and Stomas٥٫١٢ · أمراض القولون والمستقيم والفغرات
- Presents LATEيظهر متأخراً
- Iron deficiency ANAEMIA, fatigue and weight lossفقر دم بنقص الحديد، تعب، وفقدان وزن
- Because the bowel is wide and the contents are liquidلأن الأمعاء واسعة والمحتويات سائلة
- So obstruction happens late, and there is no change in bowel habit to noticeلذا يحدث الانسداد متأخراً، ولا يوجد تغيّر في عادة التبرّز يُلاحَظ
- Presents EARLIERيظهر في وقت أبكر
- Change in bowel habit, rectal bleedingتغيّر في عادة التبرّز، نزيف مستقيمي
- And obstructionوانسداد
- Because the bowel is narrower and the contents are formedلأن الأمعاء أضيق والمحتويات متماسكة
The consequence that changes practice: iron deficiency anaemia in a man or a post-menopausal woman is a colorectal red flag in its own right — investigated, not simply treated with iron, because the right-sided tumour gives no other symptom until it is advanced.
العاقبة التي تغيّر الممارسة: أن فقر دم نقص الحديد في رجل أو امرأة بعد سنّ اليأس علامة إنذار قولونية بذاتها — يُحقَّق لا يُعالَج بالحديد فقط، لأن الورم الأيمن لا يسبّب عرضاً آخر قبل أن يتقدّم.
Stoma output tells you where it is. A colostomy, formed from the colon, produces formed or semi-formed stool less frequently, and may become predictable. An ileostomy, formed from the small bowel, produces liquid to porridge-like output continuously and in large volume, and it contains digestive enzymes that excoriate the skin rapidly — so the appliance must fit closely and the skin is protected meticulously. Ileostomy patients are also at risk of dehydration and electrolyte loss, particularly sodium and potassium, because the colon that would normally reabsorb water has been bypassed.
صادر الفغرة يدلّ على موقعها. ففغرة القولون المتكوّنة من القولون تُنتج برازاً متشكّلاً أو شبه متشكّل بتواتر أقلّ وقد تصير متوقّعة. وفغرة اللفائفي المتكوّنة من الأمعاء الدقيقة تُنتج صادراً سائلاً إلى شبه عصيدة باستمرار وبحجم كبير، وهو يحوي إنزيمات هضمية تسحج الجلد بسرعة — فيجب أن يطابق الكيس بإحكام ويُحمى الجلد بدقّة. ومرضى فغرة اللفائفي معرّضون أيضاً للجفاف وفقد الشوارد وخاصّةً الصوديوم والبوتاسيوم، فالقولون الذي كان سيعيد امتصاص الماء قد جُووِز.
Stoma assessment follows Part 01 Chapter 07: a healthy stoma is pink or red, moist and slightly raised; a dusky, purple or black stoma indicates ischaemia and is reported immediately; and a small amount of bleeding when cleaning is normal because the mucosa is vascular. Report no output with distension and pain, which may be obstruction, and excessive output, which risks dehydration.
تقييم الفغرة يتبع الفصل السابع من الجزء الأول: فالفغرة السليمة وردية أو حمراء رطبة مرتفعة قليلاً؛ والفغرة القاتمة أو البنفسجية أو السوداء تدلّ على نقص تروية ويُبلَّغ عنها فوراً؛ وقليل من النزف عند التنظيف طبيعي فالمخاطية وعائية. ويُبلَّغ عن غياب الصادر مع انتفاخ وألم وقد يكون انسداداً، وعن الصادر المفرط الذي يعرّض لخطر الجفاف.
5.13 · Anorectal Conditions and Gut Infections٥٫١٣ · حالات الشرج والمستقيم وعدوى الأمعاء
- BRIGHT RED bleeding on the SURFACE of the stool or on the paperنزيف أحمر فاتح على سطح البراز أو على الورق
- Itching and discomfortحكّة وانزعاج
- Often painless unless thrombosedغالباً غير مؤلمة إلا إذا تخثّرت
- Treated with fibre, fluid, avoiding straining, topical preparations and bandingتُعالَج بالألياف والسوائل وتجنّب الحزق عند التبرّز والمستحضرات الموضعية والربط
- SEVERE SHARP pain DURING and after defecationألم حادّ شديد أثناء التبرّز وبعده
- ‘Like passing glass’ — which is how patients describe it«كأنّ زجاجاً يمرّ» — هكذا يصفه المرضى
- With a small amount of bright bloodمع كمية صغيرة من دم أحمر فاتح
- The pain causes fear of defecation → constipation → harder stool → more tearingالألم يسبّب الخوف من التبرّز ← إمساك ← براز أصلب ← تمزّق أكثر
- So breaking the cycle with stool softeners and topical treatment IS the treatmentلذا كسر هذه الحلقة بمليّنات البراز والعلاج الموضعي هو العلاج نفسه
And the rule that matters more than either: rectal bleeding is NOT assumed to be haemorrhoids. Dark blood, blood mixed THROUGH the stool, a change in bowel habit, weight loss, or bleeding in an older patient is investigated — because a patient who has haemorrhoids can also have a cancer, and the visible cause is the one that stops people looking.
والقاعدة الأهمّ من كليهما: أن النزف المستقيمي لا يُفترَض أنه ناجم عن البواسير. فالدم الداكن أو المختلط بالبراز أو تغيّر عادة الأمعاء أو نقص الوزن أو النزف لدى مريض متقدّم في السنّ يُحقَّق — لأن مريض البواسير قد يكون مصاباً بسرطان أيضاً، والسبب الظاهر هو ما يصرف الانتباه عن مواصلة البحث.
Typhoid fever is caused by Salmonella typhi spread by the faecal–oral route through contaminated food and water. It gives a stepwise rising fever, headache, abdominal pain, and characteristically a relative bradycardia — a pulse slower than the fever would predict — with rose spots and either constipation or diarrhoea. Its feared complication is intestinal perforation in the second or third week, so new severe abdominal pain in a patient with typhoid is escalated urgently. Prevention is food and water hygiene and vaccination for travellers.
الحمّى التيفية تسبّبها السالمونيلا التيفية وتنتشر بالطريق البرازي الفموي عبر طعام وماء ملوّثين. وتعطي حمّى متصاعدة درجيّاً وصداعاً وألماً بطنياً، وبصورة مميّزة بطءَ نبض نسبياً — أي نبضاً أبطأ ممّا تتنبّأ به الحمّى — مع بقع وردية وإمساك أو إسهال. ومضاعفتها المخيفة انثقاب معوي في الأسبوع الثاني أو الثالث، فالألم البطني الشديد الجديد لدى مريض تيفية يُصعَّد عاجلاً. والوقاية نظافة الطعام والماء والتطعيم للمسافرين.
Parasitic infections such as amoebiasis and giardiasis also spread by contaminated food and water and cause prolonged diarrhoea — amoebiasis classically with blood and mucus and a risk of liver abscess, giardiasis with bloating, foul-smelling stool and malabsorption. Diagnosis is by stool microscopy or antigen testing, and a travel and residence history is part of assessing any patient with persistent diarrhoea.
العدوى الطفيلية كداء الأميبات والجيارديا تنتشر أيضاً بطعام وماء ملوّثين وتسبّب إسهالاً مطوّلاً — فداء الأميبات كلاسيكياً بدم ومخاط وخطر خرّاج كبد، والجيارديا بانتفاخ وبراز كريه الرائحة وسوء امتصاص. والتشخيص بالفحص المجهري للبراز أو اختبار المستضدّ، وقصّة السفر والإقامة جزء من تقييم أيّ مريض بإسهال مستمرّ.
5.14 · Hepatitis٥٫١٤ · التهاب الكبد
The route of transmission is what the exam tests, and it separates them cleanly. Hepatitis A and E spread by the faecal–oral route — contaminated food and water, poor sanitation — and are acute, self-limiting illnesses that do not become chronic. Hepatitis B, C and D spread by blood and body fluids, including needlestick injury, sexual contact, sharing needles and vertical transmission from mother to child, and B and C can become chronic, leading to cirrhosis and liver cancer.
طريق الانتقال هو ما يختبره الامتحان، وهو يفصل بينها بوضوح. فالتهاب الكبد A وE ينتقلان بالطريق البرازي الفموي — طعام وماء ملوّثان وسوء صرف صحّي — وهما مرضان حادّان محدودان ذاتياً لا يصيران مزمنين. والتهاب الكبد B وC وD تنتقل بالدم وسوائل الجسم، بما في ذلك وخز الإبر والاتصال الجنسي ومشاركة الإبر والانتقال العمودي من الأمّ للطفل، وB وC قد يصيران مزمنين فيقودان للتليف وسرطان الكبد.
Prevention divides the same way. For A and E: hand hygiene, safe food and water, and vaccination against hepatitis A. For B: vaccination, which is the single most effective measure and is given to healthcare workers, plus standard precautions and safe sharps handling as Part 01 Chapter 05 sets out. There is no vaccine for hepatitis C, but it is now curable with direct-acting antiviral drugs. Hepatitis D only occurs in someone who has hepatitis B, so preventing B prevents D.
الوقاية تنقسم بالطريقة نفسها. فلـA وE: نظافة اليدين وطعام وماء آمنان والتطعيم ضدّ التهاب الكبد A. ولـB: التطعيم وهو أنجع تدبير منفرد ويُعطى للعاملين الصحّيين، مع الاحتياطات القياسية والتعامل الآمن مع الأدوات الحادّة كما يبيّن الفصل الخامس من الجزء الأول. ولا لقاح لالتهاب الكبد C، لكنه صار قابلاً للشفاء بمضادّات فيروسية مباشرة المفعول. والتهاب الكبد D لا يحدث إلا لمن لديه B، فمنع B يمنع D.
After a needlestick injury the sequence is: encourage the wound to bleed gently, wash with soap and running water without scrubbing, do not squeeze aggressively, report immediately, and attend occupational health for risk assessment, source testing and post-exposure prophylaxis where indicated — which is time-critical. The healthcare worker at highest risk for hepatitis B is the one sustaining a needlestick from an infected patient, which is precisely why vaccination is not optional.
بعد وخز إبرة يكون التسلسل: تشجيع الجرح على النزف برفق، والغسل بالصابون والماء الجاري دون فرك، وعدم العصر بعنف، والإبلاغ فوراً، ومراجعة الصحّة المهنية لتقييم الخطر وفحص المصدر والوقاية بعد التعرّض حيث تُستطبّ — وهي حرجة زمنياً. والعامل الصحّي الأعلى خطراً لالتهاب الكبد B هو من يتعرّض لوخز إبرة من مريض مصاب، وهذا بالضبط سبب كون التطعيم غير اختياري.
5.15 · Cirrhosis and Portal Hypertension٥٫١٥ · التليف وارتفاع الضغط البابي
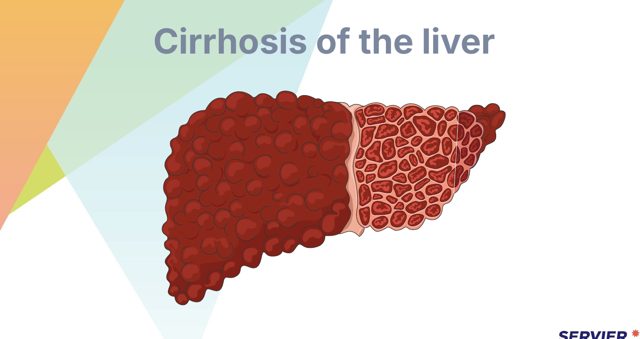
Cirrhosis is irreversible scarring that both destroys liver function and obstructs blood flow through the liver, and its complications follow from those two facts. Worldwide the causes are chronic viral hepatitis, alcohol and non-alcoholic fatty liver disease (NAFLD, now also called MASLD); in the Kingdom, fatty liver disease is now the most common liver disease and a rapidly rising cause, alongside viral hepatitis.
التليف تندّب لا رجعة فيه يُتلف وظيفة الكبد ويعيق جريان الدم عبره، ومضاعفاته تتبع هاتين الحقيقتين. وعالمياً الأسباب التهاب الكبد الفيروسي المزمن والكحول ومرض الكبد الدهني غير الكحولي (NAFLD، ويُعرف الآن أيضاً باسم MASLD)؛ وفي المملكة صار مرض الكبد الدهني أكثر أمراض الكبد شيوعاً وسبباً متزايداً بسرعة، إلى جانب التهاب الكبد الفيروسي.
From lost function: jaundice as bilirubin accumulates; hypoalbuminaemia causing oedema and contributing to ascites; coagulopathy with easy bruising and bleeding, because clotting factors are made in the liver; hepatic encephalopathy as toxins are no longer cleared; and impaired drug metabolism, so doses often need reducing. From portal hypertension: oesophageal varices, ascites, splenomegaly with a falling platelet count, and dilated abdominal wall veins.
من فقد الوظيفة: اليرقان مع تراكم البيليروبين؛ ونقص ألبومين الدم فيسبّب وذمة ويسهم في الاستسقاء؛ واضطراب التخثّر مع سهولة الكدمات والنزف، فعوامل التخثّر تُصنَع في الكبد؛ واعتلال الدماغ الكبدي مع توقّف تصفية السموم؛ واختلال استقلاب الأدوية فتحتاج الجرعات خفضاً غالباً. ومن ارتفاع الضغط البابي: دوالي المريء والاستسقاء وضخامة الطحال مع انخفاض عدد الصفيحات وأوردة جدار بطن متوسّعة.
Ascites is managed with sodium restriction, diuretics — typically spironolactone with or without furosemide — daily weight and girth measurement, and paracentesis for tense or refractory ascites, with albumin after a large-volume drain. Watch for spontaneous bacterial peritonitis, which is infection of the ascitic fluid and can be subtle: fever, abdominal pain or tenderness, or simply a deterioration in mental state or renal function in a patient with ascites. It is diagnosed by sampling the fluid and is a reason to escalate rather than observe.
الاستسقاء يُدبَّر بتقييد الصوديوم ومدرّات — سبيرونولاكتون مع أو دون فوروسيميد عادةً — ووزن ومحيط يوميين، وبزل البطن للاستسقاء المشدود أو المعند مع ألبومين بعد تصريف حجم كبير. وتجب مراقبة التهاب البريتون الجرثومي العفوي وهو عدوى في سائل الاستسقاء وقد يكون خفياً: حمّى أو ألم أو إيلام بطني أو مجرّد تدهور في الحالة الذهنية أو وظيفة الكلى لدى مريض باستسقاء. ويُشخَّص بأخذ عيّنة من السائل وهو سبب للتصعيد لا للمراقبة.
5.16 · Hepatic Encephalopathy٥٫١٦ · اعتلال الدماغ الكبدي
As the liver fails it can no longer clear nitrogenous waste — principally ammonia produced by gut bacteria acting on protein — and it accumulates and affects the brain. The presentation runs from subtle to profound: reversal of the sleep pattern, irritability and slowed thinking early; then confusion, disorientation and asterixis, the flapping tremor of the outstretched hands; then drowsiness and coma. Fetor hepaticus, a sweet musty breath odour, accompanies it.
مع فشل الكبد لا يعود يصفّي الفضلات النتروجينية — وأساساً الأمونيا التي تُنتجها جراثيم الأمعاء بعملها على البروتين — فتتراكم وتؤثّر على الدماغ. والتظاهر يمتدّ من الخفيّ للعميق: انعكاس نمط النوم والتهيّج وبطء التفكير مبكّراً؛ ثم تشوّش وتوهان ورعاش خافق في اليدين الممدودتين؛ ثم نعاس وغيبوبة. والرائحة الكبدية، وهي رائحة نفَس حلوة عفنة، ترافقه.
The precipitants are what the nurse looks for, because treating them is often what reverses it: gastrointestinal bleeding — blood in the gut is a large protein load; infection, including spontaneous bacterial peritonitis; constipation; dehydration and electrolyte disturbance, particularly from over-diuresis; sedatives and opioids; and a high protein load.
المُحدِثات هي ما يبحث عنه الطاقم التمريضي، فعلاجها غالباً ما يعكسه: نزف هضمي — فالدم في الأمعاء حمل بروتيني كبير؛ وعدوى بما فيها التهاب البريتون الجرثومي العفوي؛ وإمساك؛ وجفاف واضطراب شوارد وخاصّةً من إفراط الإدرار؛ ومهدّئات وأفيونيات؛ وحمل بروتيني عالٍ.
Lactulose is the mainstay. It acidifies the colon so ammonia is trapped and cannot be absorbed, and it acts as a laxative to clear it. The therapeutic target is two to three soft stools a day — that is the endpoint the dose is titrated to, and it is what the exam asks. Too few means the dose is inadequate; too many causes dehydration and electrolyte loss, which can itself worsen the encephalopathy. Rifaximin, a poorly absorbed antibiotic that reduces ammonia-producing gut bacteria, is often added.
اللاكتولوز هو العماد. فهو يحمّض القولون فتُحتبَس الأمونيا ولا تُمتَصّ، ويعمل كمليّن لطرحها. والهدف العلاجي برازان إلى ثلاثة برازات ليّنة يومياً — وتلك النهاية التي تُعاير عليها الجرعة، وهي ما يسأل عنه الامتحان. فالأقلّ يعني جرعة غير كافية؛ والأكثر يسبّب جفافاً وفقد شوارد قد يفاقم الاعتلال نفسه. والريفاكسيمين، وهو مضاد حيوي ضعيف الامتصاص يقلّل جراثيم الأمعاء المنتجة للأمونيا، يُضاف غالباً.
Nursing care: monitor the conscious level and orientation at intervals and document specifics rather than 'confused', since the trend is what matters; assess for asterixis; ensure safety and fall prevention; avoid sedatives; maintain nutrition with adequate protein rather than the severe restriction once practised, because malnutrition worsens outcomes; and look actively for a precipitant every time.
الرعاية التمريضية: مراقبة مستوى الوعي والتوجّه على فترات وتوثيق التفاصيل لا كلمة «مشوّش»، فالاتّجاه هو المهمّ؛ وتقييم الرعاش الخافق؛ وضمان السلامة ومنع السقوط؛ وتجنّب المهدّئات؛ والمحافظة على التغذية ببروتين كافٍ لا التقييد الشديد الذي كان يُمارَس، فسوء التغذية يزيد النتائج سوءًا؛ والبحث بفاعلية عن مُحدِث في كلّ مرّة.
5.17 · Gallbladder and Biliary Disease٥٫١٧ · أمراض المرارة والقنوات الصفراوية
Biliary colic is severe right upper quadrant or epigastric pain radiating to the right shoulder or scapula, coming on after a fatty meal, lasting hours and settling. Acute cholecystitis adds inflammation: constant pain, fever, tenderness and a positive Murphy's sign. Cholangitis is infection of the bile duct and is the dangerous one, marked by Charcot's triad — fever with rigors, right upper quadrant pain and jaundice. It can progress to septic shock and needs urgent antibiotics and biliary drainage.
المغص الصفراوي ألم شديد في الربع العلوي الأيمن أو أعلى البطن ينتشر للكتف أو لوح الكتف الأيمن، يظهر بعد وجبة دهنية ويدوم ساعات ثم يهدأ. والتهاب المرارة الحادّ يضيف التهاباً: ألم ثابت وحمّى وإيلام وعلامة مورفي إيجابية. والتهاب الأقنية الصفراوية عدوى في القناة الصفراوية وهو الخطير، ويتميّز بثلاثي شاركو — حمّى مع قشعريرة وألم في الربع العلوي الأيمن ويرقان. وقد يتقدّم لصدمة إنتانية ويحتاج مضادات حيوية عاجلة وتصريفاً صفراوياً.
Obstructive jaundice from a stone in the common bile duct gives the recognisable triad of yellow skin and sclerae, dark urine and pale clay-coloured stool, often with intense pruritus from bile salts in the skin. Manage the itching with cool showers, emollients, short nails, loose cotton clothing and avoiding heat, and expect prothrombin time to be checked, since bile is needed to absorb vitamin K.
اليرقان الانسدادي من حصاة في القناة الصفراوية المشتركة يعطي الثلاثي المميّز: جلد وصلبة صفراوان وبول داكن وبراز شاحب بلون الطين، مع حكّة شديدة غالباً من أملاح الصفراء في الجلد. وتُدبَّر الحكّة بحمّامات باردة ومرطّبات وأظافر قصيرة وملابس قطنية فضفاضة وتجنّب الحرارة، ويُتوقَّع فحص زمن البروثرومبين، فالصفراء لازمة لامتصاص فيتامين ك.
After laparoscopic cholecystectomy, the specific point is REFERRED SHOULDER-TIP PAIN from the carbon dioxide used to inflate the abdomen — it is EXPECTED, it is not a complication, and it settles over a day or two. Warning him in advance is what stops him thinking something has gone wrong, and mobilising helps it disperse.
بعد استئصال المرارة بالمنظار تكون النقطة المحدّدة هي ألم طرف الكتف المُحال من ثاني أكسيد الكربون المستخدَم لنفخ البطن — وهو متوقّع وليس مضاعفةً ويهدأ خلال يوم أو يومين. وتحذير المريض مسبقاً هو ما يمنعه من الظنّ بأن خطباً ما قد حدث، والتحرّك المبكّر يساعد على زواله.
5.18 · Pancreatitis٥٫١٨ · التهاب البنكرياس
The two dominant causes are gallstones and alcohol, with others including hypertriglyceridaemia, certain drugs and ERCP. The pancreas digests itself, and the presentation is severe epigastric pain radiating straight through to the back, relieved somewhat by sitting forward and leaning over, with nausea, vomiting, fever, tachycardia and abdominal tenderness. Lipase is more specific than amylase.
السببان المهيمنان حصيات المرارة والكحول، ومن الأسباب الأخرى فرط ثلاثيات الغليسريد في الدم وأدوية معيّنة وتصوير القنوات الصفراوية والبنكرياسية بالتنظير. والبنكرياس يهضم نفسه، والتظاهر ألم أعلى البطن شديد ينتشر نافذاً للظهر ويخفّ بعض الشيء بالجلوس مائلاً للأمام، مع غثيان وتقيّؤ وحمّى وتسرّع نبض وإيلام بطني. والليباز أكثر نوعيةً من الأميلاز.
Cullen's and Grey Turner's signs — periumbilical and flank bruising — indicate retroperitoneal haemorrhage and mark severe disease. Watch for the systemic complications, because severe pancreatitis is a critical illness: hypovolaemic shock from massive third-space fluid loss, hypocalcaemia, hyperglycaemia, acute respiratory distress syndrome, acute kidney injury, and later pseudocyst and necrosis.
علامتا كولن وغراي تيرنر — الكدم حول السرّة وفي الخاصرتين — تدلّان على نزف خلف الصفاق وتُميّزان المرض الشديد. وتجب مراقبة المضاعفات الجهازية، فالتهاب البنكرياس الشديد مرض حرج: صدمة نقص حجم من فقد سوائل هائل للحيّز الثالث، ونقص كالسيوم، وارتفاع سكّر، ومتلازمة ضائقة تنفّسية حادّة، وأذيّة كلوية حادّة، ولاحقاً كيسة كاذبة ونخر.
Management: early goal-directed intravenous fluid resuscitation (avoiding over-resuscitation), which is the single most important early intervention; effective analgesia, because the pain is severe; antiemetics; nil by mouth initially to rest the pancreas, with early enteral feeding reintroduced as tolerated because prolonged starvation worsens outcomes; correction of electrolytes with attention to calcium and magnesium; and close monitoring of fluid balance, blood glucose, oxygenation and renal function. Position the patient sitting forward if that eases the pain.
التدبير: إنعاش وريدي مبكّر موجَّه بالهدف بالسوائل (مع تجنّب الإفراط في الإنعاش) وهو أهمّ تدخّل مبكّر منفرد؛ ومسكّن فعّال فالألم شديد؛ ومضادّات قيء؛ وصيام أولاً لإراحة البنكرياس مع إعادة التغذية المعوية مبكّراً بحسب التحمّل لأن الصيام المطوّل يجعل النتائج أسوأ؛ وتصحيح الشوارد مع انتباه للكالسيوم والمغنيسيوم؛ ومراقبة لصيقة لميزان السوائل وسكّر الدم والأكسجة ووظيفة الكلى. ويوضَع المريض جالساً مائلاً للأمام إن خفّف ذلك الألم.
Chronic pancreatitis destroys the gland over time, producing persistent pain, steatorrhoea from loss of digestive enzymes, weight loss and eventually diabetes as the islet cells are lost. Treatment includes pancreatic enzyme replacement taken with every meal and snack — the timing matters, exactly as it does with phosphate binders — plus fat-soluble vitamin supplementation, an adequate-energy diet (fat is restricted only if steatorrhoea persists despite enzyme replacement), and complete avoidance of alcohol. Pancreatic cancer often presents late with painless obstructive jaundice, weight loss and back pain.
التهاب البنكرياس المزمن يُتلف الغدّة مع الوقت فيُنتج ألماً مستمرّاً وإسهالاً دهنياً من فقد الإنزيمات الهضمية ونقصاً في الوزن وفي النهاية داء السكّري مع فقد خلايا الجزر. والعلاج يشمل تعويض إنزيمات البنكرياس مع كلّ وجبة ووجبة خفيفة — والتوقيت يهمّ تماماً كما مع رابطات الفوسفات — مع تعويض الفيتامينات الذوّابة في الدهن وحمية كافية الطاقة (يُقيَّد الدهن فقط إن استمر الإسهال الدهني رغم تعويض الإنزيمات) وتجنّب الكحول تماماً. وسرطان البنكرياس يتظاهر متأخّراً غالباً بيرقان انسدادي غير مؤلم ونقص وزن وألم ظهر.
5.19 · Gastrointestinal Cancer and Major Surgery٥٫١٩ · سرطان الجهاز الهضمي والجراحة الكبرى
Gastric cancer presents late because early symptoms are vague — indigestion, early satiety, mild epigastric discomfort — and by the time there is weight loss, vomiting, anaemia or a palpable mass the disease is advanced. Risk factors include Helicobacter pylori, smoking, and diets high in salted, smoked and preserved foods. A patient over the usual age with new persistent dyspepsia, weight loss, dysphagia, vomiting or anaemia is referred for endoscopy rather than treated with acid suppression alone — the alarm features are what trigger investigation.
سرطان المعدة يتظاهر متأخّراً لأن الأعراض المبكّرة غامضة — عسر هضم وشبع مبكّر وانزعاج أعلى البطن خفيف — وبحلول ظهور نقص الوزن والتقيّؤ وفقر الدم أو كتلة محسوسة يكون المرض متقدّماً. وعوامل الخطر تشمل الملوية البوابية والتدخين والحميات العالية بالأطعمة المملّحة والمدخّنة والمحفوظة. والمريض فوق السنّ المعتاد بعسر هضم جديد مستمرّ أو نقص وزن أو عسر بلع أو تقيّؤ أو فقر دم يُحال للتنظير لا يُعالَج بكبت الحمض وحده — فسمات الإنذار هي ما يُطلق الاستقصاء.
Pancreatic cancer and tumours of the head of the pancreas or bile duct may be treated with a PANCREATICODUODENECTOMY — the WHIPPLE procedure — a long and major operation removing the head of the pancreas, the duodenum, the gallbladder and part of the bile duct, with reconstruction.
سرطان البنكرياس وأورام رأسه أو القناة الصفراوية قد تُعالَج باستئصال البنكرياس والاثني عشر — إجراء ويبل — عملية كبرى طويلة تشمل استئصال رأس البنكرياس والاثني عشر والمرارة وجزء من القناة الصفراوية مع إعادة البناء.
In advanced gastrointestinal cancer the priorities shift to PALLIATIVE symptom control and QUALITY OF LIFE.
في سرطان الجهاز الهضمي المتقدّم تتحوّل الأولويات إلى التحكّم الملطّف بالأعراض وجودة الحياة.
Blunt abdominal trauma — from a road traffic accident or a fall — can injure the spleen or liver, both of which bleed heavily. Look for a seat-belt mark, bruising, abdominal distension, tenderness and referred left shoulder pain from a splenic injury irritating the diaphragm. Monitor for haemorrhage: pulse, blood pressure, conscious level, and the fact that a young patient compensates well and then decompensates suddenly. Do not palpate repeatedly, keep him nil by mouth, obtain large-bore access and crossmatch, and escalate.
إصابة البطن الرضّية غير النافذة — من حادث مروري أو سقوط — قد تصيب الطحال أو الكبد وكلاهما ينزف بغزارة. يُبحَث عن أثر حزام الأمان وكدمات وانتفاخ بطني وإيلام وألم محال إلى الكتف الأيسر من إصابة طحالية تهيّج الحجاب الحاجز. ويُراقَب النزف: النبض والضغط ومستوى الوعي، وحقيقة أن المريض الشابّ يعوّض جيّداً ثم ينهار تعويضه فجأةً. ولا يُجَسّ البطن مراراً، ويُبقى المريض صائماً، ويُؤمَّن مدخل واسع ومطابقة زمر، ويُصعَّد الأمر.
5.20 · Tubes, Drains and Abdominal Surgery٥٫٢٠ · الأنابيب والمنازح وجراحة البطن
A nasogastric tube serves two different purposes and the exam distinguishes them. For decompression — in bowel obstruction, ileus or persistent vomiting — it is placed on free drainage or low suction to remove gastric contents and gas, relieving distension, nausea and vomiting and reducing the risk of aspiration. For feeding, it delivers nutrition, as Part 01 Chapter 07 sets out.
الأنبوب الأنفي المعدي يؤدّي غرضين مختلفين والامتحان يميّز بينهما. فلتخفيف الضغط — في انسداد الأمعاء أو العلوص أو التقيّؤ المستمرّ — يُوضَع على تصريف حرّ أو شفط منخفض لإزالة محتويات المعدة والغاز، فيخفّف الانتفاخ والغثيان والتقيّؤ ويقلّل خطر الاستنشاق. وللتغذية يوصّل الغذاء كما يبيّن الفصل السابع من الجزء الأول.
Placement is confirmed by aspirating gastric contents and testing the pH, which should be 5.5 or below; an X-ray is used where the aspirate cannot be obtained or the pH is higher. The auscultated air bolus is not a reliable method. Signs the decompression is working are reduced abdominal distension, relief of nausea and vomiting, and return of bowel sounds and flatus.
يُؤكَّد الموضع بشفط محتوى معدي وفحص درجة الحموضة (pH) التي ينبغي أن تكون ٥٫٥ أو أقلّ؛ وتُستخدَم صورة أشعّة حيث يتعذّر الحصول على الرشافة أو تكون درجة الحموضة أعلى. وحقن الهواء المسموع بالإصغاء ليس طريقة موثوقة. وعلامات نجاح التخفيف نقص انتفاخ البطن وزوال الغثيان والتقيّؤ وعودة أصوات الأمعاء والريح.
Abdominal drains are measured and their character recorded. After abdominal surgery, watch for paralytic ileus — absent bowel sounds, distension, no flatus — which delays feeding and resolves with time, mobilisation and correcting electrolytes and opioid load. Early mobilisation, adequate analgesia so the patient can move and breathe, and early oral intake where allowed are the principles that shorten recovery.
منازح البطن تُقاس ويُسجَّل طابعها. وبعد جراحة البطن تجب مراقبة العلوص الشللي — غياب أصوات الأمعاء وانتفاخ وانعدام الريح — وهو يؤخّر التغذية ويزول بالوقت والتحريك وتصحيح الشوارد وحمل الأفيونيات. والتحريك المبكّر والتسكين الكافي ليتحرّك المريض ويتنفّس، والوارد الفموي المبكّر حيث يُسمح به، هي المبادئ التي تقصّر التعافي.
Wound dehiscence and evisceration follow the rule set out in Part 01 Chapter 07 and it is worth repeating because it is absolute: if bowel protrudes through the wound, cover it immediately with sterile gauze moistened with sterile normal saline, place the patient in low Fowler's with the knees bent to reduce abdominal tension, keep him nil by mouth, notify immediately and prepare for theatre. Do not attempt to push the bowel back in, and do not let the gauze dry out.
تفزّر الجرح وبروز الأحشاء يتبعان القاعدة المبيّنة في الفصل السابع من الجزء الأول وتستحقّ التكرار فهي قطعية: فإن برزت أمعاء عبر الجرح يجب تغطيتها فوراً بشاش معقّم مبلّل بمحلول ملحي طبيعي معقّم، ويوضَع المريض في وضعية فاولر المنخفضة والركبتان مثنيّتان لتقليل الشدّ البطني، ويُبقى المريض صائماً، ويُبلَّغ فوراً ويُحضَّر لغرفة العمليات. ولا تُحاوَل إعادة الأمعاء إلى الداخل، ولا يُترَك الشاش يجفّ.
5.21 · Nutrition in Gastrointestinal Disease٥٫٢١ · التغذية في المرض الهضمي
The principle is simple and often forgotten: if the gut works, use it. Enteral feeding maintains the gut mucosa, is cheaper and carries fewer serious complications than parenteral nutrition, which is reserved for a gut that cannot be used — obstruction, severe malabsorption, high-output fistula or prolonged ileus. Parenteral nutrition is never stopped abruptly, because rebound hypoglycaemia follows, as Part 01 Chapter 07 sets out.
المبدأ بسيط وكثيراً ما يُنسى: إن كانت الأمعاء تعمل فيجب استخدامها. فالتغذية المعوية تحافظ على مخاطية الأمعاء وهي أرخص وتحمل مضاعفات خطيرة أقلّ من التغذية الوريدية المحجوزة لأمعاء لا يمكن استخدامها — انسداد أو سوء امتصاص شديد أو ناسور عالي الصادر أو علوص مطوّل. والتغذية الوريدية لا تُوقَف فجأةً أبداً، فيتبعها نقص سكّر دم ارتدادي كما يبيّن الفصل السابع من الجزء الأول.
Refeeding syndrome is the danger in a patient who has been malnourished or starved — including after prolonged vomiting, in alcohol dependence, after bariatric surgery or with any prolonged poor intake. When feeding restarts, insulin drives phosphate, potassium and magnesium into the cells and the serum levels fall sharply, causing arrhythmia, respiratory failure, seizures and death. The prevention is to start feeding slowly and low, check and replace phosphate, potassium and magnesium before and during, give thiamine, and monitor closely for the first several days.
متلازمة إعادة التغذية هي الخطر لدى مريض كان سيّئ التغذية أو مجوَّعاً — بما في ذلك بعد تقيّؤ مطوّل أو في الاعتماد على الكحول أو بعد جراحة السمنة أو مع أيّ وارد ضعيف مطوّل. فحين تُستأنف التغذية يدفع الإنسولين الفوسفات والبوتاسيوم والمغنيسيوم إلى الخلايا فتهبط مستويات المصل بحدّة، ما يسبّب اضطراب نظم وفشلاً تنفّسياً واختلاجات وموتاً. والوقاية بدء التغذية ببطء وبمقدار منخفض وفحص وتعويض الفوسفات والبوتاسيوم والمغنيسيوم قبلها وأثناءها وإعطاء الثيامين والمراقبة اللصيقة الأيام الأولى.
Therapeutic diets to know: a low-residue diet reduces stool bulk and is used in acute flares of inflammatory bowel disease, diverticulitis and around bowel surgery; a high-fibre diet with good fluid intake prevents constipation and diverticular disease and is introduced once an acute episode has settled; and a gluten-free diet in coeliac disease is strict and lifelong.
الحميات العلاجية الواجب معرفتها: الحمية منخفضة البقايا تقلّل حجم البراز وتُستخدَم في هجمات داء الأمعاء الالتهابي الحادّة والتهاب الرتج وحول جراحة الأمعاء؛ والحمية عالية الألياف مع وارد سوائل جيّد تمنع الإمساك وداء الرتوج وتُدخَل بعد هدوء النوبة الحادّة؛ والحمية الخالية من الغلوتين في الداء البطني صارمة ومدى الحياة.
5.22 · Gastrointestinal Emergencies٥٫٢٢ · الطوارئ الهضمية
The acute abdomen that needs a surgeon now has recognisable features: sudden severe pain, a board-like rigid abdomen, absent bowel sounds, rebound tenderness, and a patient who lies completely still because movement is agony. Compare that with renal colic in Chapter 04, where the patient cannot keep still — the difference in behaviour is itself diagnostic. The response is nil by mouth, notify immediately, intravenous access and fluids, analgesia, and prepare for surgery.
البطن الحادّ الذي يحتاج جرّاحاً الآن له سمات مميّزة: ألم شديد مفاجئ وبطن صلب كاللوح وغياب أصوات الأمعاء وإيلام ارتدادي ومريض يستلقي ساكناً تماماً فالحركة عذاب. ويُقارَن ذلك بالمغص الكلوي في الفصل الرابع حيث لا يستطيع المريض السكون — والفرق في السلوك تشخيصي بحدّ ذاته. والاستجابة صيام وإبلاغ فوري ومدخل وريدي وسوائل ومسكّن وتحضير للجراحة.
Bowel ischaemia is the diagnosis that is missed because the early picture is deceptive: severe pain that is markedly out of proportion to the abdominal findings, in a patient who is often elderly with atrial fibrillation or vascular disease. As the bowel dies, the pain may briefly ease before peritonitis and shock follow, and the lactate rises. Pain out of proportion to the examination is a reason to escalate rather than reassure.
نقص تروية الأمعاء هو التشخيص الذي يُغفَل لأن الصورة المبكّرة خادعة: ألم شديد غير متناسب بوضوح مع موجودات البطن، لدى مريض مسنّ برجفان أذيني أو مرض وعائي غالباً. ومع موت الأمعاء قد يخفّ الألم وجيزاً قبل أن يتبعه التهاب بريتون وصدمة، وترتفع اللاكتات. والألم غير المتناسب مع الفحص سبب للتصعيد لا للطمأنة.
Massive gastrointestinal bleeding is managed as in the upper gastrointestinal section: airway, two large-bore cannulae, crossmatch, fluid and blood, and urgent endoscopy. Remember that a patient on anticoagulants or antiplatelets from Chapter 01 bleeds more and is harder to stop, so establish what he takes early.
النزف الهضمي الهائل يُدبَّر كما في قسم الجهاز الهضمي العلوي: مجرى هواء وقنيتان واسعتان ومطابقة زمر وسوائل ودم وتنظير عاجل. ويجب تذكّر أن المريض على مضادّات التخثّر أو مضادّات الصفيحات من الفصل الأول ينزف أكثر ويصعب إيقافه، فيجب تحديد ما يتناوله مبكّراً.
5.23 · Gastrointestinal Drugs٥٫٢٣ · الأدوية الهضمية
Proton pump inhibitors suppress acid strongly and are taken before food, typically thirty minutes before breakfast. Long-term use is associated with a higher risk of Clostridioides difficile infection, hypomagnesaemia, B12 deficiency and fracture, so they are reviewed rather than continued indefinitely. H2 receptor antagonists are weaker; antacids give immediate symptomatic relief but interfere with the absorption of other drugs, so they are separated in time — a point that matters with levothyroxine as Chapter 03 sets out.
مثبّطات مضخّة البروتون تكبت الحمض بقوّة وتُؤخذ قبل الطعام، وعادةً قبل الإفطار بثلاثين دقيقة. والاستخدام طويل الأمد يرتبط بخطر أعلى لعدوى المطثية العسيرة ونقص المغنيسيوم ونقص فيتامين ب١٢ والكسور، فتُراجَع لا تُواصَل إلى أجل غير مسمّى. وحاصرات مستقبل الهيستامين H2 أضعف؛ ومضادّات الحموضة تعطي تخفيفاً فورياً للأعراض لكنها تتداخل مع امتصاص أدوية أخرى، فتُفصَل زمنياً — وهي نقطة تهمّ مع الليفوثيروكسين كما يبيّن الفصل الثالث.
Laxatives differ by mechanism: bulk-forming agents need adequate fluid or they worsen constipation; osmotic agents such as lactulose draw water in; stimulants are for short-term use; and stool softeners ease straining. Antidiarrhoeals such as loperamide are avoided in bloody or febrile infective diarrhoea, in suspected Clostridioides difficile infection and in active inflammatory colitis, because slowing the bowel retains the organism or toxin and can precipitate toxic megacolon.
المليّنات تختلف بالآلية: فالمكوّنة للكتلة تحتاج سوائل كافية وإلا فاقمت الإمساك؛ والتناضحية كاللاكتولوز تسحب الماء؛ والمنبّهة للاستخدام قصير الأمد؛ ومليّنات البراز تخفّف الإجهاد. ومضادّات الإسهال كاللوبيراميد تُتجنّب في الإسهال الخمجي الدموي أو المصحوب بحمّى وعند الاشتباه بعدوى المطثية العسيرة وفي التهاب القولون الالتهابي الفعّال، فإبطاء الأمعاء يُبقي الكائن الممرض أو السمّ داخل الأمعاء وقد يُحدث تضخّم قولون سمّياً.
PARACETAMOL OVERDOSE is the drug point that matters most in a liver chapter. It is dangerous precisely because the patient may look and FEEL WELL for the first day — and by the time he is unwell, the damage is done.
الجرعة الزائدة من الباراسيتامول أهمّ نقطة دوائية في فصل الكبد. وهي خطرة تحديداً لأن المريض قد يبدو ويشعر بأنه بخير في اليوم الأول — وحين يشعر بالمرض يكون الضرر قد وقع.
Non-steroidal anti-inflammatory drugs and corticosteroids both raise the risk of peptic ulceration and gastrointestinal bleeding, and the risk multiplies when they are combined or added to an anticoagulant. Gastroprotection is prescribed where the risk is high, and a patient with dyspepsia on these drugs is not simply given an antacid and sent away.
مضادّات الالتهاب غير الستيرويدية والستيرويدات القشرية كلاهما يرفع خطر التقرّح الهضمي والنزف الهضمي، والخطر يتضاعف عند جمعهما أو إضافتهما لمضادّ تخثّر. وتُوصَف الوقاية المعدية حيث يرتفع الخطر، والمريض بعسر هضم على هذه الأدوية لا يُعطى مضادّ حموضة ويُصرَف ببساطة.
5.24 · Antiemetics and Other Gut Drugs٥٫٢٤ · مضادّات القيء وأدوية هضمية أخرى
The choice of antiemetic follows the CAUSE.
اختيار مضادّ القيء يتبع السبب.
Sucralfate works differently from acid suppressants: it forms a protective barrier over the ulcer base rather than reducing acid. That mechanism dictates the administration — it is taken on an empty stomach, about an hour before meals, and it binds other drugs and reduces their absorption, so it is separated in time from everything else, in the same way as antacids and as the phosphate binders in Chapter 04.
السكرالفات يعمل بطريقة مختلفة عن كابتات الحمض: فهو يشكّل حاجزاً واقياً فوق قاعدة القرحة بدلاً من تقليل الحمض. وتلك الآلية تُملي طريقة الإعطاء — فيُؤخذ على معدة فارغة قبل الوجبات بنحو ساعة، وهو يربط أدوية أخرى ويقلّل امتصاصها، فيُفصَل زمنياً عن كلّ شيء آخر، كما هي الحال مع مضادّات الحموضة ورابطات الفوسفات في الفصل الرابع.
Herbal and traditional remedies deserve a specific mention, because patients frequently take them and do not regard them as medicines, so they do not appear on the drug history unless asked about directly. Several are hepatotoxic, and a number of unexplained liver injuries trace back to them. Ask about herbal preparations, traditional remedies and imported supplements by name and without judgement, particularly in any patient presenting with abnormal liver tests, and record what is being taken.
العلاجات العشبية والتقليدية تستحقّ ذكراً محدّداً، فالمرضى يتناولونها كثيراً ولا يعدّونها أدوية، فلا تظهر في القصّة الدوائية إلا إن سُئل عنها مباشرةً. وعدّة منها سامّة للكبد، وعدد من الأذيّات الكبدية غير المفسَّرة يرجع إليها. ويجب السؤال عن المستحضرات العشبية والعلاجات التقليدية والمكمّلات المستوردة بالاسم ودون حكم، خاصّةً لدى أيّ مريض يحضر بتحاليل كبد شاذّة، وتسجيل ما يُتناوَل.
5.25 · Living With Gastrointestinal Disease٥٫٢٥ · التعايش مع المرض الهضمي
A stoma changes how a person sees his own body, and the distress is often GREATER than the clinical team assumes. Expect grief, embarrassment, fear of odour and noise, fear of leakage in public, and worry about intimacy, prayer and returning to work.
الفغرة تغيّر كيف يرى الشخص جسده والكرب غالباً أكبر ممّا يفترض الفريق السريري. ويُتوقَّع الحزن والإحراج والخوف من الرائحة والصوت والخوف من التسرّب في الأماكن العامة والقلق بشأن العلاقة الحميمة والصلاة والعودة إلى العمل.
Inflammatory bowel disease typically begins in young adulthood and affects education, work, travel and relationships. Urgency and unpredictability are what patients find hardest — knowing where a toilet is becomes a constant background calculation. Ask about the effect on daily life rather than only about stool frequency, screen for the depression and anxiety that are common in a relapsing illness, and support adherence to maintenance treatment during remission, which is when patients stop taking it.
داء الأمعاء الالتهابي يبدأ في الشباب عادةً ويؤثّر على التعليم والعمل والسفر والعلاقات. والإلحاح وعدم القابلية للتنبّؤ أصعب ما يجده المرضى — فمعرفة مكان المرحاض تصير حساباً خلفياً دائماً. ويُسأل عن الأثر على الحياة اليومية لا عن تواتر البراز فقط، ويُجرى مسح للكشف عن الاكتئاب والقلق الشائعين في مرض ناكس، ويُدعَم الالتزام بعلاج الصيانة أثناء الهدأة، فذلك حين يتوقّف المرضى عنه.
Alcohol is a sensitive subject and in this setting a legally and religiously prohibited one, which makes patients less likely to disclose it. Where it is clinically relevant — in liver disease or pancreatitis — ask in a private, non-judgemental and matter-of-fact way, without an audience of family members, and make clear that the question is asked of everyone and is for their treatment. A patient who feels judged will simply deny it, and the clinical picture will then make no sense.
الكحول موضوع حسّاس وهو في هذا السياق محرَّم قانوناً وديناً، ما يجعل المرضى أقلّ ميلاً للإفصاح. وحيث يكون ذا صلة سريرية — في مرض الكبد أو التهاب البنكرياس — يُسأل بطريقة خاصّة وواقعية ودون إصدار أحكام، دون جمهور من أفراد الأسرة، ويُوضَّح أن السؤال يُطرَح على الجميع وأنه لعلاجهم. والمريض الذي يشعر بالحكم عليه سينكر ببساطة، ولن تكون الصورة السريرية عندها منطقية.
5.26 · Gastrointestinal Health in the Saudi Setting٥٫٢٦ · الصحّة الهضمية في السياق السعودي
Non-alcoholic fatty liver disease (NAFLD, now also called MASLD) is now the dominant liver problem in the Kingdom, and the reason is straightforward: alcohol is prohibited, so the classic Western cause of cirrhosis is largely absent, while obesity, type 2 diabetes and dyslipidaemia are highly prevalent. Estimates put NAFLD prevalence at roughly a quarter of the adult population, projected to rise further by 2030, and it is far higher — around half or more — among patients with type 2 diabetes. Cirrhosis and liver cancer arising from it are projected to increase substantially.
مرض الكبد الدهني غير الكحولي (NAFLD، ويُعرف الآن أيضاً باسم MASLD) صار المشكلة الكبدية المهيمنة في المملكة، والسبب واضح: فالكحول محرَّم، فالسبب الغربي الكلاسيكي لتشمّع الكبد غائب إلى حدّ بعيد، بينما السمنة والسكّري من النمط الثاني واضطراب الشحوم عالية الانتشار. وتضع التقديرات انتشاره عند نحو ربع البالغين، ويُتوقّع ارتفاعه أكثر بحلول ٢٠٣٠، وهو أعلى بكثير — نحو النصف أو أكثر — بين مرضى السكّري من النمط الثاني. ويُتوقّع ازدياد تشمّع الكبد وسرطان الكبد الناشئين عنه جوهرياً.
The practical consequence is that a raised ALT in a Saudi adult with obesity or diabetes most often means FATTY LIVER — and the mainstay of treatment is weight loss, activity and metabolic control rather than a drug.
العاقبة العملية أن ارتفاع ALT في بالغ سعودي بسمنة أو سكّري يعني الكبد الدهني غالباً — والركيزة العلاجية هي إنقاص الوزن والنشاط والضبط الاستقلابي لا الدواء.
Hajj and Umrah bring millions into shared eating and washing facilities, and food and water hygiene is the practical protection against gastroenteritis and hepatitis A. Teach pilgrims to wash hands before eating and after the toilet, drink bottled or treated water, avoid food left standing in the heat, be cautious with uncooked items washed in untreated water, and seek care early for diarrhoea with fever or blood. Dehydration from diarrhoea in that heat becomes dangerous quickly, and oral rehydration is the first-line treatment.
الحجّ والعمرة يجمعان الملايين في مرافق أكل وغسل مشتركة، ونظافة الطعام والماء هي الحماية العملية من التهاب المعدة والأمعاء والتهاب الكبد A. يُنصح بتعليم الحجّاج غسل اليدين قبل الأكل وبعد المرحاض، وشرب ماء معبّأ أو معالَج، وتجنّب الطعام المتروك في الحرّ، والحذر من الأصناف غير المطهوّة المغسولة بماء غير معالَج، وطلب الرعاية مبكّراً للإسهال مع حمّى أو دم. والجفاف من الإسهال في تلك الحرارة يصير خطراً بسرعة، والإماهة الفموية هي العلاج الأول.
Fasting in Ramadan affects gastrointestinal patients in SPECIFIC ways, and a nurse who can advise practically is far more useful than one who simply advises against it.
الصيام في رمضان يؤثّر على مرضى الجهاز الهضمي بطرق محدّدة، والكادر التمريضي القادر على تقديم إرشاد عملي أنفع بكثير من كادر يكتفي بالنصح بعدم الصيام.
5.27 · Zoonotic and Regional Infections٥٫٢٧ · العدوى الحيوانية المنشأ والإقليمية
Brucellosis is endemic in the region and is worth knowing well, because it is easily missed. It is acquired from unpasteurised milk — particularly camel and goat milk — and unpasteurised dairy products, and by direct contact with infected animals, which makes farmers, herders, abattoir workers and veterinarians occupationally at risk. It presents insidiously with an undulating fever, drenching night sweats with a characteristic odour, malaise, joint and back pain, headache and weight loss, often with hepatosplenomegaly and deranged liver tests.
داء البروسيلّات متوطّن في المنطقة ويستحقّ معرفةً جيّدة فهو سهل الإغفال. ويُكتسَب من الحليب غير المبستر — وخاصّةً حليب الإبل والماعز — ومنتجات الألبان غير المبسترة، وبالمخالطة المباشرة للحيوانات المصابة، ما يجعل المزارعين والرعاة وعمّال المسالخ والأطبّاء البيطريين معرّضين مهنياً. ويتظاهر خفيةً بحمّى مموّجة وتعرّق ليلي غزير برائحة مميّزة وتوعّك وألم مفاصل وظهر وصداع ونقص وزن، مع ضخامة كبد وطحال وتحاليل كبد مضطربة غالباً.
The nursing points: take a careful history of raw milk consumption and animal contact, because without it the diagnosis is not considered; treatment requires a prolonged combination of antibiotics over weeks, and relapse follows incomplete treatment, so adherence teaching matters as much as it does in tuberculosis; and prevention is pasteurising or boiling milk and avoiding unpasteurised dairy, which is a public health message worth giving to any family that keeps animals.
النقاط التمريضية: تُؤخذ قصّة دقيقة عن تناول الحليب الخام ومخالطة الحيوانات، فبدونها لا يُنظَر في التشخيص؛ والعلاج يتطلّب توليفة مطوّلة من المضادات الحيوية على مدى أسابيع، والنكس يتبع العلاج غير الكامل، فتعليم الالتزام يهمّ بقدر ما يهمّ في السلّ؛ والوقاية بسترة الحليب أو غليه وتجنّب الألبان غير المبسترة، وهي رسالة صحّة عامّة تستحقّ إعطاءها لأيّ أسرة تربّي حيوانات.
HYDATID DISEASE is caused by the tapeworm ECHINOCOCCUS, whose eggs are passed in DOG faeces and acquired by humans through contaminated hands, food or water — which makes it a livestock and sheepdog-associated infection, and relevant here.
داء الكيسات العدارية تسبّبه الشريطية المشوّكة التي تُطرَح بيوضها في براز الكلاب وتُكتسَب بأيدٍ أو أطعمة أو مياه ملوّثة، مما يجعله عدوى مرتبطة بالماشية وكلاب الرعي، وذا صلة بالموضوع هنا.
Test yourselfالاختبار الذاتي
Loading… جارٍ التحميل…
Loading… جارٍ التحميل…
Loading… جارٍ التحميل…